Related Experiment Video
Updated: May 6, 2026

Transcanalicular Diode Laser-assisted Dacryocystorhinostomy for the Treatment of Primary Acquired Nasolacrimal Duct Obstruction
Published on: October 13, 2017
Superior canal dehiscence syndrome: clinical manifestations and radiologic correlations
Issam Saliba1, Anastasios Maniakas, Lina Zahra Benamira
1Department of Otolaryngology, Head and Neck Surgery, Montreal University Hospital Center (CHUM), Notre Dame Hospital, University of Montreal, 1560 Sherbrooke East, Montreal, QC, H2L 4M1, Canada, issam.saliba@umontreal.ca.

Abstract:
The objective of this study is to describe the superior canal dehiscence syndrome (SCDS) and its vestibule-cochlear manifestations, while analyzing dehiscence size, audiogram and vestibular-evoked myogenic potential (VEMP) changes following dehiscence obliteration. We conducted a prospective study in a tertiary referral center. All Patients diagnosed and surgically treated for SCDS were operated through a middle fossa craniotomy (MFC). Clinical and radiological data were collected. The main outcome measures were Air-bone gaps, Pure-tone average (PTA), speech discrimination scores (SDS) and VEMP thresholds and were correlated to dehiscence size. 28 patients were included in this study with a mean dehiscence size of 4.68 mm. Phonophobia and imbalance were the most debilitating cochlear and vestibular symptoms, respectively. At 2 months postoperatively, low-frequency air-bone gaps showed a statistically significant improvement (p < 0.001). SDS and PTA did not show any statistically significant changes 2 months postoperatively (p = 0.282 and p = 0.295, respectively). VEMP threshold differences between operated and contralateral ears were statistically significant preoperatively (p < 0.001) and non-significant 2 months postoperatively (p = 0.173). Dehiscence size only showed a statistically significant correlation with preoperative total cochlear symptoms, while remaining insignificant with all other variables measured. Air-bone gaps, VEMP and computerized tomography remain essential tools in diagnosing and following SCDS. Dehiscence size is an independent factor in the analysis of SCDS, with cochlear symptomatology being associated to dehiscence sizes. Finally, it is shown that overall symptomatology, audiometric results and VEMP thresholds return to normal values post-obliteration, confirming the continuing success of the MFC approach for SCDS obliteration.


Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:23
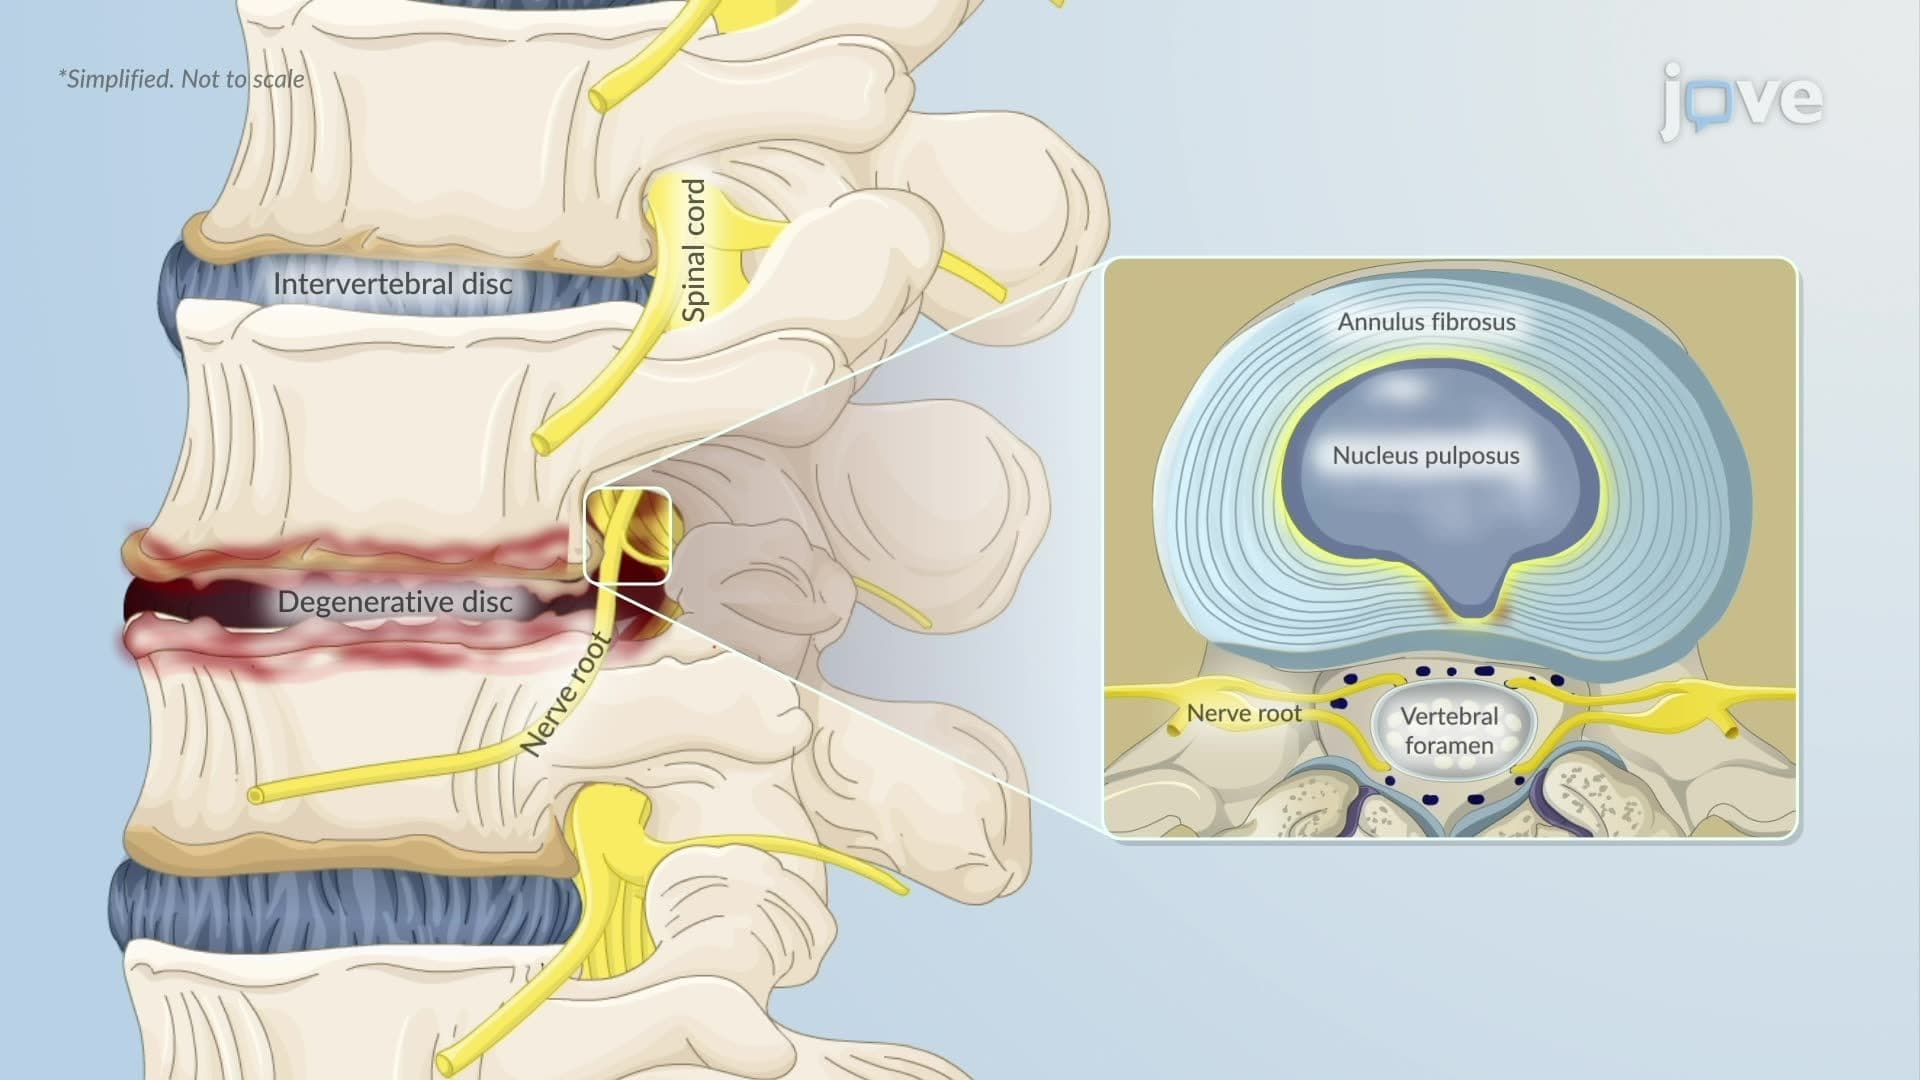
Degenerative Disc Disease ll: Pathophysiology
 01:27
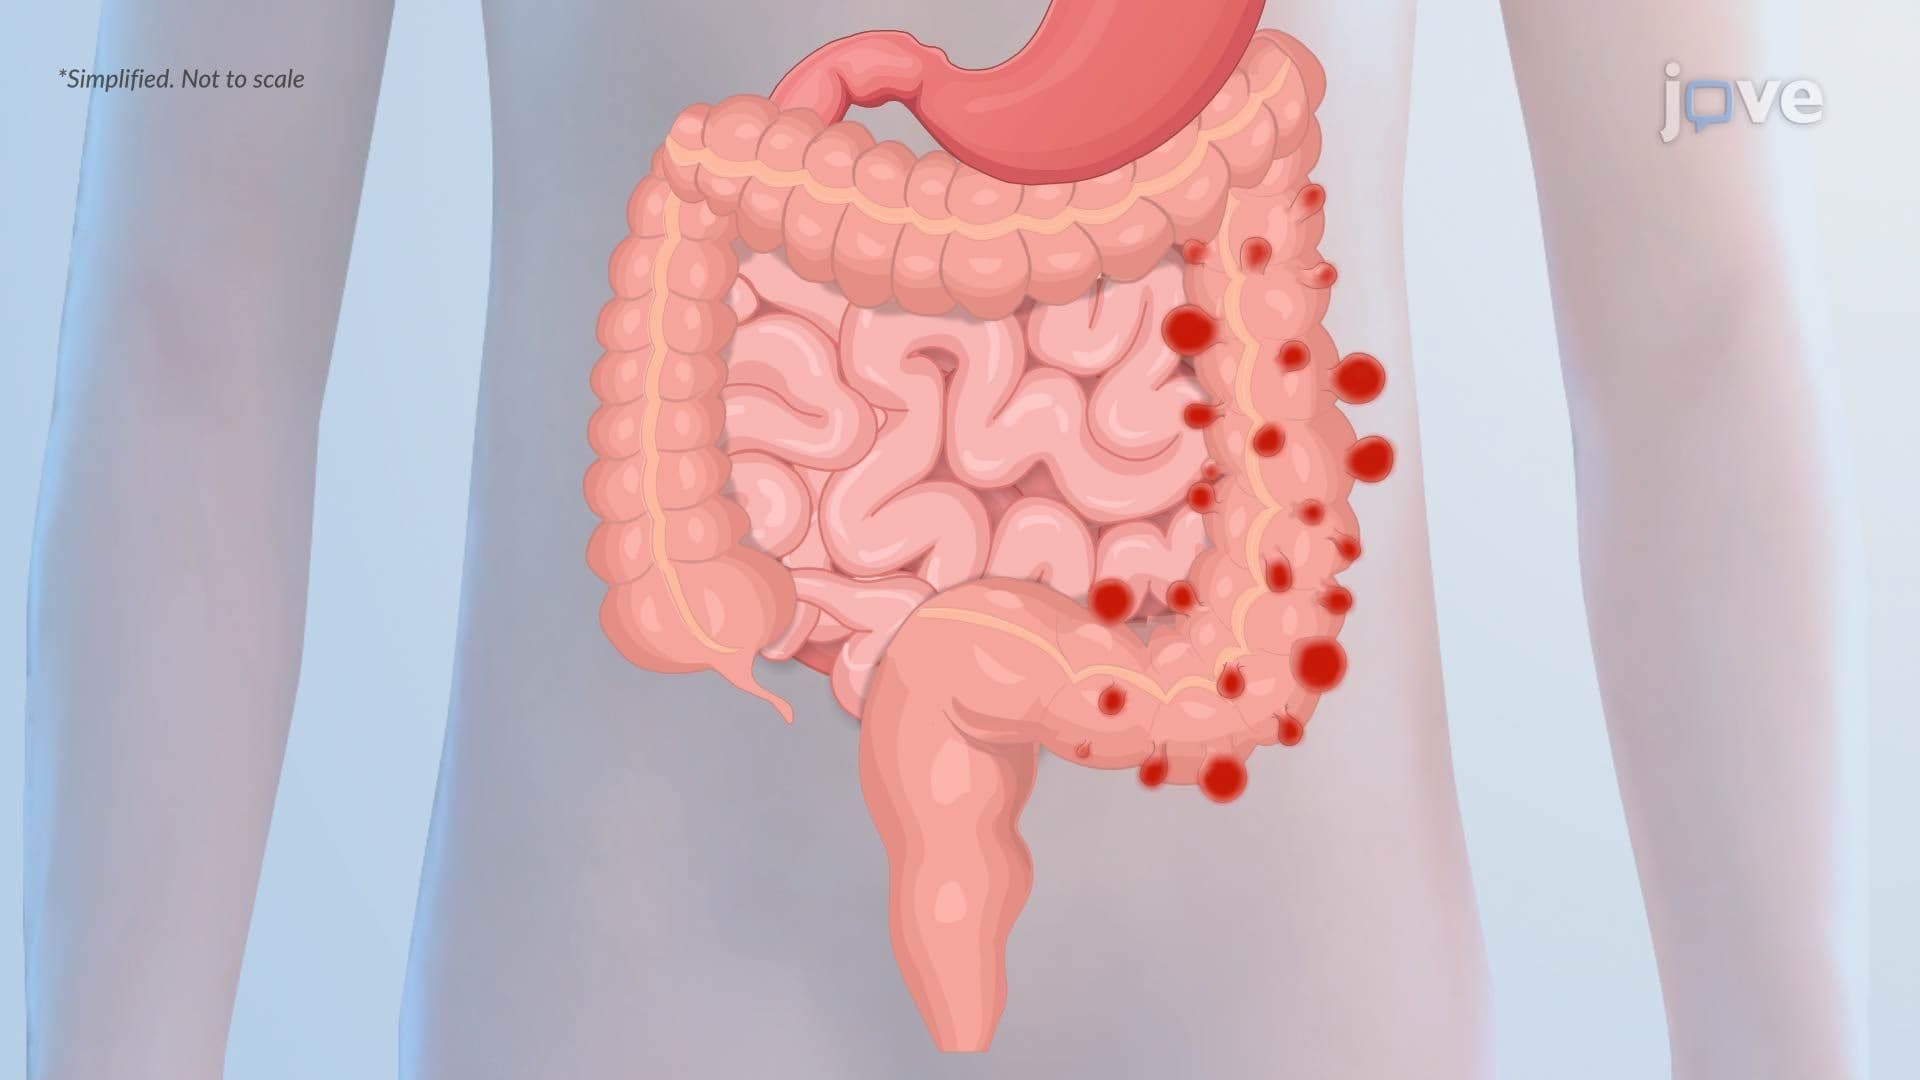
Diverticular Disease of the Colon
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies