Related Experiment Video
Updated: May 6, 2026
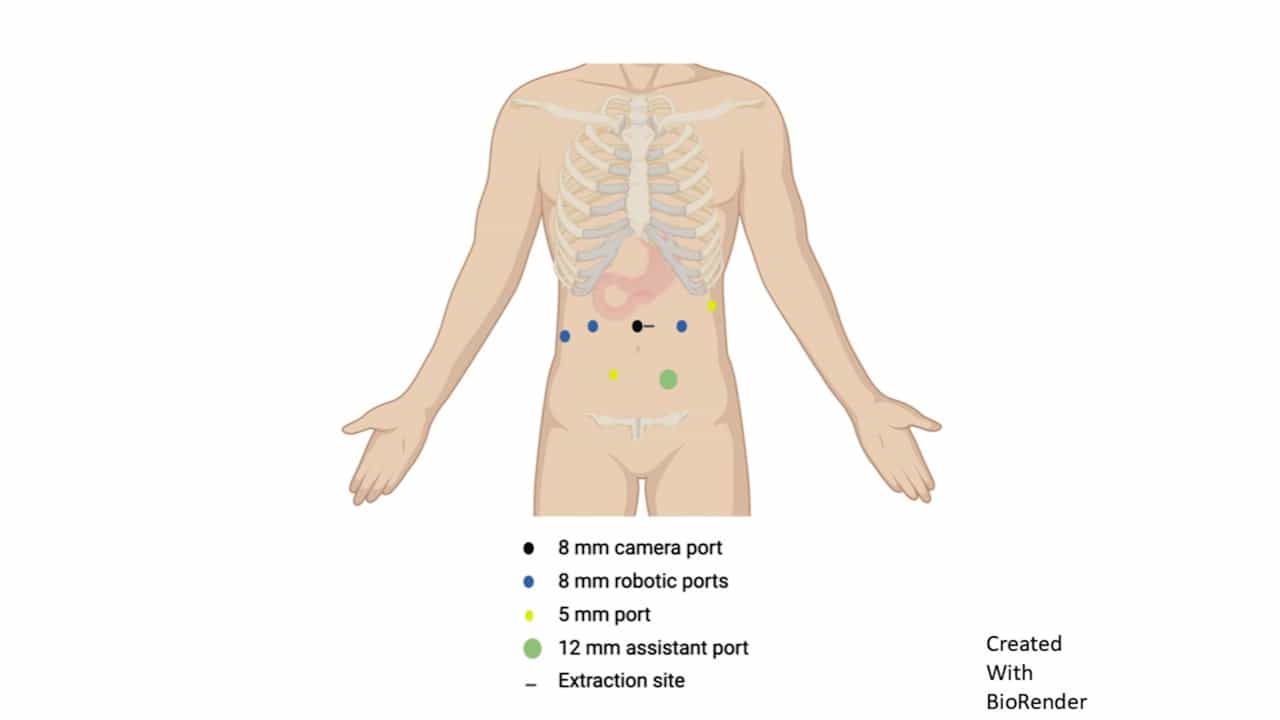

Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
Neoadjuvant imatinib in advanced primary or locally recurrent dermatofibrosarcoma protuberans: a multicenter phase II
Selma Ugurel1, Thomas Mentzel, Jochen Utikal
1Authors' Affiliations: Department of Dermatology, University of Würzburg, Würzburg; Dermatopathology Bodensee, Friedrichshafen; Skin Cancer Unit, German Cancer Research Center, Heidelberg; Department of Dermatology, University Hospital Heidelberg, Heidelberg; Department of Dermatology, University Medical Center Mannheim, University of Heidelberg, Mannheim; Department of Dermatology, Martin Luther University, Halle/Saale; Department of Dermatology, Elbe Klinikum Buxtehude, Buxtehude; Department of Dermatology, Saarland University Hospital, Homburg, Saarland; Department of Dermatology, University Hospital of Münster, Münster; Department of Dermatology, University of Kiel, Kiel; Department of Dermatology, Technical University Munich, Munich; Department of Dermatology, University Hospital Erlangen, Erlangen; Department of Dermatology, Helios Klinikum Erfurt, Erfurt; Department of Pathology, University of Göttingen, Göttingen; Department of Dermatology, University of Essen, Essen, Germany; and Department of Dermatology, Medical University Graz, Graz, Austria.

Purpose:
Dermatofibrosarcoma protuberans (DFSP) is a rare cutaneous tumor. COL1A1-PDGFB gene fusion is frequent in DFSP, rendering tumor cell proliferation and survival dependent on PDGFRβ (platelet-derived growth factor receptor β) signaling. This trial investigated imatinib as neoadjuvant treatment of DFSP, including long-term follow-up.
Experimental Design:
The primary endpoint of this multicenter phase II trial was response; secondary endpoints were safety, tumor relapse, and response biomarkers. Patients with advanced primary or locally recurrent DFSP and measurable disease by RECIST (response evaluation criteria in solid tumors) were eligible and received imatinib 600 mg/d until definitive surgery with histopathologic proof of tumor-free margins.
Results:
Sixteen patients received imatinib, and 14 patients were evaluable for all endpoints. Median treatment duration was 3.1 months; median tumor shrinkage was 31.5%. Best overall response was 7.1% complete response (CR), 50.0% partial response (PR), 35.7% stable disease, and 7.1% progressive disease (PD). Toxicity was moderate with 25.0% grade 3 and 4 events. During a median follow-up of 6.4 years, one patient developed secondary resistance to imatinib but responded to second-line sunitinib. This patient also presented local recurrence, distant metastasis, and death from DFSP. Exploratory analysis showed that response to imatinib was associated with decreased tumor cellularity and formation of strong hyalinic fibrosis. Weak PDGFRB phosphorylation and pigmented-type DFSP were associated with nonresponse. Additional to PDGFRB, the kinases EGFR and insulin receptor were found activated in a high percentage of DFSPs.
Conclusion:
The neoadjuvant use of imatinib 600 mg/d in DFSP is efficacious and well tolerated. Long-term follow-up results do not definitely support smaller surgical margins after successful imatinib pretreatment, and presume that secondary resistance to imatinib might promote accelerated disease progression.


