Related Experiment Video
Updated: May 5, 2026
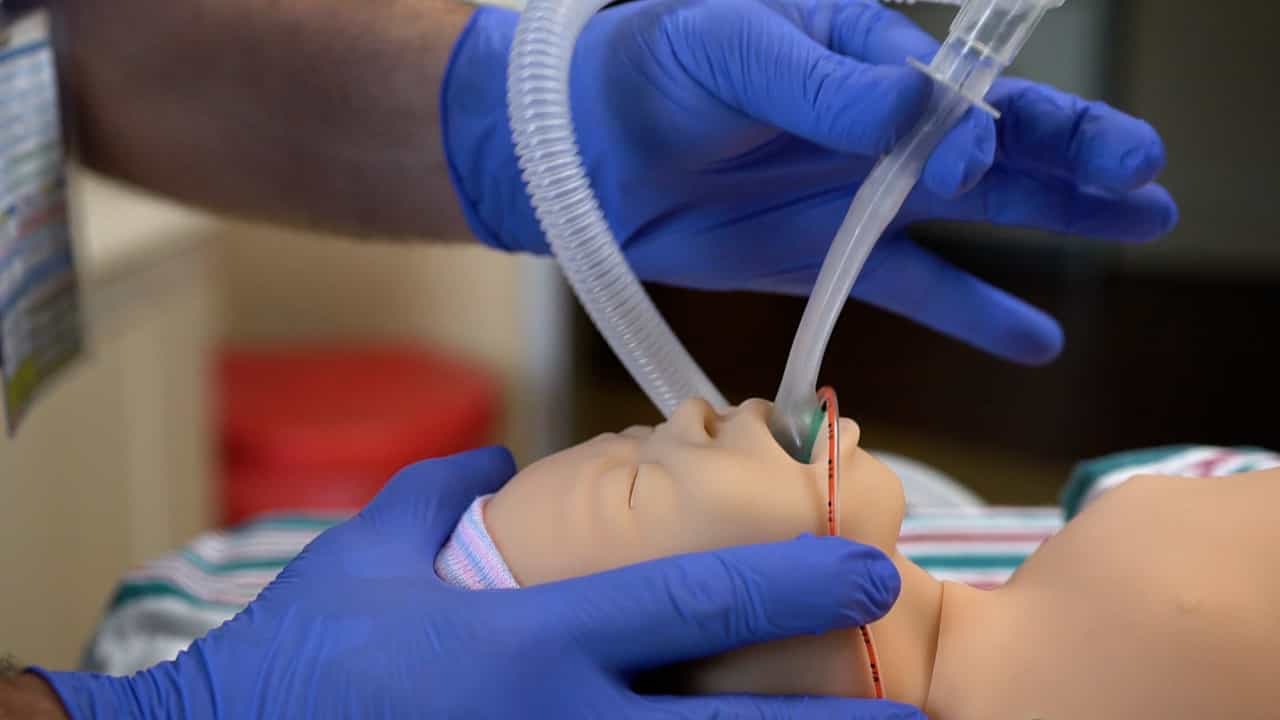
Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Supraglottoplasty in premature infants with laryngomalacia: does gestation age at birth influence outcomes?
Venkata S P B Durvasula1, Bradley R Lawson, Charles M Bower
1Arkansas Children's Hospital, Little Rock, Arkansas, USA.

Insights
Supraglottoplasty (SGP) success rates were similar for premature and term infants with congenital laryngomalacia. However, preterm infants, especially those born before 32 weeks, experienced higher rates of dysphagia and gastrostomy tube placement.
Area of Science:
- Pediatric Otolaryngology
- Neonatal Surgery
- Congenital Airway Anomalies
Background:
- Congenital laryngomalacia (LM) is a common cause of infant stridor.
- Prematurity is often considered a risk factor for surgical outcomes.
- Supraglottoplasty (SGP) is a primary surgical intervention for LM.
Purpose of the Study:
- To compare the efficacy of SGP in premature infants versus term infants with LM.
- To investigate if prematurity impacts SGP success rates.
- To assess secondary outcomes such as dysphagia and need for gastrostomy tube placement.
Main Methods:
- Retrospective case series analysis of 325 patients undergoing SGP.
- Exclusion criteria included age >12 months, syndromic conditions, and neurologic/cardiac comorbidities.
- Outcomes assessed included SGP success, revision rates, tracheostomy, secondary airway lesions (SAL), dysphagia, and gastrostomy tube (GT) placement.
Main Results:
- SGP success rates were comparable between term (92.7%) and preterm (90%) infants (P = .5865).
- Preterm infants showed significantly higher incidence of SAL (72.5% vs 34.6%, P = .0002) and dysphagia (32.5% vs 6.6%, P < .001).
- Gastrostomy tube insertion was more frequent in preterm infants (27.5% vs 6.6%, P = .003), particularly those born <32 weeks gestation.
Conclusions:
- SGP outcomes are similar for term and preterm infants with congenital laryngomalacia.
- Preterm infants, especially those with very low gestational age (<32 weeks), face increased risks of post-operative dysphagia and need for feeding support.
- Gestational age is a critical factor influencing long-term feeding outcomes after SGP.
Purpose:
Prematurity is thought to be to be an independent risk factor for supraglottoplasty (SGP) failure. The purpose of this study was to compare the outcomes of supraglottoplasty in premature infants with congenital laryngomalacia (LM) with that of term infants.
Study Design:
Case series with chart review.
Setting:
Tertiary-care pediatric institution.
Methods:
Analysis was performed on 325 consecutive patients undergoing SGP between 2004 and 2012. Patients older than 12 months age or with syndrome, neurologic, or cardiac comorbidities were excluded. Resolution of airway symptoms after SGP was considered successful while revision SGP and tracheostomy were considered failures. The rates of secondary airway lesions (SAL), dysphagia, and gastrostomy tube (GT) placement were also compared.
Results:
A total of 176 infants (136 term, 40 preterm) were identified. SGP was successful in 92.7% term and 90% preterm infants with no significant difference (P = .5865). Incidence of revision SGP and tracheostomy was similar among the groups. The outcomes of SGP were the same in all groups stratified by age. Incidence of SAL was significantly higher in preterm (72.5%) compared to term infants (34.6%, P = .0002). Dysphagia rates in the follow-up were higher in preterm (32.5%) versus term infants (6.6%, P < .001). The rate of GT insertion was significantly greater (P = .003) in preterm (27.5%) than term infants (6.6%). The preoperative dysphagia, persistent dysphagia, and GT in follow-up was significantly higher when gestation age <32 weeks (25%, P = .0168).
Conclusion:
Supraglottoplasty outcomes in term and preterm infants were similar irrespective of gestation age. Higher rates of dysphagia in follow-up are seen when gestation age <32 weeks.