Related Experiment Video
Updated: May 4, 2026
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Long-term efficacy of modified-release recombinant human thyrotropin augmented radioiodine therapy for benign
Søren Fast1, Laszlo Hegedüs, Furio Pacini
11 Department of Endocrinology and Metabolism, Odense University Hospital , Odense, Denmark .

Background:
Enhanced reduction of multinodular goiter (MNG) can be achieved by stimulation with recombinant human thyrotropin (rhTSH) before radioiodine ((131)I) therapy. The objective was to compare the long-term efficacy and safety of two low doses of modified release rhTSH (MRrhTSH) in combination with (131)I therapy.
Methods:
In this phase II, single-blinded, placebo-controlled study, 95 patients (57.2 ± 9.6 years old, 85% women, 83% Caucasians) with MNG (median size 96.0 mL; range 31.9-242.2 mL) were randomized to receive placebo (n=32), 0.01 mg MRrhTSH (n=30), or 0.03 mg MRrhTSH (n=33) 24 hours before a calculated (131)I activity. Thyroid volume (TV) and smallest cross-sectional area of trachea (SCAT) were measured (by computed tomography scan) at baseline, six months, and 36 months. Thyroid function and quality of life (QoL) was evaluated at three-month and yearly intervals respectively.
Results:
At six months, TV reduction was enhanced in the 0.03 mg MRrhTSH group (32.9% vs. 23.1% in the placebo group; p=0.03) but not in the 0.01 mg MRrhTSH group. At 36 months, the mean percent TV reduction from baseline was 44 ± 12.7% (SD) in the placebo group, 41 ± 21.0% in the 0.01 mg MRrhTSH group, and 53 ± 18.6% in the 0.03 mg MRrhTSH group, with no statistically significant differences among the groups, p=0.105. In the 0.03 mg MRrhTSH group, the subset of patients with basal (131)I uptake <20% had a 24% greater TV reduction at 36 months than the corresponding subset of patients in the placebo group (p=0.01). At 36 months, the largest relative increase in SCAT was observed in the 0.03 mg MRrhTSH group (13.4 ± 23.2%), but this was not statistically different from the increases observed in the placebo or the 0.01 mg MRrhTSH group (p=0.15). Goiter-related symptoms were reduced and QoL improved, without any enhanced benefit from using MRrhTSH. At three years, the prevalence of permanent hypothyroidism was 13%, 33%, and 45% in the placebo, 0.01 mg, and 0.03 mg MRrhTSH groups respectively. The overall safety profile of the study was favorable.
Conclusions:
When used as adjuvant to (131)I, enhanced MNG reduction could not be demonstrated with MRrhTSH doses ≤ 0.03 mg, indicating that the lower threshold for efficacy is around this level.

Related Concept Videos
 01:27
Goiter
 01:27
Hyperthyroidism II: Pathophysiology
 01:20
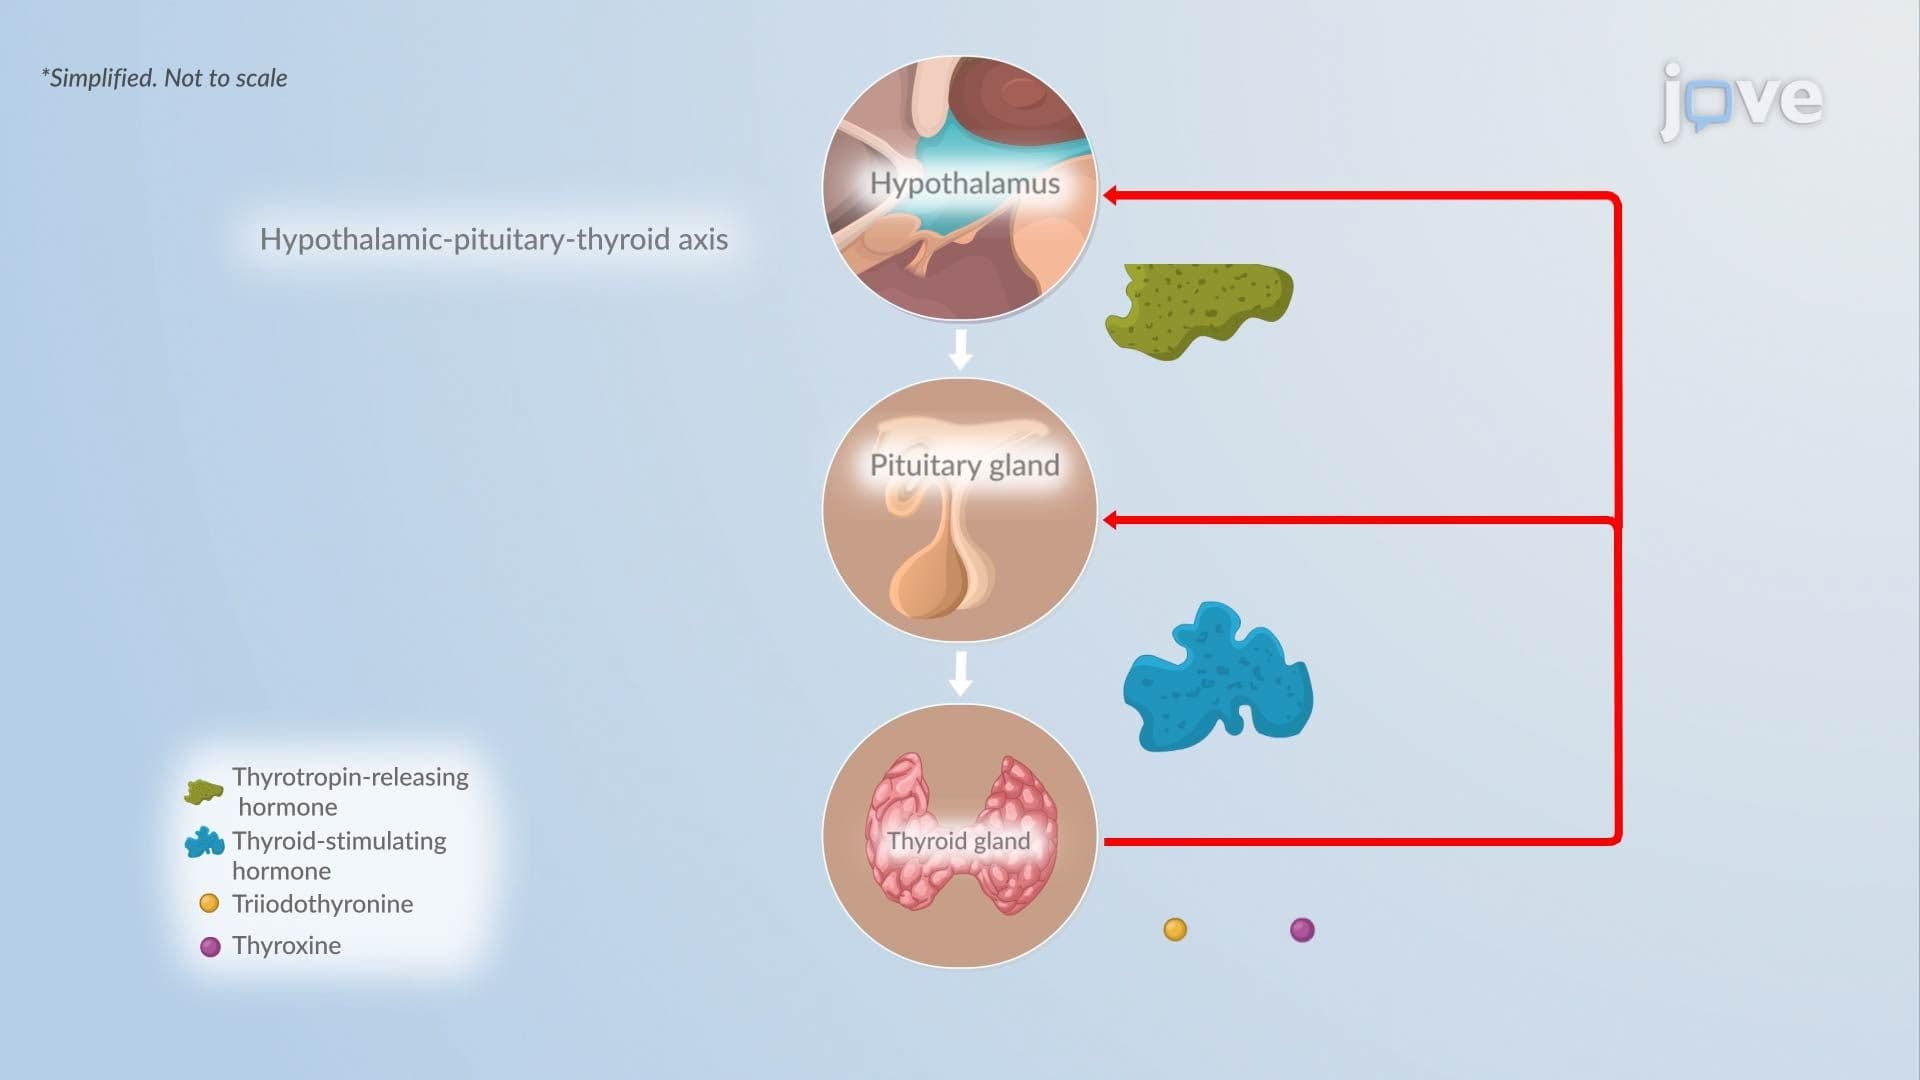
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:25
Hyperthyroidism I: Introduction
 01:24
Graves Disease II: Pathophysiology