Related Experiment Video
Updated: May 4, 2026
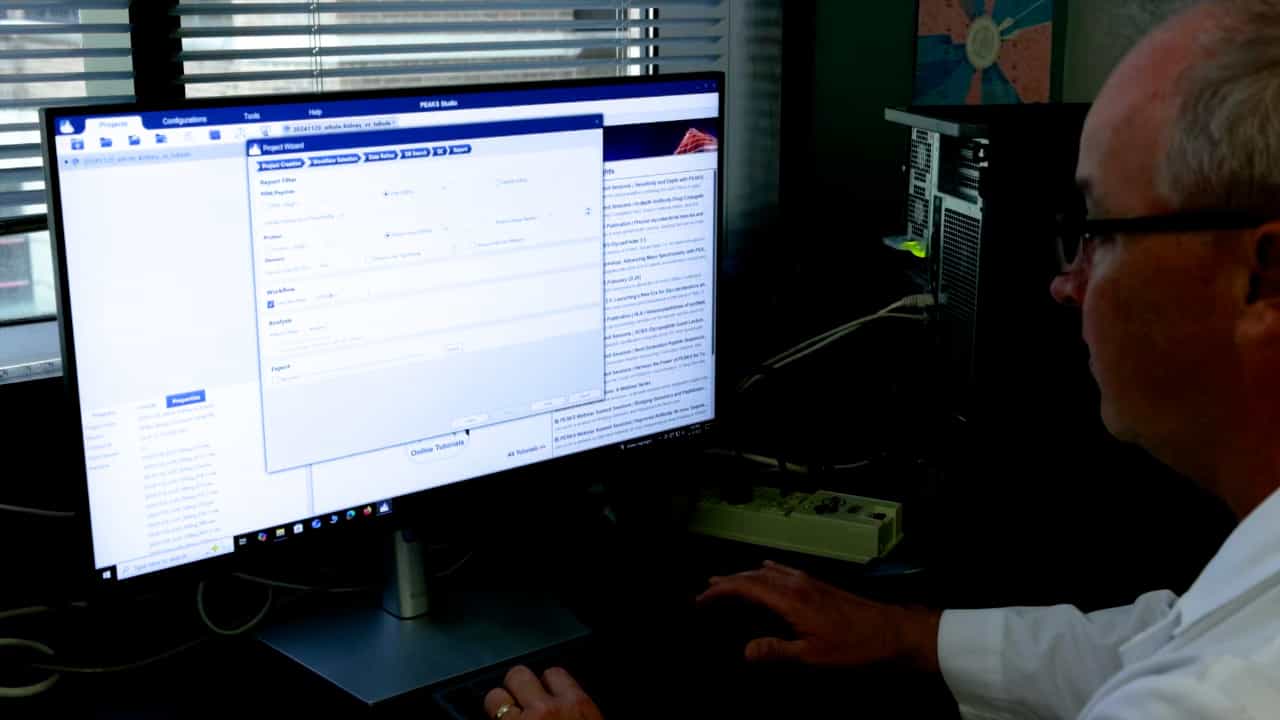

Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
Therapeutic approaches to slowing the progression of diabetic nephropathy - is less best?
Eva Vivian1, Chelsea Mannebach2
1University of Wisconsin-Madison, School of Pharmacy, Madison, USA;

Objective:
Angiotensin II receptor blockers (ARBs) and angiotensin-converting enzyme (ACE) inhibitors are known to reduce proteinuria and have been the first-line agents in the management of diabetic nephropathy for the past 20 years. This review covers recent studies that compare the benefit of additional blockage of the renin-angiotensin-aldosterone system through combination therapy with an ACE inhibitor and ARB, or a direct renin inhibitor (DRI), to monotherapy.
Design:
Primary and review articles that addressed the pathophysiology, diagnosis, and therapeutic options for attenuating the progression of diabetic nephropathy were retrieved through a MEDLINE search (January 1990 to December 2012) and the bibliographies of identified articles were reviewed. English language sources were searched using the following search terms: diabetes mellitus, nephropathy, proteinuria, ACE inhibitors, ARBs, and DRIs.
Setting:
Randomized, placebo-controlled, short- and long-term studies published in peer-reviewed journals that were determined to be methodologically sound, with appropriate statistical analysis of the results, were selected for inclusion in this review.
Participants:
Adult (≥18 years) patients with diabetic nephropathy.
Measurements:
Serum creatinine level was used to estimate glomerular filtration rate (GFR). GFR was calculated using the four-variable Modification of Diet in Renal Disease formula. The urine albumin-to-creatinine ratio was measured at baseline and at the conclusion of each study. A value between 3.4 mg/mmol and below 33.9 mg/mmol was defined as microalbuminuria. A value of 33.9 mg/mmol or more (approximately 300 mg/g creatinine) was defined as macroalbuminuria.
Results:
ACE inhibitors and ARBs are now the mainstay of treatment for diabetic nephropathy. However, combination therapy with an ACE inhibitor and an ARB, or DRI, has not been found to be more effective than monotherapy with an ACE inhibitor or ARB, and may increase the risk of hyperkalemia or acute kidney injury.
Conclusion:
Both ACE inhibitors and ARBs remain the first-line agents in attenuating the progression of diabetic nephropathy; however, recent studies suggest that combining an ACE inhibitor with an ARB, or combining a DRI with an ACE inhibitor or ARB, may increase adverse events without clinical benefits to offset them.
More Related Videos
 05:06
Author Spotlight: Integrating Tai Chi with Mindfulness Training to Achieve an Effective Mind-Body Exercise
Published on: July 14, 2023
 08:15
Author Spotlight: Network Pharmacology and Molecular Docking to Decipher the Action of Jiawei Shengjiang San Against Diabetic Kidney Disease
Published on: May 10, 2024
Related Concept Videos
 01:28
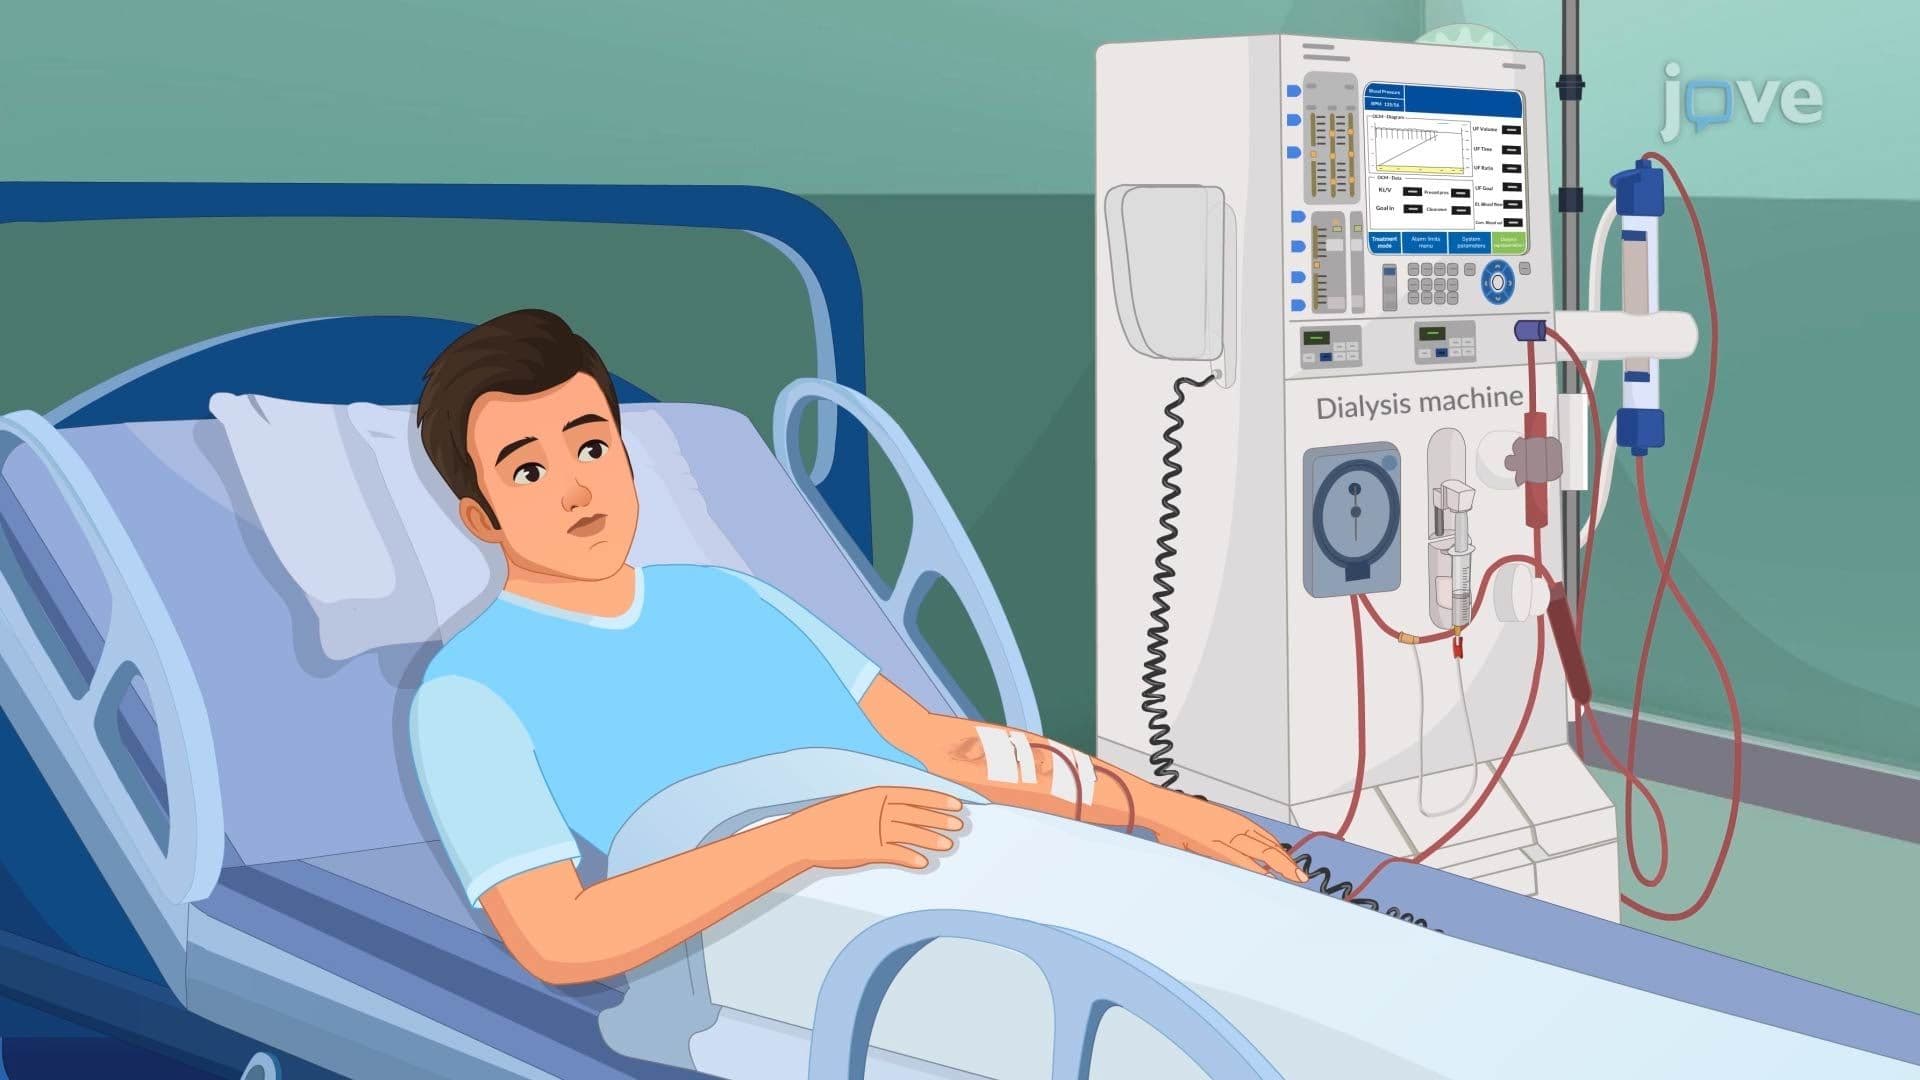
Diabetic Nephropathy
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:30
Heart Failure V: Medical Management
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:18
Chronic Kidney Disease IV: Nursing Management