Related Experiment Video
Updated: May 3, 2026
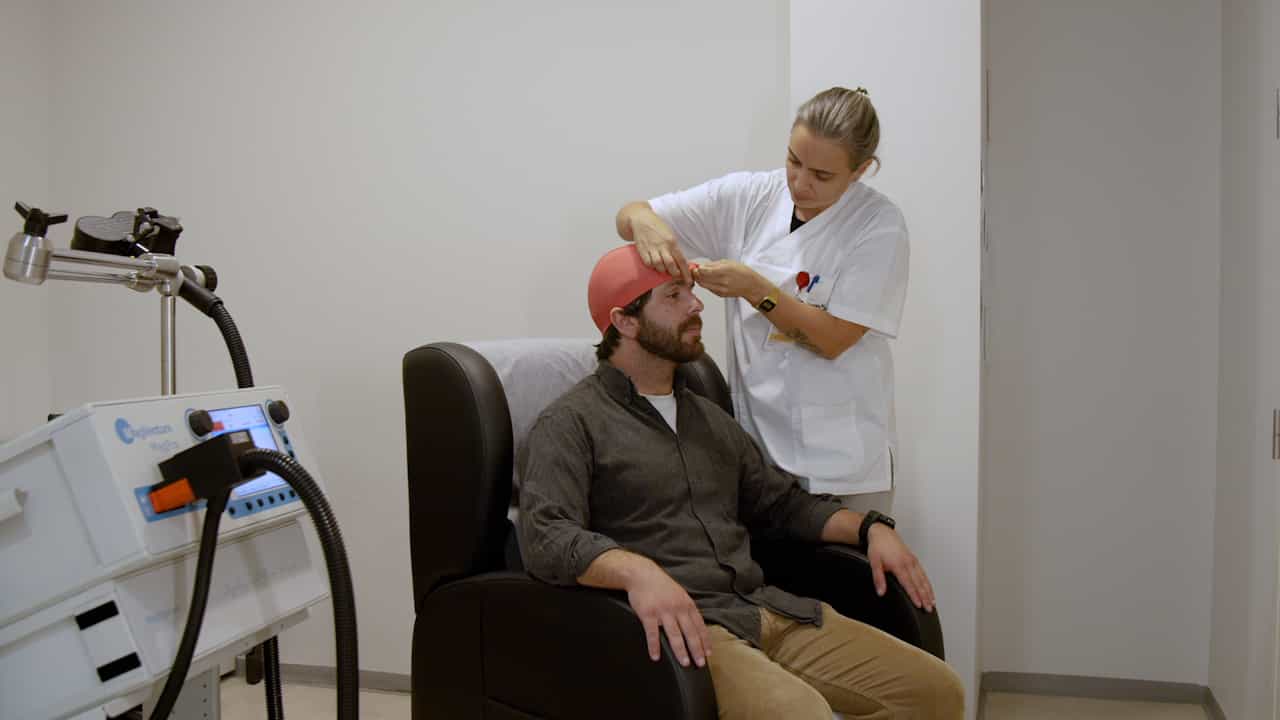

Conventional Repetitive Transcranial Magnetic Stimulation for Depression: A Step-by-Step Protocol
Published on: November 21, 2025
Implementation of treatment guidelines for specialist mental health care
Corrado Barbui1, Francesca Girlanda, Esra Ay
1Department of Public Health and Community Medicine, Section of Psychiatry, University of Verona, Policlinico "GB Rossi", Piazzale L.A. Scuro, 10, Verona, Italy, 37134.

Background:
A huge gap exists between the production of evidence and its take-up in clinical practice settings. To fill this gap, treatment guidelines, based on explicit assessments of the evidence base, are commonly employed in several fields of medicine, including schizophrenia and related psychotic disorders. It remains unclear, however, whether treatment guidelines have any impact on provider performance and patient outcomes, and how implementation should be conducted to maximise benefit.
Objectives:
The primary objective of this review was to examine the efficacy of guideline implementation strategies in improving process outcomes (performance of healthcare providers) and patient outcomes. We additionally explored which components of different guideline implementation strategies can influence process and patient outcomes.
Search Methods:
We searched the Cochrane Schizophrenia Group Register (March 2012), as well as references of included studies.
Selection Criteria:
Studies that examined schizophrenia-spectrum disorders to compare guideline implementation strategies with usual care or to assess the comparative efficacy of different guideline implementation strategies.
Data Collection And Analysis:
Review authors worked independently and in duplicate to critically appraise records from 882 studies; five individual studies met the inclusion criteria and were considered. As critical appraisal of the five included studies revealed substantial heterogeneity in terms of focus of the guideline, target of the intervention, implementation strategy and outcome measures, meta-analysis was carried out for antipsychotic co-prescribing only.
Main Results:
Of the five included studies, practitioner impact was assessed in three. The five studies were generally at unclear risk of bias, and all evidence in the 'Summary of findings' table was graded by review authors as of very low quality. Meta-analysis of two studies revealed that a combination of several guideline dissemination and implementation strategies targeting healthcare professionals did not reduce antipsychotic co-prescribing in schizophrenia outpatients (two studies, n = 1,082, risk ratio (RR) 1.10, 95% confidence interval (CI) 0.99 to 1.23; corrected for cluster design: n = 310, RR 0.97, CI 0.75 to 1.25). One trial, which studied a nurse-led intervention aimed at promoting cardiovascular disease screening, found a significant effect in terms of the proportion of people receiving screening (blood pressure: n = 96, RR 0.07, 95% CI 0.02 to 0.28; cholesterol: n = 103, RR 0.46, 95% CI 0.30 to 0.70; glucose: n = 103, RR 0.53, 95% CI 0.34 to 0.82; BMI: n = 99, RR 0.22, 95% CI 0.08 to 0.60; smoking status: n = 96, RR 0.28, 95% CI 0.12 to 0.64; Framingham score: n = 110, RR 0.69, 95% CI 0.55 to 0.87), although in the analysis corrected for cluster design, the effect was statistically significant for blood pressure and cholesterol only (blood pressure, corrected for cluster design: n = 33, RR 0.10, 95% CI 0.01 to 0.74; cholesterol, corrected for cluster design: n = 35, RR 0.49, 95% CI 0.24 to 0.99; glucose, corrected for cluster design: n = 35, RR 0.58, 95% CI 0.28 to 1.21; BMI, corrected for cluster design: n = 34, RR 0.18, 95% CI 0.02 to 1.37; smoking status, corrected for cluster design: n = 32, RR 0.25, 95% CI 0.06 to 1.03; Framingham score, corrected for cluster design: n = 38, RR 0.71, 95% CI 0.48 to 1.03; very low quality). Regarding participant outcomes, one trial assessed the efficacy of a shared decision-making implementation strategy and found no impact in terms of psychopathology, satisfaction with care and drug attitude. Another single trial studied a multifaceted intervention to promote medication adherence and found no impact in terms of adherence rates.
Authors' Conclusions:
With only five studies meeting inclusion criteria, and with limited low or very low quality usable information, it is not possible to arrive at definitive conclusions. The preliminary pattern of evidence suggests that, although small changes in psychiatric practice have been demonstrated, uncertainty remains in terms of clinically meaningful and sustainable effects of treatment guidelines on patient outcomes and how best to implement such guidelines for maximal benefit.
Related Concept Videos
 01:24
Treatment Strategies for Psychological Disorders
Psychological therapies focus on modifying emotions, thoughts, and behaviors through talking, interpreting, listening, rewarding, challenging, and modeling. Clinical psychologists, counselors, and social workers commonly practice psychotherapy. Clinical...
 01:30
Community Based Intervention
Foundations of Community Mental Health Programs
Central to the success of community-based interventions is the...
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...
 01:26
Psychosis: Goals of Pharmacotherapy
 01:28
Acute Coronary Syndrome IV: Interprofessional Care