Related Experiment Video
Updated: May 3, 2026
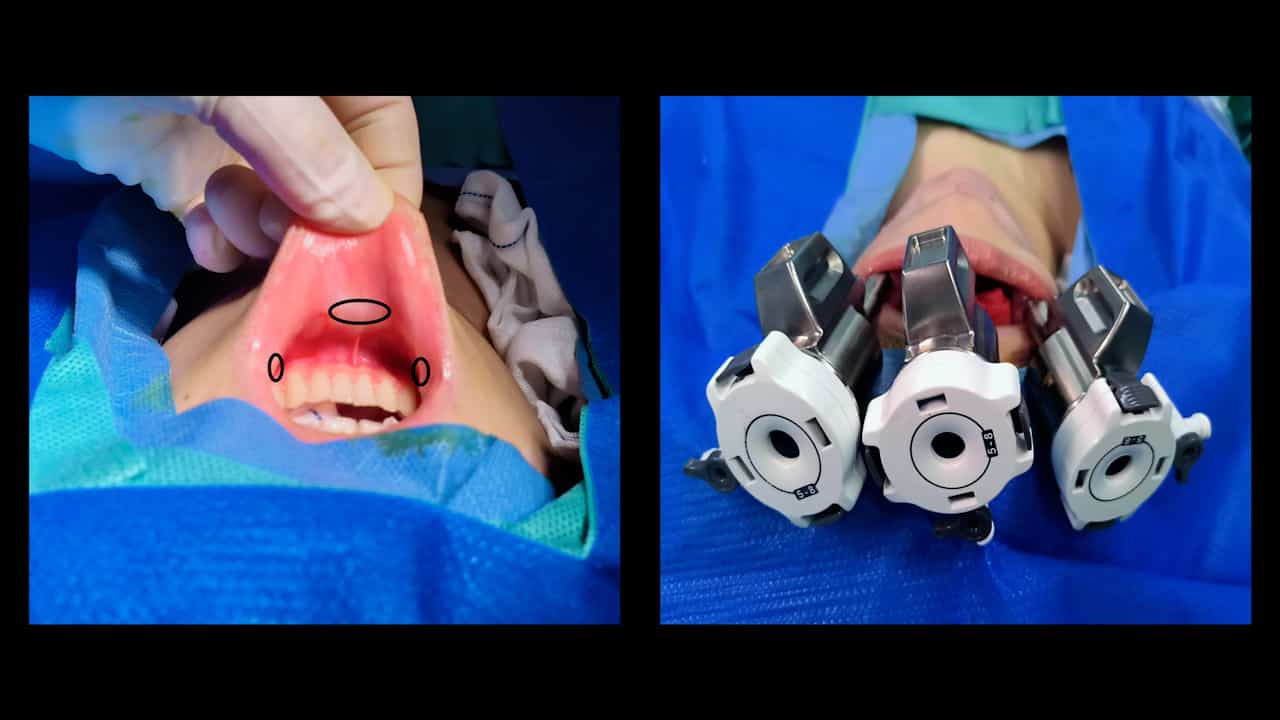

Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
Recurrent laryngeal nerve palsy during surgery for benign thyroid diseases: risk factors and outcome analysis
Keisuke Enomoto1, Shinya Uchino2, Shin Watanabe2
1Department of Otolaryngology, Noguchi Thyroid Clinic and Hospital Foundation, Beppu, Japan.

Background:
We investigated the risk factors for postoperative recurrent laryngeal nerve (RLN) palsy and related outcomes in patients with benign thyroid diseases.
Material And Methods:
From 2008 to 2010, 844 thyroidectomies for benign thyroid diseases (benign nodules in 447; Graves' disease in 377; huge goiter attributable to Hashimoto thyroiditis in 20) were performed at Noguchi Thyroid Clinic and Hospital Foundation. The otolaryngologists screened all patients for the presence or absence of RLN palsy by laryngoscope, both pre- and postoperatively. When RLN palsy was present, the patients were checked periodically by laryngoscopy without additional drug therapy until the recovery of vocal cord palsy or loss of contact.
Results:
A total of 1,374 nerves were at risk during the thyroid surgery (bilateral risk in 530, unilateral risk in 314). No patient exhibited a bilateral RLN palsy. Unilateral postoperative RLN palsies were found in 45 patients (benign nodules in 25, Graves' disease in 19, and Hashimoto thyroiditis in 1). The RLN was involuntarily amputated in five patients during the operation. The incidence of RLN palsy was 5.3% per patient and 3.3% per nerve. The incidence of RLN palsy was greater in patients who underwent complete unilateral thyroid lobe resection compared with partial resection of the lobe (P = .04). The occurrence of RLN palsy was associated with the need for reoperation caused by postoperative bleeding and the reduced weight of the thyroid remnant in Graves' disease (P = .04 and P = .03, respectively). Among 40 patients with RLN palsy and excluding 5 amputated patients, the RLN palsy resolved in 34 patients (85%) within 12 months after the procedure. The remaining 6 patients (15%) were considered to have permanent RLN palsies.
Conclusion:
Complete resection of the thyroid lobe and reoperation for postoperative bleeding are the risk factors for postoperative RLN palsy in patients with benign thyroid nodules. In Graves' disease, smaller weight of the residual thyroid tissue contributes to the occurrence of RLN palsy. Most RLN palsies that do not require amputation of the nerve resolve spontaneously within 12 months after surgery. In this study, the palsy remained in 1.3% (11/844) of patients.

Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:28
Graves' Disease I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...