Retroperitoneoscopic pyelolithotomy: a minimally invasive alternative for the management of large renal pelvic stone
Related Experiment Video
Updated: May 2, 2026
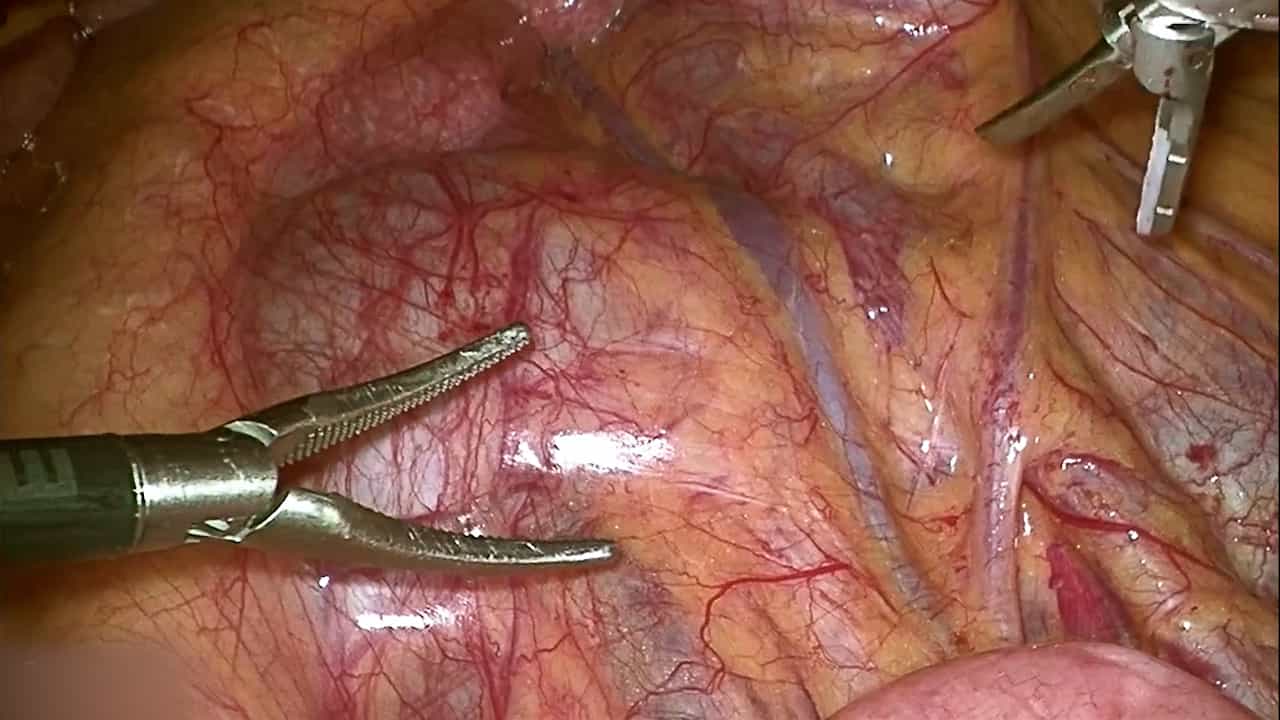
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
Saurabh Sudhir Chipde1, Santosh Agrawal1
1Department of Urology and Renal Transplantation, Sri Aurobindo Institute of Medical Sciences (SAIMS), Indore (M.P.), India.

Introduction:
Large stones in renal pelvis can be treated with percutaneous nephrolithotomy (PCNL) or pyelolithotomy (either by open or laparoscopic techniques). PCNL is difficult in undilated system. For pyelolithotomy, laparoscopy is more preferable over the open surgery. Surgeons are more familiar with the tansperitoneoscopic anatomy than retroperitoneoscopic one, but retroperitoneoscopic approach can be attempted if we anticipate the problems in the transperitoneal route.
Case:
A fifty years old gentleman presented to us with the complaint of dull aching right flank pain. On ultrasonographic examination, he was found to have a large stone in renal pelvis with minimal hydronephrosis and thickened omentum on right side. Xray KUB showed a large radio-opaque shadow in renal area. We did the CECT-Urogram of the patient to know the detailed anatomy, which showed a stone of 5.3 x 3.7 cm in right extra-rena pelvis without hydronephrosis and a large focal area of marked fat stranding in omentum on the right side in mid and lower abdomen with swirling of fat stranding on the superior aspect suggestive of omental infarction and torsion. Due to undilated caliceal system, we preferred laparoscopic surgery over the PCNL in this patient. As whole of the omental tissue was stuck on right side we decided to proceed with transperitoneoscopic route instead of retroperitoneoscopic one. The DJ stent was inserted preoperatively.The surgery was performed in the flank position with three ports, one 10mm port just antero-inferior to tip of 12th rib for camera and two 5mm working ports, one at anterior axillary line and other at renal angle. We created the retroperitoneal space with the customized balloon, made with the glove-fingure.
Results:
The operative time was 1 hour 40 minutes, and there were no intra or post-operative complications. The stone was removed in toto. Patient was orally allowed on first postoperative day and foleys was removed on second day. patient was discharged on day 2. DJ stent was removed after 15 days. At two months follow-up the patient was asymptomatic.
Conclusion:
The retroperitoneoscopic pyelolithotomy is a good alternative for removal of large stone in renal pelvis, with the added advantages of no peritoneal contamination and a quick recovery of bowel function.
More Related Videos
 03:56
A Two-Step Method for Percutaneous Transhepatic Choledochoscopic Lithotomy
Published on: September 13, 2022
 06:39
Technical Modification of the Terminal Ureter During Total Transperitoneal Laparoscopic Nephroureterectomy for Upper Urinary Tract Urothelial Carcinoma
Published on: November 22, 2019
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:30
Urinary Tract Calculi III: Medical Management
 01:28
Urinary Tract Calculi V: Nursing Management
 01:26
Kidney Transplant II: Surgical Procedure