Related Experiment Video
Updated: May 1, 2026


Homogeneous Time-resolved Förster Resonance Energy Transfer-based Assay for Detection of Insulin Secretion
Published on: May 10, 2018
The pharmacokinetic considerations and adverse effects of DPP-4 inhibitors [corrected]
Theodosios D Filippatos1, Vasilios G Athyros, Moses S Elisaf
1Aristotle University of Thessaloniki, Hippokration Hospital, Medical School, Second Propedeutic Department of Internal Medicine , Thessaloniki , Greece.

Introduction:
Dipeptidyl-peptidase-4 (DPP-4) inhibitors are a class of anti-hyperglycemic agents with proven efficacy in patients with type 2 diabetes mellitus (T2DM).
Areas Covered:
This review considers the pharmacokinetic profile, adverse effects and drug interactions of DPP-4 inhibitors. DPP-4 inhibitors have certain differences in their structure, metabolism, route of elimination and selectivity for DPP-4 over structurally related enzymes, such as DPP-8/DPP-9. They have a low potential for drug interactions, with the exception of saxagliptin that is largely metabolized by cytochrome CYP3A4/A5. Reports of pancreatitis and pancreatic cancer have raised concerns regarding the safety of DPP-4 inhibitors and are under investigation. Post-marketing surveillance has revealed less common adverse effects, especially a number of skin- and immune-related adverse effects. These issues are covered in the present review.
Expert Opinion:
DPP-4 inhibitors are useful and efficient drugs. DPP-4 inhibitors have similar mechanism of action and similar efficacy. However, DPP-4 inhibitors have certain differences in their pharmacokinetic properties that may be associated with different clinical effects and adverse event profiles. Although clinical trials indicated a favorable safety profile, post-marketing reports revealed certain safety aspects that need further investigation. Certainly, more research is needed to clarify if the differences among DPP-4 inhibitors could lead to a different clinical and safety profile.


Related Concept Videos
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
 01:25
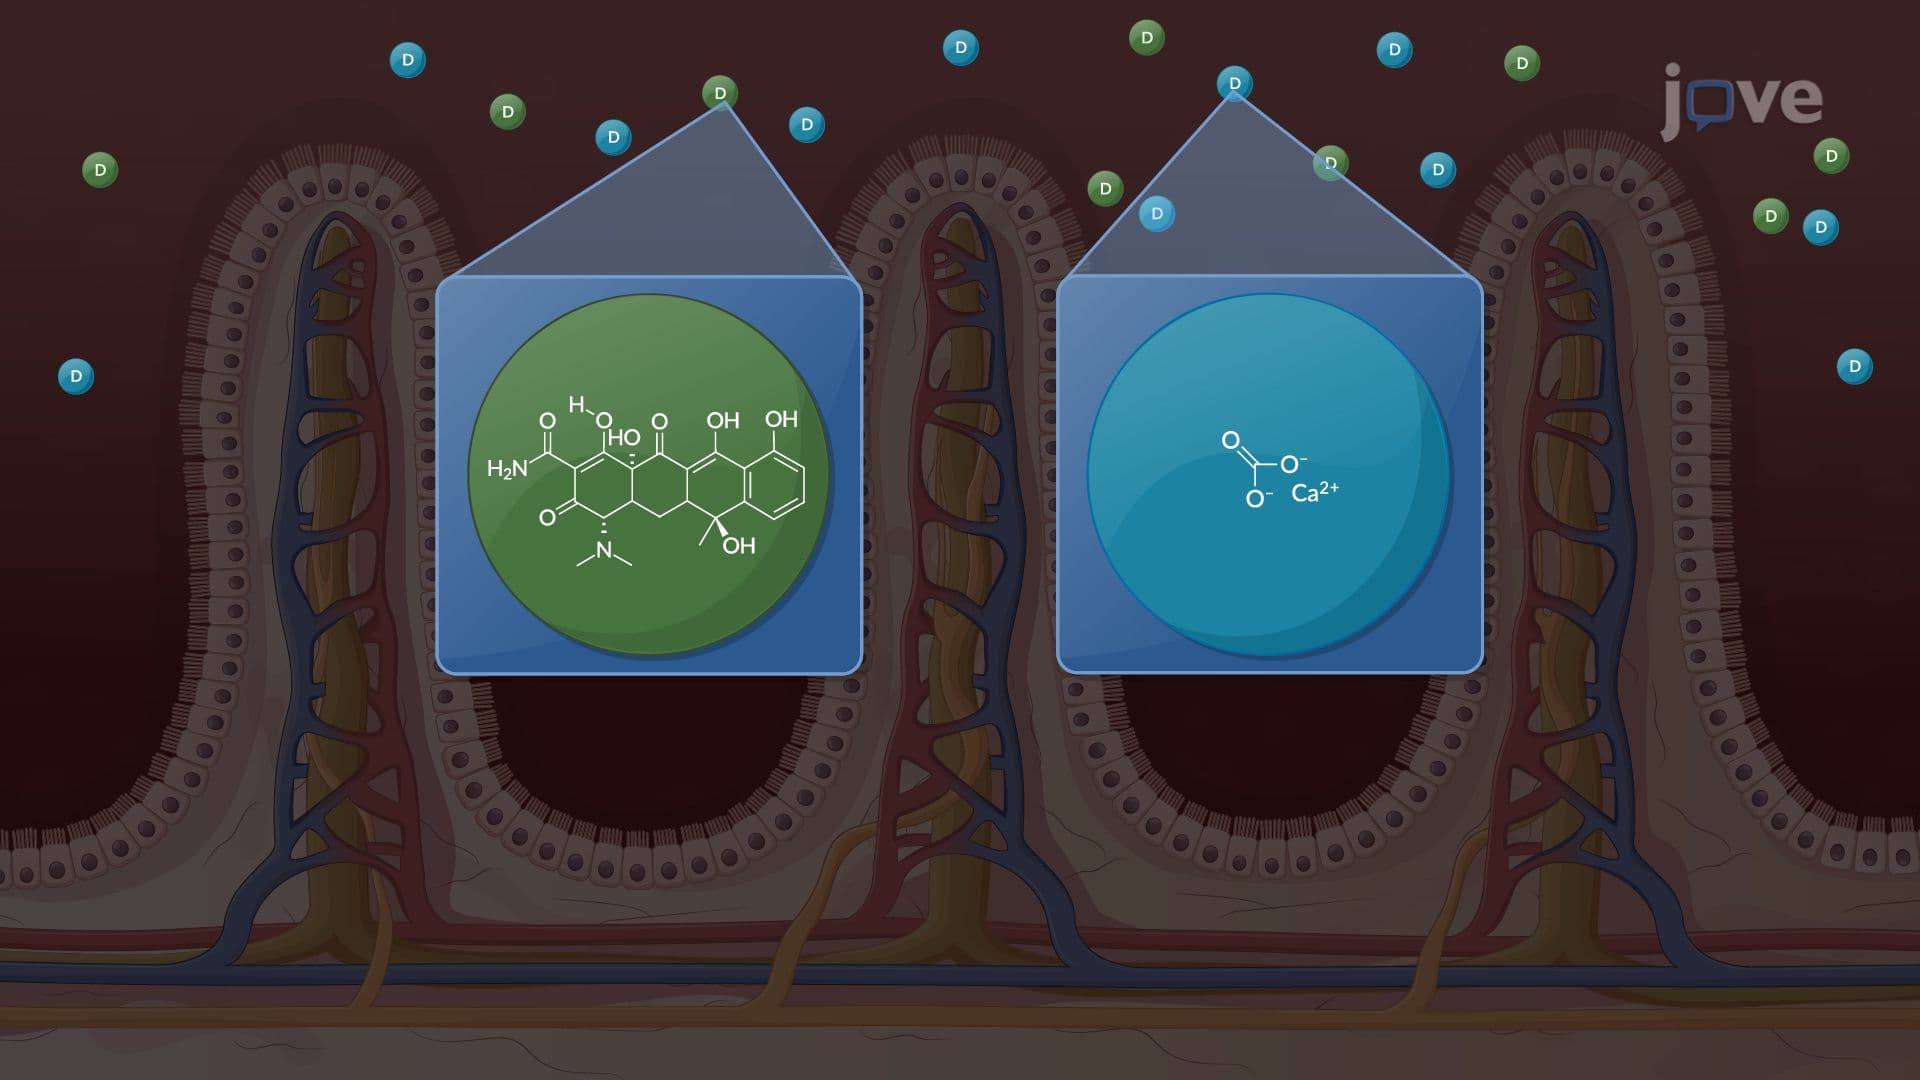
Pharmacokinetics: Drug–Drug Interactions
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones