Related Experiment Video
Updated: Apr 30, 2026


A Detailed Protocol for Physiological Parameters Acquisition and Analysis in Neurosurgical Critical Patients
Published on: October 17, 2017
Control of blood pressure in hypertensive neurological emergencies
Lisa Manning1, Thompson G Robinson, Craig S Anderson
1Department of Cardiovascular Sciences and NIHR Biomedical Research Unit in Cardiovascular Disease, University of Leicester, Leicester, UK, lm313@le.ac.uk.

Neurological hypertensive emergencies cause significant morbidity and mortality. Most occur in the setting of ischaemic stroke, spontaneous intracerebral hemorrhage (ICH), or subarachnoid hemorrhage (SAH), but other causes relate to hypertensive encephalopathy and reversible cerebral vasoconstriction syndrome (RCVS). Prompt and controlled reduction of blood pressure (BP) is necessary, although there remains uncertainty as to the optimal rate of decline and ideal antihypertensive agent. There is probably no single treatment strategy that covers all neurological hypertensive emergencies. Prompt diagnosis of the underlying disorder, recognition of its severity, and appropriate targeted treatment are required. Lack of comparative-effectiveness data leaves clinicians with limited evidence-based guidance in management, although significant developments have occurred recently in the field. In this article, we review the management of specific neurological hypertensive emergencies, with particular emphasis on recent evidence.
Neurological hypertensive emergencies cause significant morbidity and mortality. Most occur in the setting of ischaemic stroke, spontaneous intracerebral hemorrhage (ICH), or subarachnoid hemorrhage (SAH), but other causes relate to hypertensive encephalopathy and reversible cerebral vasoconstriction syndrome (RCVS). Prompt and controlled reduction of blood pressure (BP) is necessary, although there remains uncertainty as to the optimal rate of decline and ideal antihypertensive agent. There is probably no single treatment strategy that covers all neurological hypertensive emergencies. Prompt diagnosis of the underlying disorder, recognition of its severity, and appropriate targeted treatment are required. Lack of comparative-effectiveness data leaves clinicians with limited evidence-based guidance in management, although significant developments have occurred recently in the field. In this article, we review the management of specific neurological hypertensive emergencies, with particular emphasis on recent evidence.
More Related Videos
 09:00
Real-Time Monitoring and Modulation of Blood Pressure in a Rabbit Model of Ischemic Stroke
Published on: February 10, 2023
 06:51
Development of an Algorithm to Perform a Comprehensive Study of Autonomic Dysreflexia in Animals with High Spinal Cord Injury Using a Telemetry Device
Published on: July 29, 2016
Related Concept Videos
 01:23
Hypertension V: Nursing Management
 01:18
Hypertension and Regulation of Blood Pressure
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:30
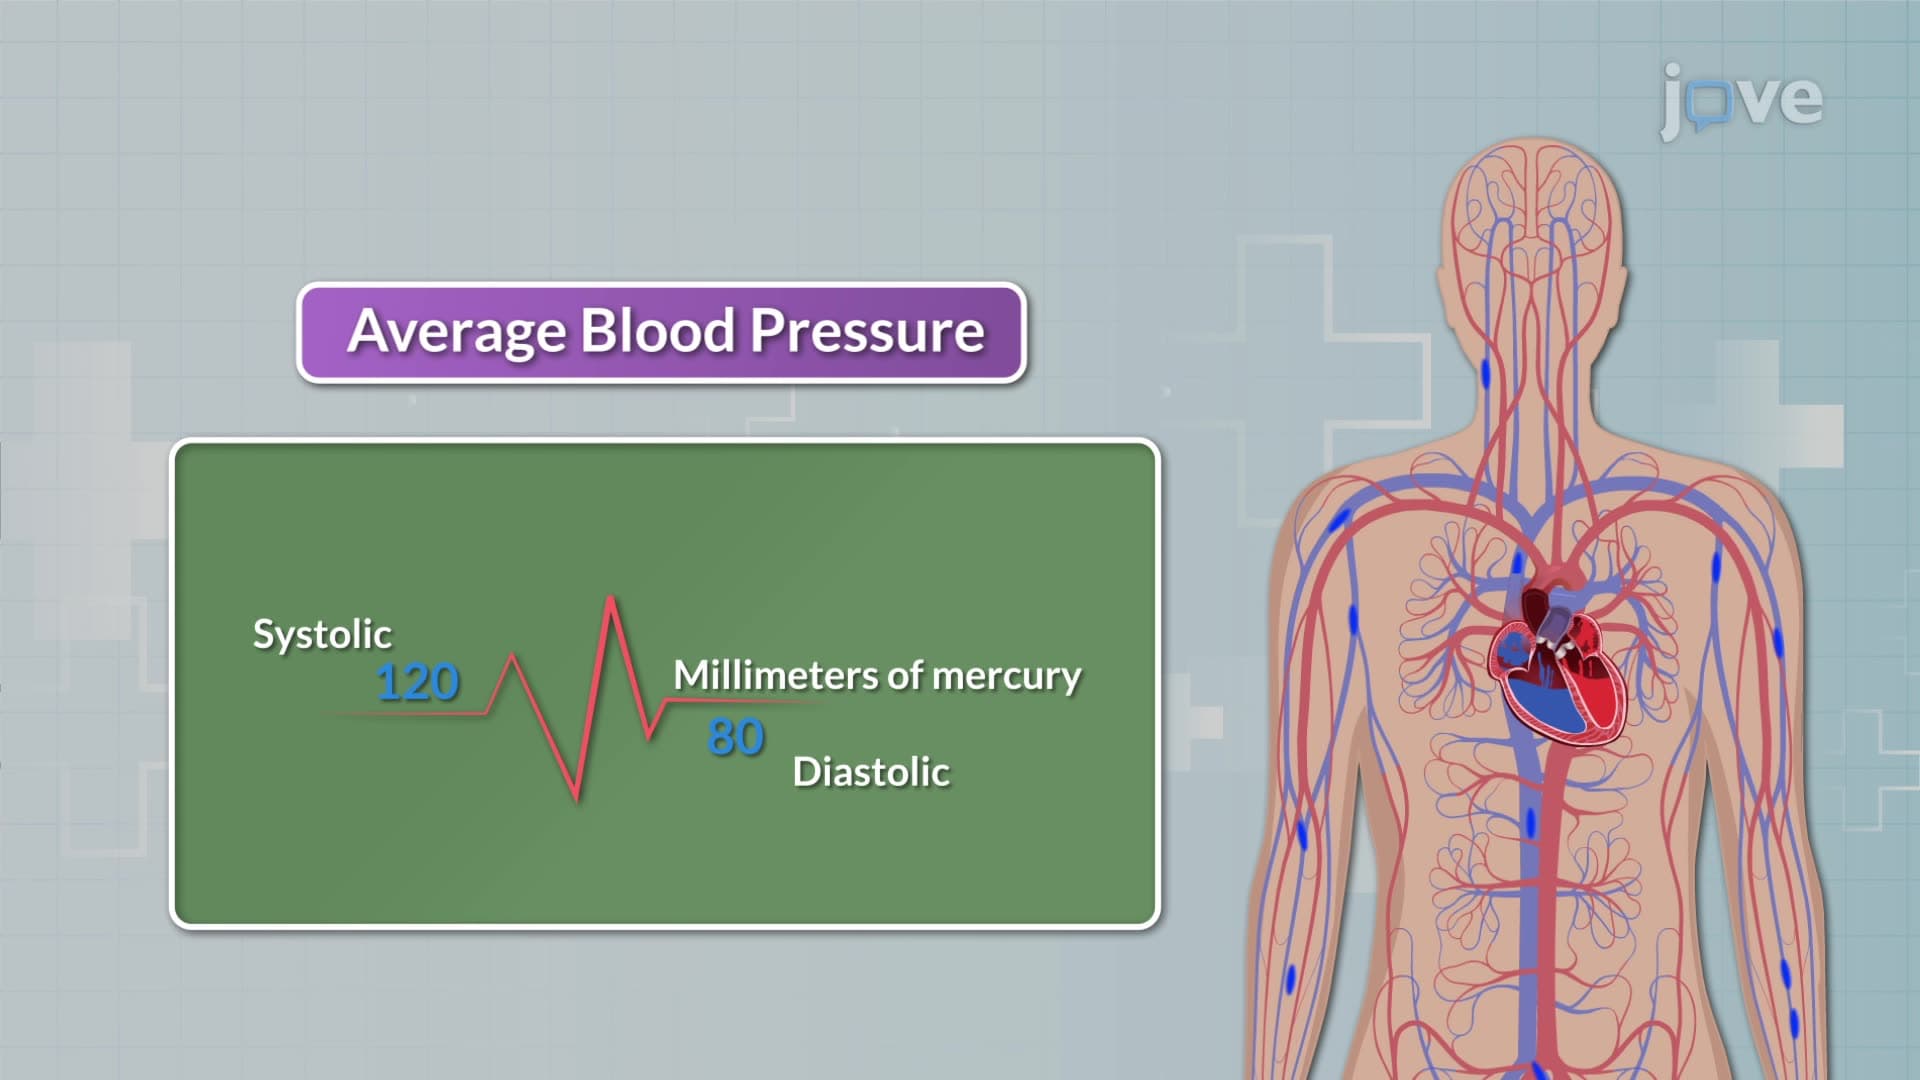
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:28
Hypertension I: Introduction
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...