Related Experiment Video
Updated: Apr 28, 2026

Fecal Microbiota Transplantation via Colonoscopy for Recurrent C. difficile Infection
Published on: December 8, 2014
Fecal microbiota transplant for treatment of Clostridium difficile infection in immunocompromised patients
Colleen R Kelly1, Chioma Ihunnah1, Monika Fischer2
1Division of Gastroenterology, Brown Alpert Medical School, Women's Medicine Collaborative, Alpert Medical School of Brown University, Providence, Rhode Island, USA.

Objectives:
Patients who are immunocompromised (IC) are at increased risk of Clostridium difficile infection (CDI), which has increased to epidemic proportions over the past decade. Fecal microbiota transplantation (FMT) appears effective for the treatment of CDI, although there is concern that IC patients may be at increased risk of having adverse events (AEs) related to FMT. This study describes the multicenter experience of FMT in IC patients.
Methods:
A multicenter retrospective series was performed on the use of FMT in IC patients with CDI that was recurrent, refractory, or severe. We aimed to describe rates of CDI cure after FMT as well as AEs experienced by IC patients after FMT. A 32-item questionnaire soliciting demographic and pre- and post-FMT data was completed for 99 patients at 16 centers, of whom 80 were eligible for inclusion. Outcomes included (i) rates of CDI cure after FMT, (ii) serious adverse events (SAEs) such as death or hospitalization within 12 weeks of FMT, (iii) infection within 12 weeks of FMT, and (iv) AEs (related and unrelated) to FMT.
Results:
Cases included adult (75) and pediatric (5) patients treated with FMT for recurrent (55%), refractory (11%), and severe and/or overlap of recurrent/refractory and severe CDI (34%). In all, 79% were outpatients at the time of FMT. The mean follow-up period between FMT and data collection was 11 months (range 3-46 months). Reasons for IC included: HIV/AIDS (3), solid organ transplant (19), oncologic condition (7), immunosuppressive therapy for inflammatory bowel disease (IBD; 36), and other medical conditions/medications (15). The CDI cure rate after a single FMT was 78%, with 62 patients suffering no recurrence at least 12 weeks post FMT. Twelve patients underwent repeat FMT, of whom eight had no further CDI. Thus, the overall cure rate was 89%. Twelve (15%) had any SAE within 12 weeks post FMT, of which 10 were hospitalizations. Two deaths occurred within 12 weeks of FMT, one of which was the result of aspiration during sedation for FMT administered via colonoscopy; the other was unrelated to FMT. None suffered infections definitely related to FMT, but two patients developed unrelated infections and five had self-limited diarrheal illness in which no causal organism was identified. One patient had a superficial mucosal tear caused by the colonoscopy performed for the FMT, and three patients reported mild, self-limited abdominal discomfort post FMT. Five (14% of IBD patients) experienced disease flare post FMT. Three ulcerative colitis (UC) patients underwent colectomy related to course of UC >100 days after FMT.
Conclusions:
This series demonstrates the effective use of FMT for CDI in IC patients with few SAEs or related AEs. Importantly, there were no related infectious complications in these high-risk patients.


Related Concept Videos
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:27
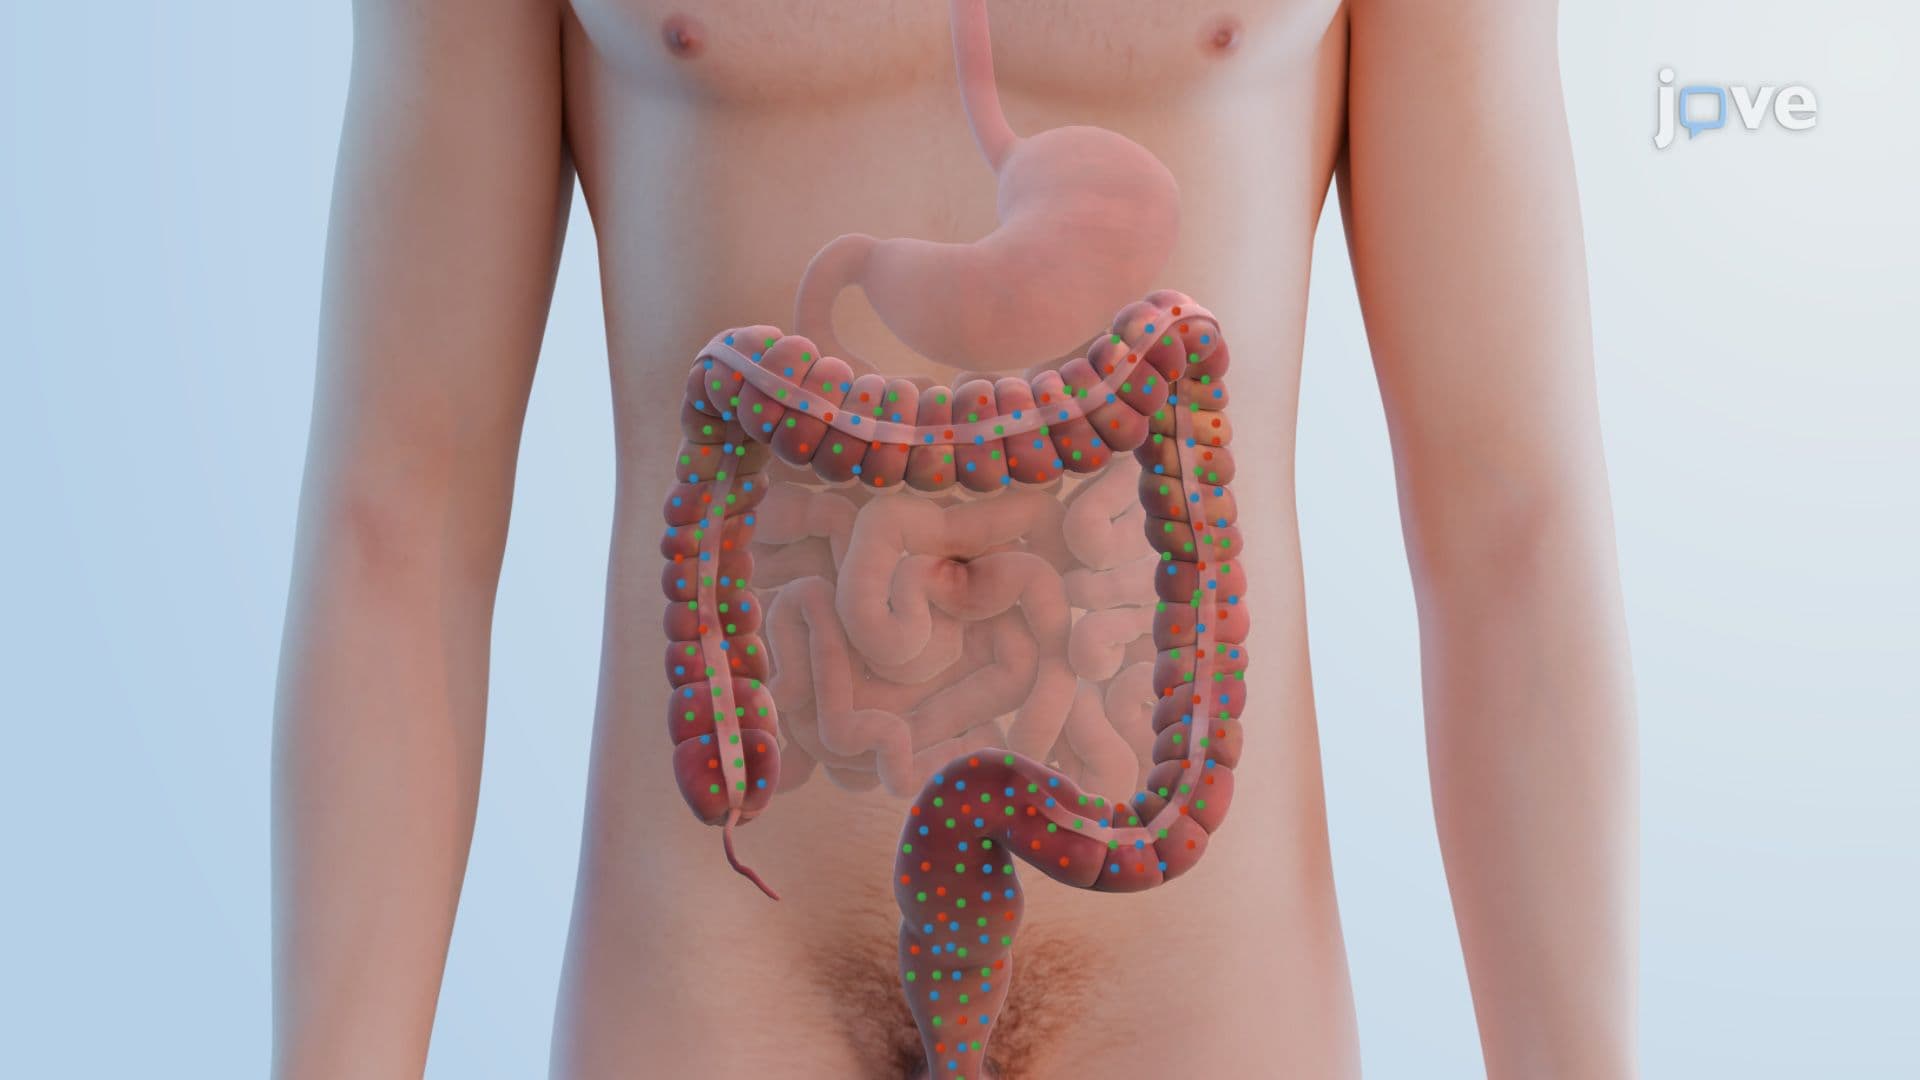
Microbiota of the Large Intestine
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:30
Development of Human Microbiota
 01:21
Drugs for Treatment of Constipation-Predominant IBS
 01:22
Introduction to the Human Microbiota