Related Experiment Video
Updated: Mar 1, 2026

Isolation of Human Lymphatic Endothelial Cells by Multi-parameter Fluorescence-activated Cell Sorting
Published on: May 1, 2015
The natural history of intravascular lymphomatosis
Ekokobe Fonkem1, Edwin Lok, David Robison
1Brain Tumor Center and Neuro-Oncology Unit, Department of Neurology, Beth Israel Deaconess Medical Center, Boston, Massachusetts.

Abstract:
Intravascular lymphomatosis (IVL) is a rare and clinically devastating form of extranodal B-cell non-Hodgkin's lymphoma. We performed a comprehensive analysis of the literature on IVL's published between 1959 and 2011 and evaluated the natural history as well as identified prognostic and predictive factors in patients. Nonparametric two-tailed Mann-Whitney U-test and Mantel-Cox log rank test were used to evaluate the survival intervals and prognostic factors. Multivariate analysis of variance (MANOVA) and chi-squared statistics were carried out to examine treatment-related predictive factors. Of the 740 patients with IVL, 651 (88%) had a diagnosis of B-cell lymphoma, 45 (6%) with T-cell lymphoma, and 12 patients (2%) with NK cell lymphoma. Central nervous system (CNS) IVL had the highest proportion of postmortem diagnosis, 250 (60%) compared to 21 (8%) of skin, 28 (11%) of bone marrow (BM) and spleen, and 17 (7%) of lung IVL's. Age <70 years (P = 0.0073), non-CNS site of initial diagnosis (P = 0.0014), lactate dehydrogenase (LDH) <700 (P = 0.0112), and rituximab treatment (P < 0.0001) were favorable prognostic factors. Gender, ethnicity, hemoglobin, BM biopsy, and the type of imaging studies used were not significant. Rituximab and doxorubicin treatment worked significantly better in patients with age >71 and LDH >577 compared to nonrituximab, nondoxorubicin regimens (MANOVA 2 degrees of freedom, P = 0.0345), with a median time from treatment to death of 20.0 (95% confidence interval [CI] 14.0-N/A, n = 14) months versus 2.0 (95%CI 0.5-N/A, n = 5) (χ(2) = 4.7, P = 0.0304). Patients with CNS IVL relapsed primarily in the CNS (88%) while same-organ relapse occurred less frequently in skin (23%), BM and spleen (50%) and lung (20%) IVL's. Our results indicate that IVL is primarily a disease of B-lymphoma cells. Timely diagnosis and treatment with rituximab-based chemotherapy improve patient survival. The pattern of recurrence is different between CNS IVL and IVL's in other organs.
Related Concept Videos
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular...
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:15
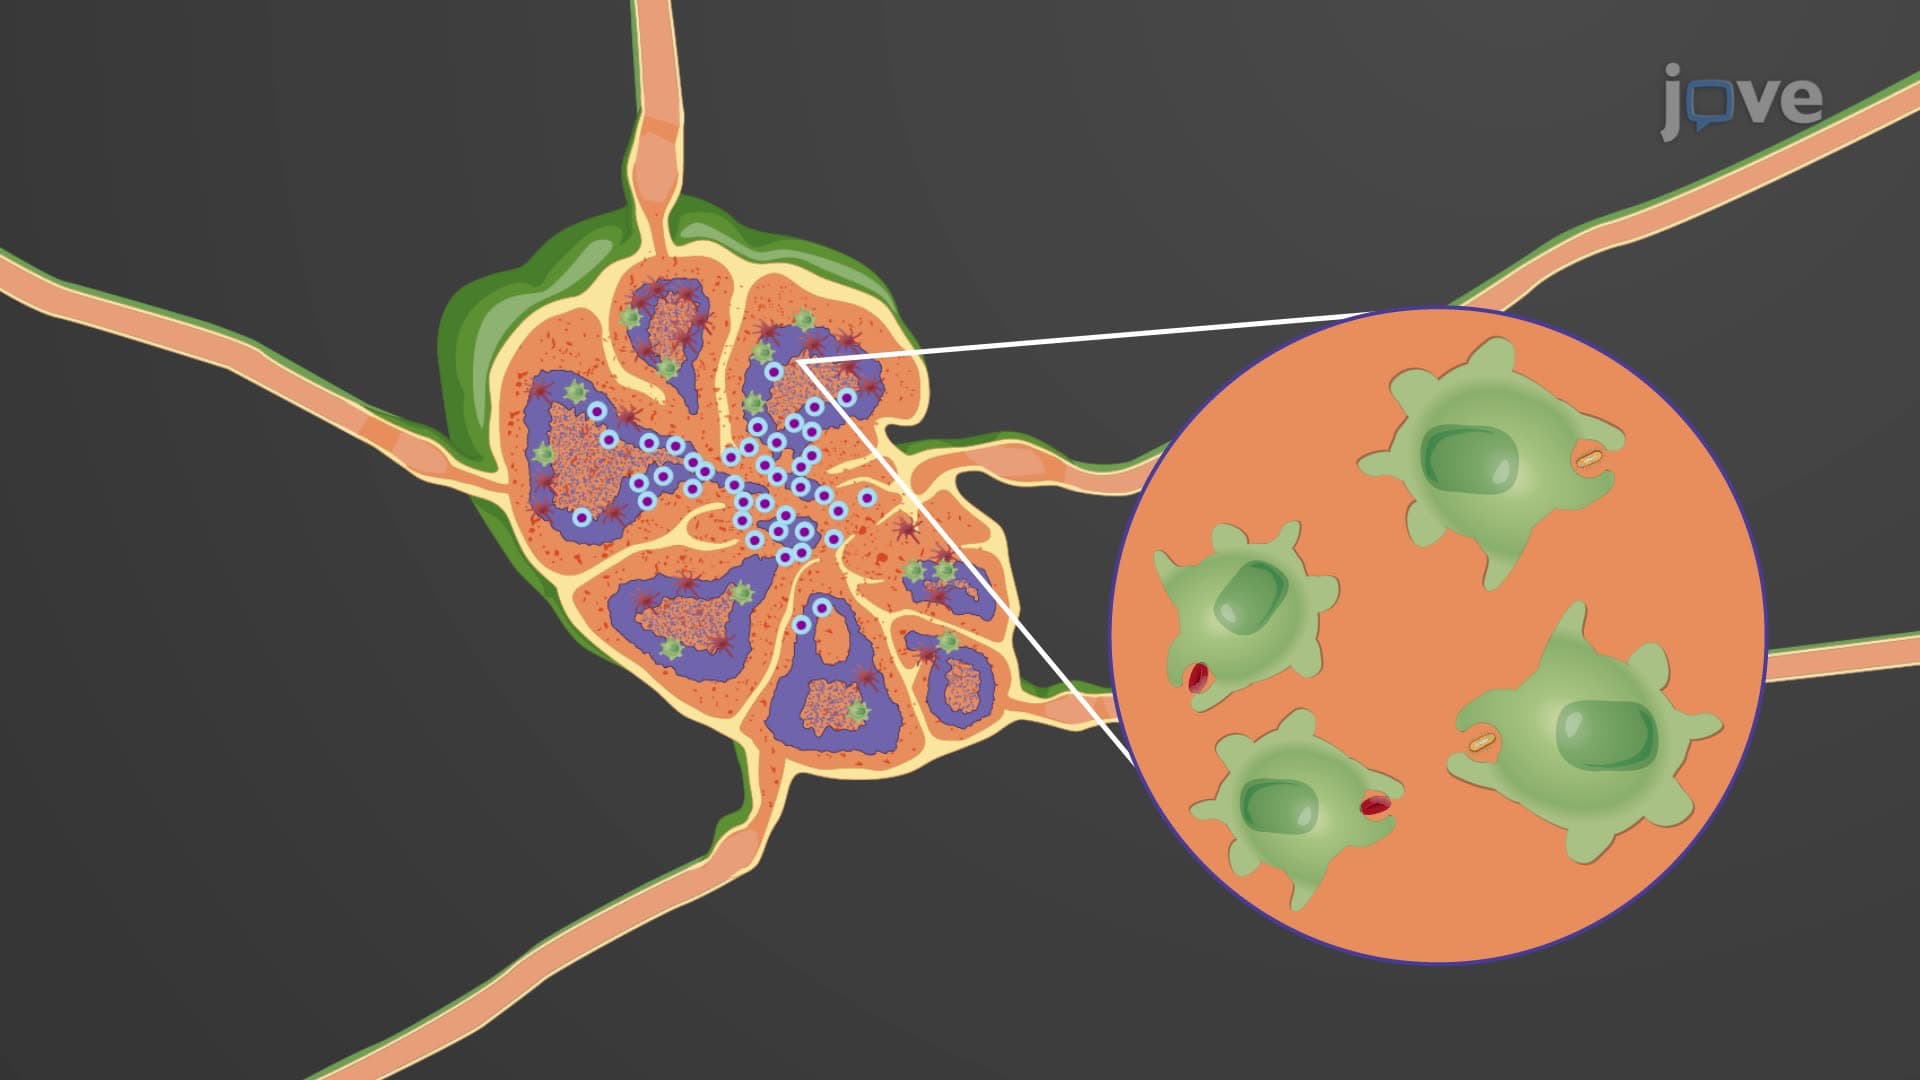
Secondary Lymphoid Organs
The spleen is a vital organ in the lymphatic system, nestled in the upper left side of the abdomen. It is composed of two primary regions: the red pulp and the white pulp, each having distinct functions. The red pulp performs a significant role in blood filtration. It efficiently purges the blood of old or damaged red blood cells and...
 01:16
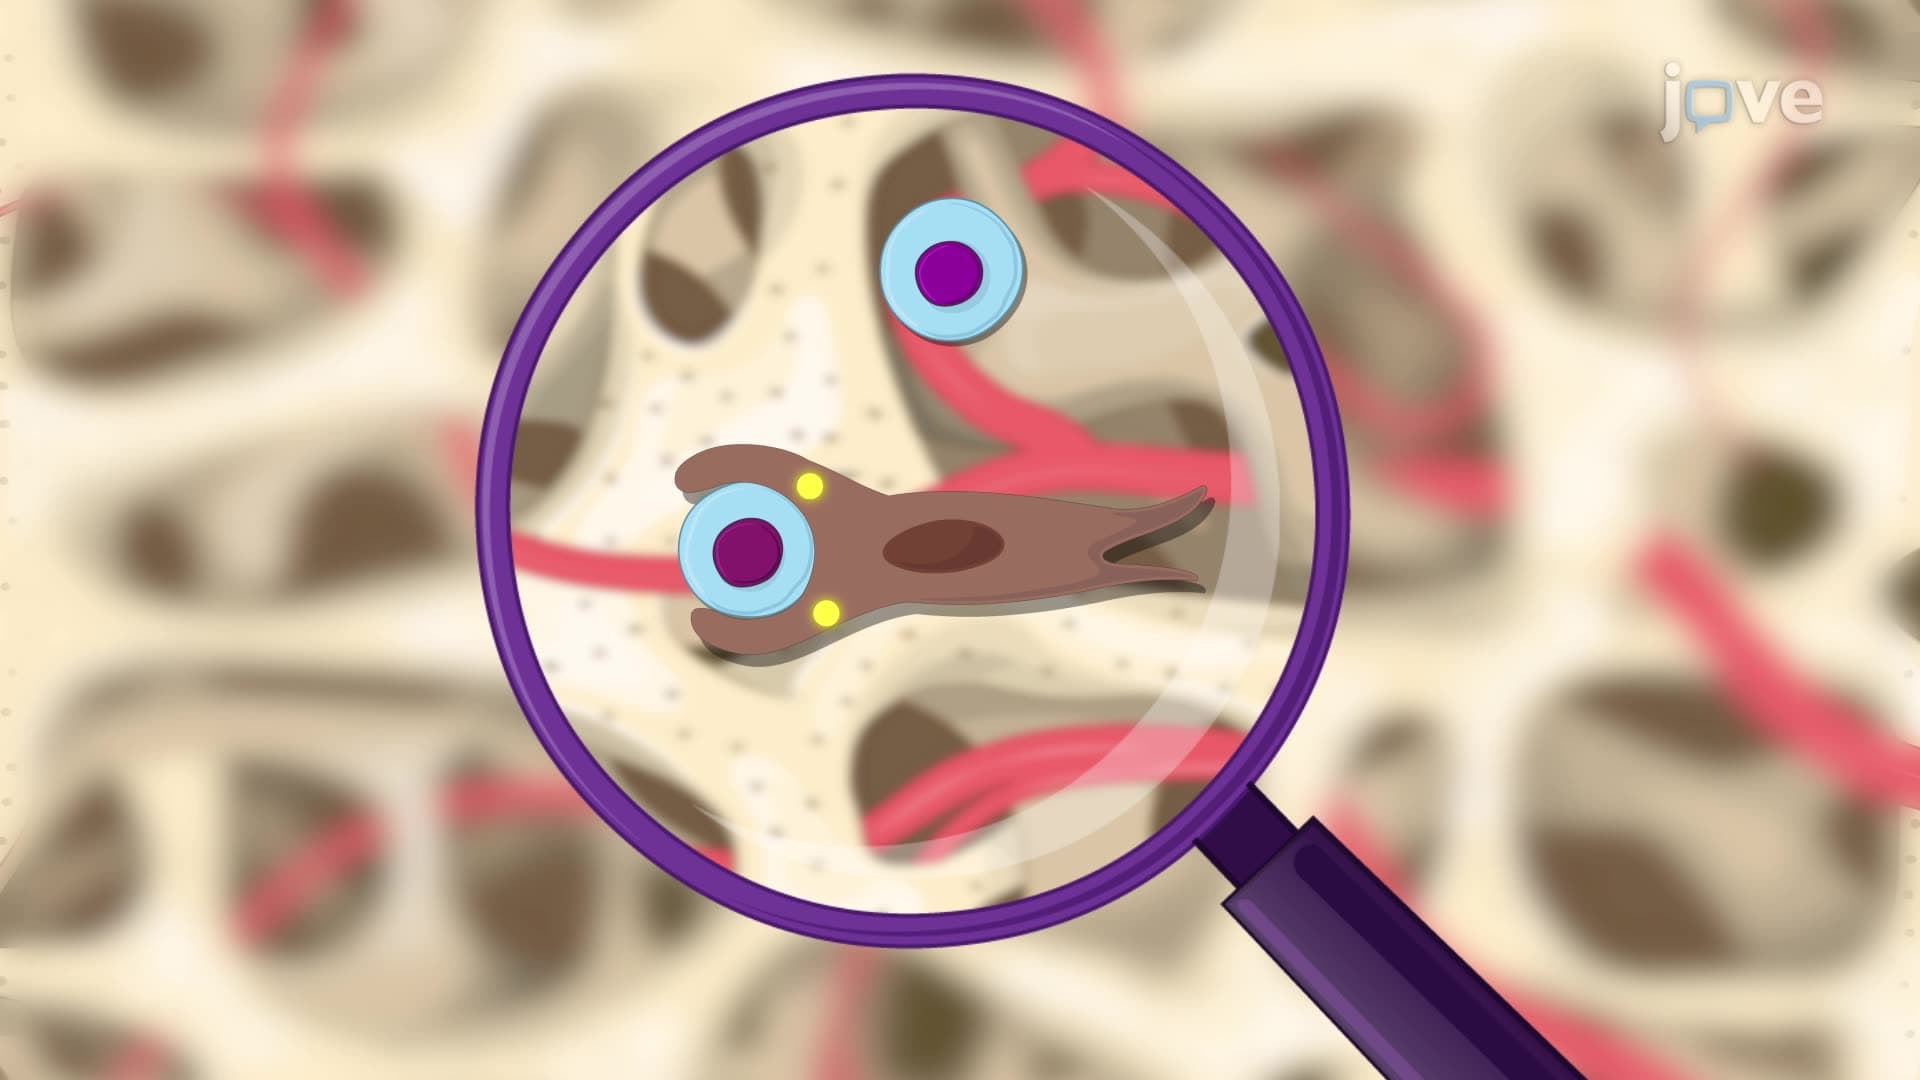
Primary Lymphoid Organs
The red bone marrow is a soft, spongy tissue nestled in the interior of long bones such as the humerus and femur. It is the site...