
Detection of culprit coronary lesion location in pre-hospital 12-lead ECG
Richard E Gregg1, Saeed Babaeizadeh1
1Advanced Algorithm Research Center, Philips Healthcare, Andover, MA, USA.

Insights
An automated system reliably determines culprit lesion location from pre-hospital electrocardiograms (ECGs), improving ST-segment elevation myocardial infarction (STEMI) care. This technology aids in identifying critical blockages, potentially reducing treatment times for heart attacks.
Area of Science:
- Cardiology
- Medical Technology
- Artificial Intelligence in Medicine
Background:
- Pre-hospital 12-lead ECG interpretation is crucial for timely ST-segment elevation myocardial infarction (STEMI) treatment.
- Identifying culprit lesion location (e.g., proximal LAD) in STEMI can indicate higher risk.
- Noisy pre-hospital ECGs pose challenges for automated STEMI detection and lesion localization.
Purpose of the Study:
- To develop and evaluate an automated system for classifying culprit lesion location (proximal LAD, LAD, RCA, LCx) from pre-hospital 12-lead ECGs.
- To assess the system's performance in a challenging pre-hospital environment.
Main Methods:
- A three-classifier system was designed: LAD vs. non-LAD, RCA vs. LCx, and proximal vs. non-proximal LAD.
- The system was trained on emergency department ECGs (n=181) and tested on pre-hospital ECGs (n=80).
- Performance metrics included sensitivity, specificity, and positive predictive value.
Main Results:
- High specificity and PPV were achieved for proximal LAD, LAD, and LCx classifications.
- Sensitivity, Specificity, and PPV for proximal LAD were 50%, 100%, 100%; for all LAD were 90%, 100%, 100%; for RCA were 98%, 72%, 78%; and for LCx were 50%, 98%, 90% respectively.
- The RCA classifier was designed with lower specificity to prioritize LCx classification accuracy.
Conclusions:
- Automated determination of culprit lesion location from pre-hospital ECGs appears reliable, despite limitations of the test database size.
- Further research is warranted to assess the clinical impact of this automated system on patient treatment and outcomes.
Background:
Pre-hospital 12-lead ECG interpretation is important because pre-hospital activation of the coronary catheterization laboratory reduces ST-segment elevation myocardial infarction (STEMI) discovery-to-treatment time. In addition, some ECG features indicate higher risk in STEMI such as proximal left anterior descending (LAD) culprit lesion location. The challenging nature of the pre-hospital environment can lead to noisier ECGs which make automated STEMI detection difficult. We describe an automated system to classify lesion location as proximal LAD, LAD, right coronary artery (RCA) and left circumflex (LCx) and test the performance on pre-hospital 12-lead ECG.
Methods:
The overall classifier was designed from three linked classifiers to separate LAD from non-LAD (RCA or LCx) in the first step, RCA from LCx in a second classifier and proximal from non-proximal LAD in the third classifier. The proximal LAD classifier was designed for high specificity because the output may be used in the decision to modify treatment. The LCx classifier was designed for high specificity because RCA is dominant in most people. The system was trained on a set of emergency department ECGs (n=181) and tested on a set of pre-hospital ECGs (n=80). Both sets were based on a sequential sample starting with symptoms suggesting acute coronary syndromes. Culprit lesion location was determined from coronary catheterization laboratory reports. Inclusion criteria included STEMI interpretation by computer and culprit lesion with 70% or more narrowing. Algorithm accuracy was measured on the test set by sensitivity (SE), specificity (SP), and positive predictive value (PPV).
Results:
SE, SP and PPV were 50, 100 and 100% respectively for proximal LAD lesion location; 90, 100 and 100% for all LAD; 98, 72 and 78% for RCA; and 50, 98 and 90% for LCx. Specificity and PPV were high for proximal LAD, LAD and LCx. Specificity and PPV are not as high for RCA by design since the RCA-LCx tradeoff favors high specificity in LCx.
Conclusion:
Although our test database is not large, algorithm performance suggests culprit lesion location can be reliably determined from pre-hospital ECG. Further research is needed however to evaluate the impact of automated culprit lesion location on patient treatment and outcomes.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:28
Electrocardiogram Fundamentals
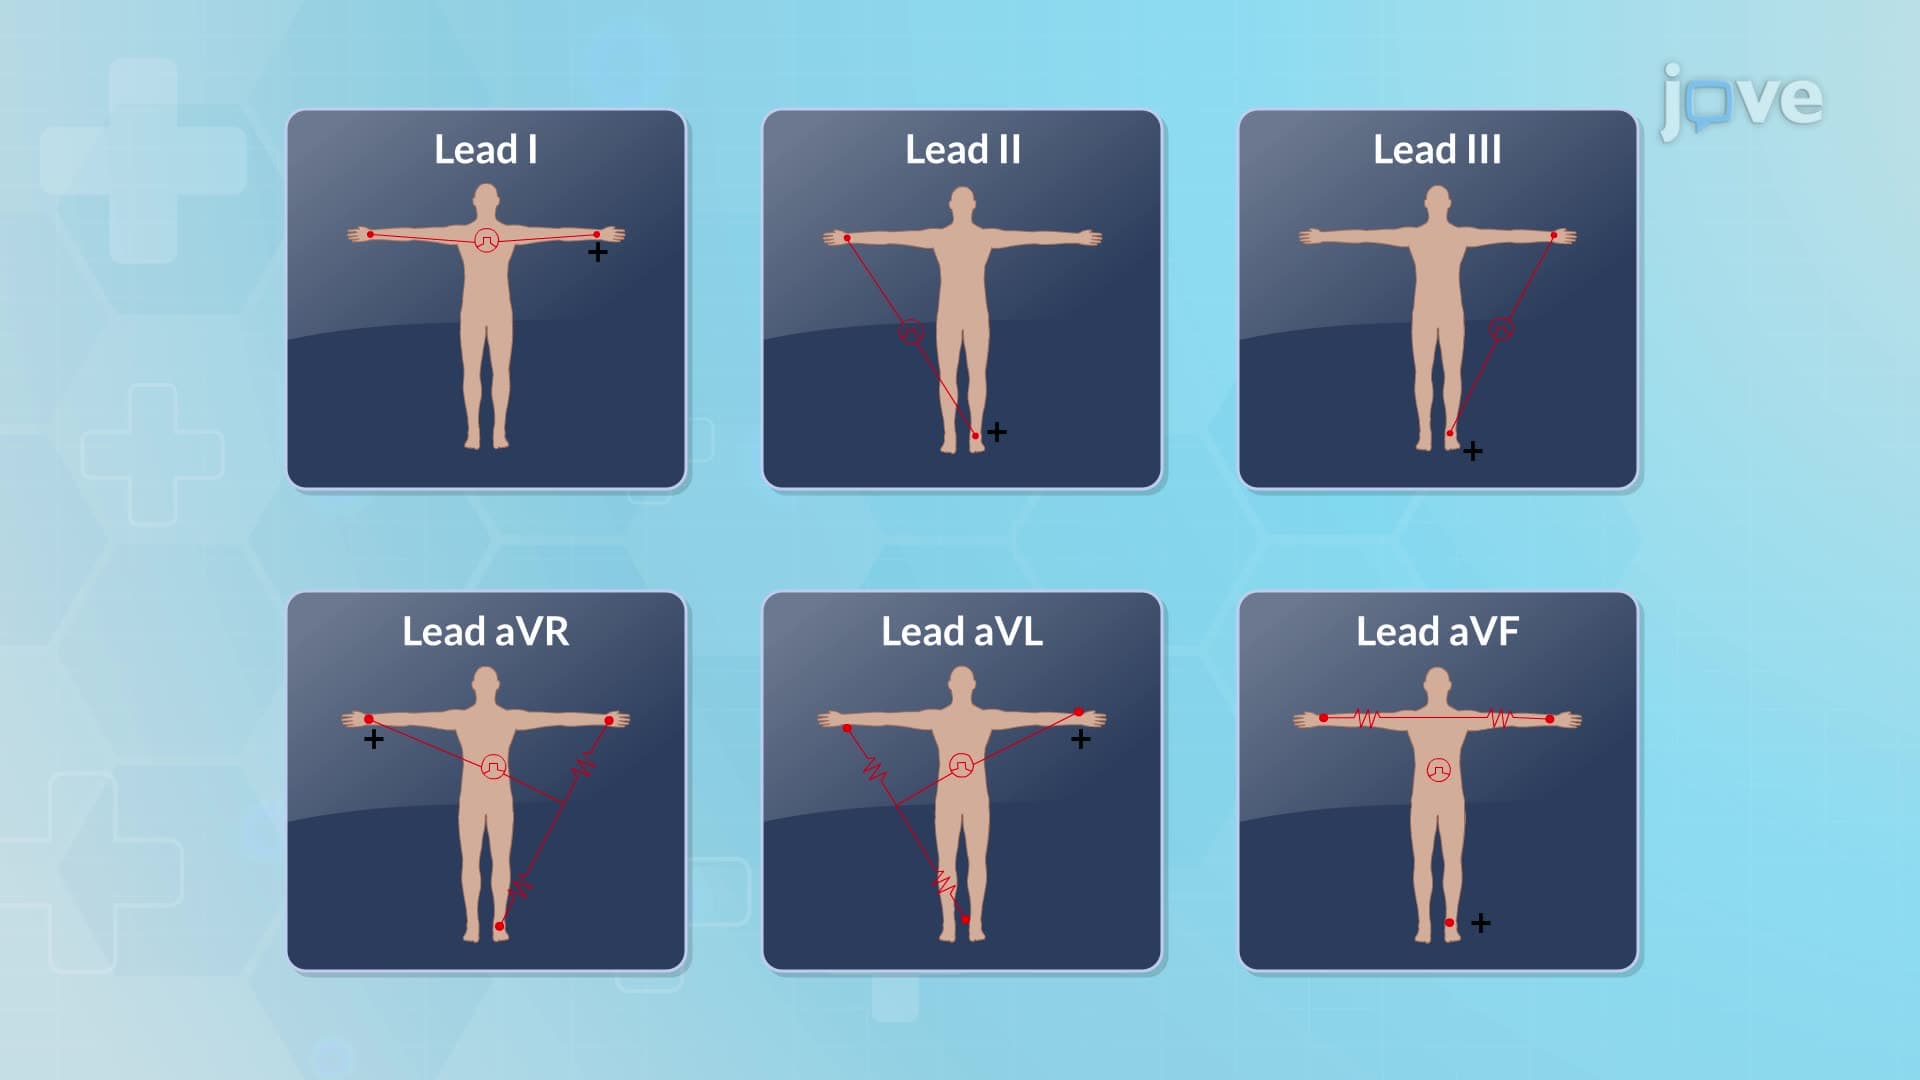
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:30
Acute Coronary Syndrome I: Introduction
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations