Related Experiment Video
Updated: Apr 23, 2026


Learning Modern Laryngeal Surgery in a Dissection Laboratory
Published on: March 18, 2020
Pharyngocutaneous fistula after total laryngectomy: a single-institution experience, 2001-2012
Eleni M Benson1, Richard M Hirata2, Carol B Thompson3
1Department of Otolaryngology-Head and Neck Surgery, Johns Hopkins Medical Institutions, 601 N. Caroline Street, 6th floor, Baltimore, MD, United States.

Purpose:
The purpose of this study was to determine the incidence of and risk factors for pharyngocutaneous fistula in patients undergoing total laryngectomy at a single institution.
Materials And Methods:
The records of 59 patients undergoing primary or salvage total laryngectomy at our institution from 2001 to 2012 were retrospectively reviewed. Data collected included patient, tumor and treatment characteristics, and surgical technique. Risk factors were analyzed for association with pharyngocutaneous fistula formation.
Results:
Twenty patients (34%) developed fistulas. Preoperative tracheostomy (OR 4.1; 95% CI 1.3-13 [p=0.02]) and low postoperative hemoglobin (OR 9.1; 95% CI 1.1-78 [p=0.04]) were associated with fistula development. Regarding surgical technique, primary sutured closure of the total laryngectomy defect had the lowest fistula rate (11%). In comparison, primary stapled closure and pectoralis onlay flap over primary closure had nonsignificantly increased fistula rates (43%, OR 6.0; 95% CI 1.0-37.3 [p=0.06] and 25%, OR 2.7; 95% CI 0.4-23.9 [p=0.38], respectively). Pectoralis flap incorporated into the suture line had a significantly increased fistula rate (50%, OR 7.1; 95% CI 1.4-46 [p=0.02]). After stratification for salvage status, patient comorbidities were associated with fistula in non-salvage cases whereas disease-related characteristics were associated with fistula in salvage cases. Fistula development was associated with increased length of hospital stay (p<0.001) and increased time before oral diet initiation (p<0.001).
Conclusions:
Pharyngocutaneous fistula is a common complication of total laryngectomy. Preoperative tracheostomy, postoperative hemoglobin, and surgical technique are important in determining the risk of fistula.

Related Concept Videos
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:20
Pharynx
Nasopharynx
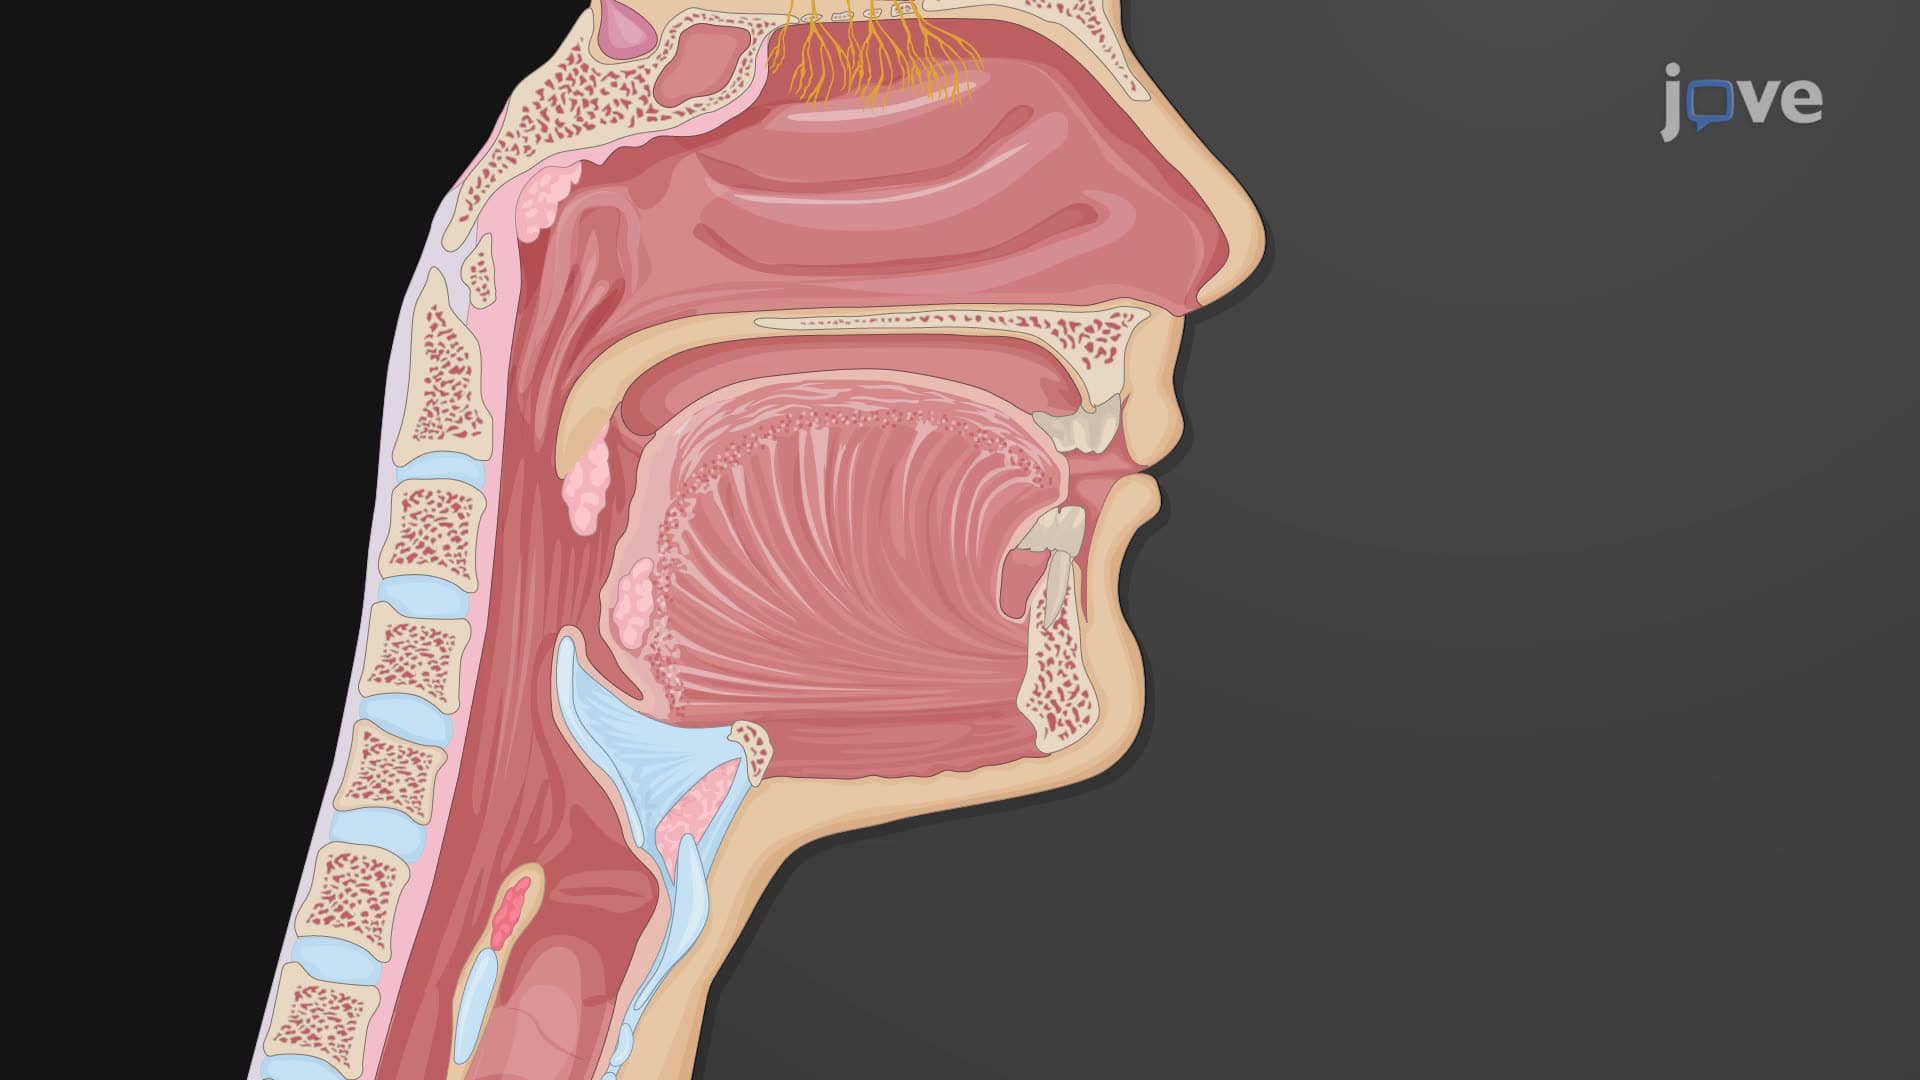
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques