Related Experiment Video
Updated: Apr 21, 2026


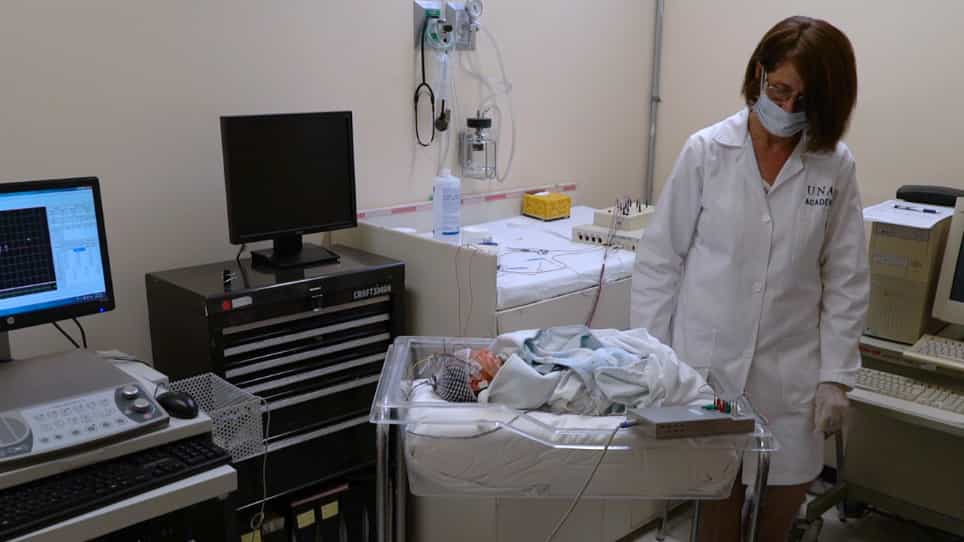
Electroretinogram Recording for Infants and Children under Anesthesia to Achieve Optimal Dark Adaptation and International Standards
Published on: September 3, 2020
Vigabatrin retinal toxicity in children with infantile spasms: An observational cohort study
Carol A Westall1, Tom Wright2, Filomeno Cortese2
1From the Department of Ophthalmology and Vision Science (C.A.W., T.W., A.K., J.R.B.), and Faculty of Medicine (O.C.S.), The Hospital for Sick Children, University of Toronto (C.A.W., J.R.B., O.C.S.); and Hotchkiss Brain Institute, University of Calgary (F.C.), Canada. Carol.westall@sickkids.ca fcortese@ucalgary.ca.

Insights
Limiting vigabatrin (VGB) treatment to six months significantly reduces the risk of VGB-induced retinal damage in infants with infantile spasms (IS). This study highlights duration as a key factor in VGB-RD.
Area of Science:
- Ophthalmology
- Pediatric Neurology
- Clinical Electrophysiology
Background:
- Infantile spasms (IS) is an early infancy epilepsy syndrome.
- Vigabatrin (VGB) is a common treatment for IS.
- VGB can cause retinal damage (VGB-RD).
Purpose of the Study:
- Determine the time course of VGB-induced retinal damage (VGB-RD) in children with IS.
- Identify risk factors associated with VGB-RD.
Main Methods:
- Observational cohort study of 146 infants with IS treated with VGB.
- Electroretinograms (ERGs) were used to assess retinal function.
- Kaplan-Meier survival analysis was employed to evaluate VGB treatment duration and VGB-RD.
Main Results:
- 21% of participants developed VGB-RD.
- ERG amplitudes decreased with VGB treatment duration (p=0.0004).
- 5.3% and 13.3% developed VGB-RD after 6 and 12 months of VGB, respectively; no recovery was observed after VGB cessation.
Conclusions:
- Minimizing VGB treatment duration to 6 months is recommended.
- This strategy is expected to reduce the prevalence of VGB-RD in IS patients.
Objectives:
To determine time to vigabatrin (VGB, Sabril; Lundbeck, Deerfield, IL) induced retinal damage in children with infantile spasms (IS) and to identify risk factors for VGB-induced retinal damage (VGB-RD).
Methods:
Observational cohort study including 146 participants (68 female, 81 male) with IS, an age-specific epilepsy syndrome of early infancy, treated with VGB. Participants ranged from 3 to 34.9 months of age (median 7.6 months). The median duration of VGB treatment was 16 months (range 4.6-78.5 months). Electroretinograms (ERGs) were performed according to the Standards of the International Society for Clinical Electrophysiology of Vision. Inclusion required baseline (pre-VGB or within 4 weeks of starting VGB treatment) and at least 2 follow-up ERGs. Significant reduction from baseline of the 30-Hz ERG flicker amplitude on 2 consecutive visits identified VGB-RD. Kaplan-Meier survival analyses depicted the effect of duration of VGB on VGB-RD.
Results:
These data represent the largest survival analysis of children treated with VGB who did not succumb to retinal toxicity during the study. Thirty of the 146 participants (21%) showed VGB-RD. The ERG amplitude reduced with duration of VGB treatment (p = 0.0004) with no recovery after VGB cessation. With 6 and 12 months of VGB treatment, 5.3% and 13.3%, respectively, developed VGB-RD. There was neither effect of age of initiation of VGB treatment nor sex of the child on survival statistics and no significant effect of cumulative dosage on the occurrence of VGB-RD.
Conclusions:
Minimizing VGB treatment to 6 months will reduce the prevalence of VGB-RD in patients with IS.