Related Experiment Video
Updated: Apr 17, 2026
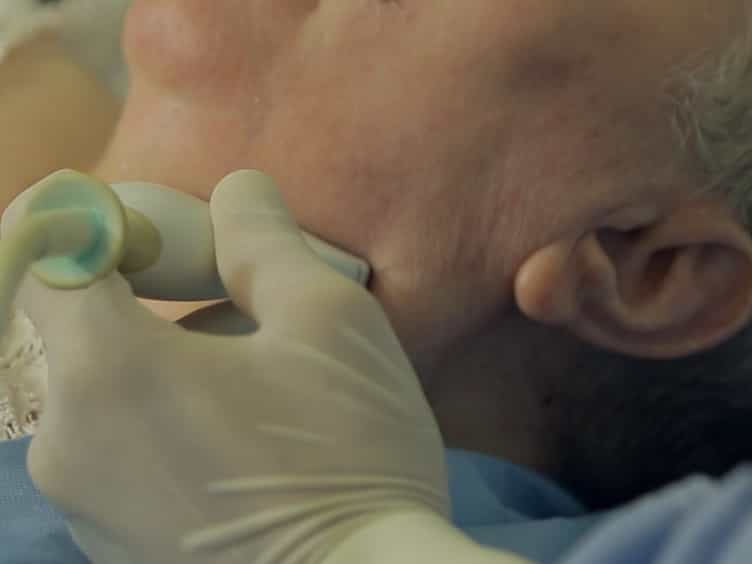
Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Employment of higher doses of botulinum toxin type A to reduce spasticity after stroke
Andrea Santamato1, Maria Francesca Micello1, Maurizio Ranieri1
1Physical Medicine and Rehabilitation Section-"OORR Hospital", University of Foggia, Foggia, Italy.

Abstract:
Spasticity is a common disabling symptom for several neurological conditions. Botulinum toxin type A injection represents the gold standard treatment for focal spasticity with efficacy, reversibility, and low prevalence of complications. Current guidelines suggest a dose up to 600 units (U) of onabotulinumtoxinA/incobotulinumtoxinA or up to 1,500 U of abobotulinumtoxinA to treat post-stroke spasticity to avoid important adverse effects. However, recently, higher doses of botulinum toxin type A were employed, especially in case of upper and lower limb severe spasticity. With searches of US National Library of Medicine databases, we identified all studies published from December 1989 to July 2014 concerning the use of higher doses of this neurotoxin for spasticity treatment with at least a dose of 600 U of onabotulinumtoxinA and incobotulinumtoxinA or 1,800 U of abobotulinumtoxinA. The cumulative body of evidence coming from the eight studies selected suggested that higher doses of botulinum toxin type A appeared to be efficacious in reducing spasticity of the upper and lower limbs after stroke, with adverse effects generally mild. However, further investigations are needed to determine the safety and reproducibility in larger case series or randomized clinical trials of higher doses of botulinum toxin type A also after repeated injections.
More Related Videos
 07:20
Author Spotlight: Repetitive Transcranial Magnetic Stimulation Combined with Movement Observation in Cerebral Palsy
Published on: August 9, 2024
 08:40
Isokinetic Robotic Device to Improve Test-Retest and Inter-Rater Reliability for Stretch Reflex Measurements in Stroke Patients with Spasticity
Published on: June 12, 2019
Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also...
 01:09
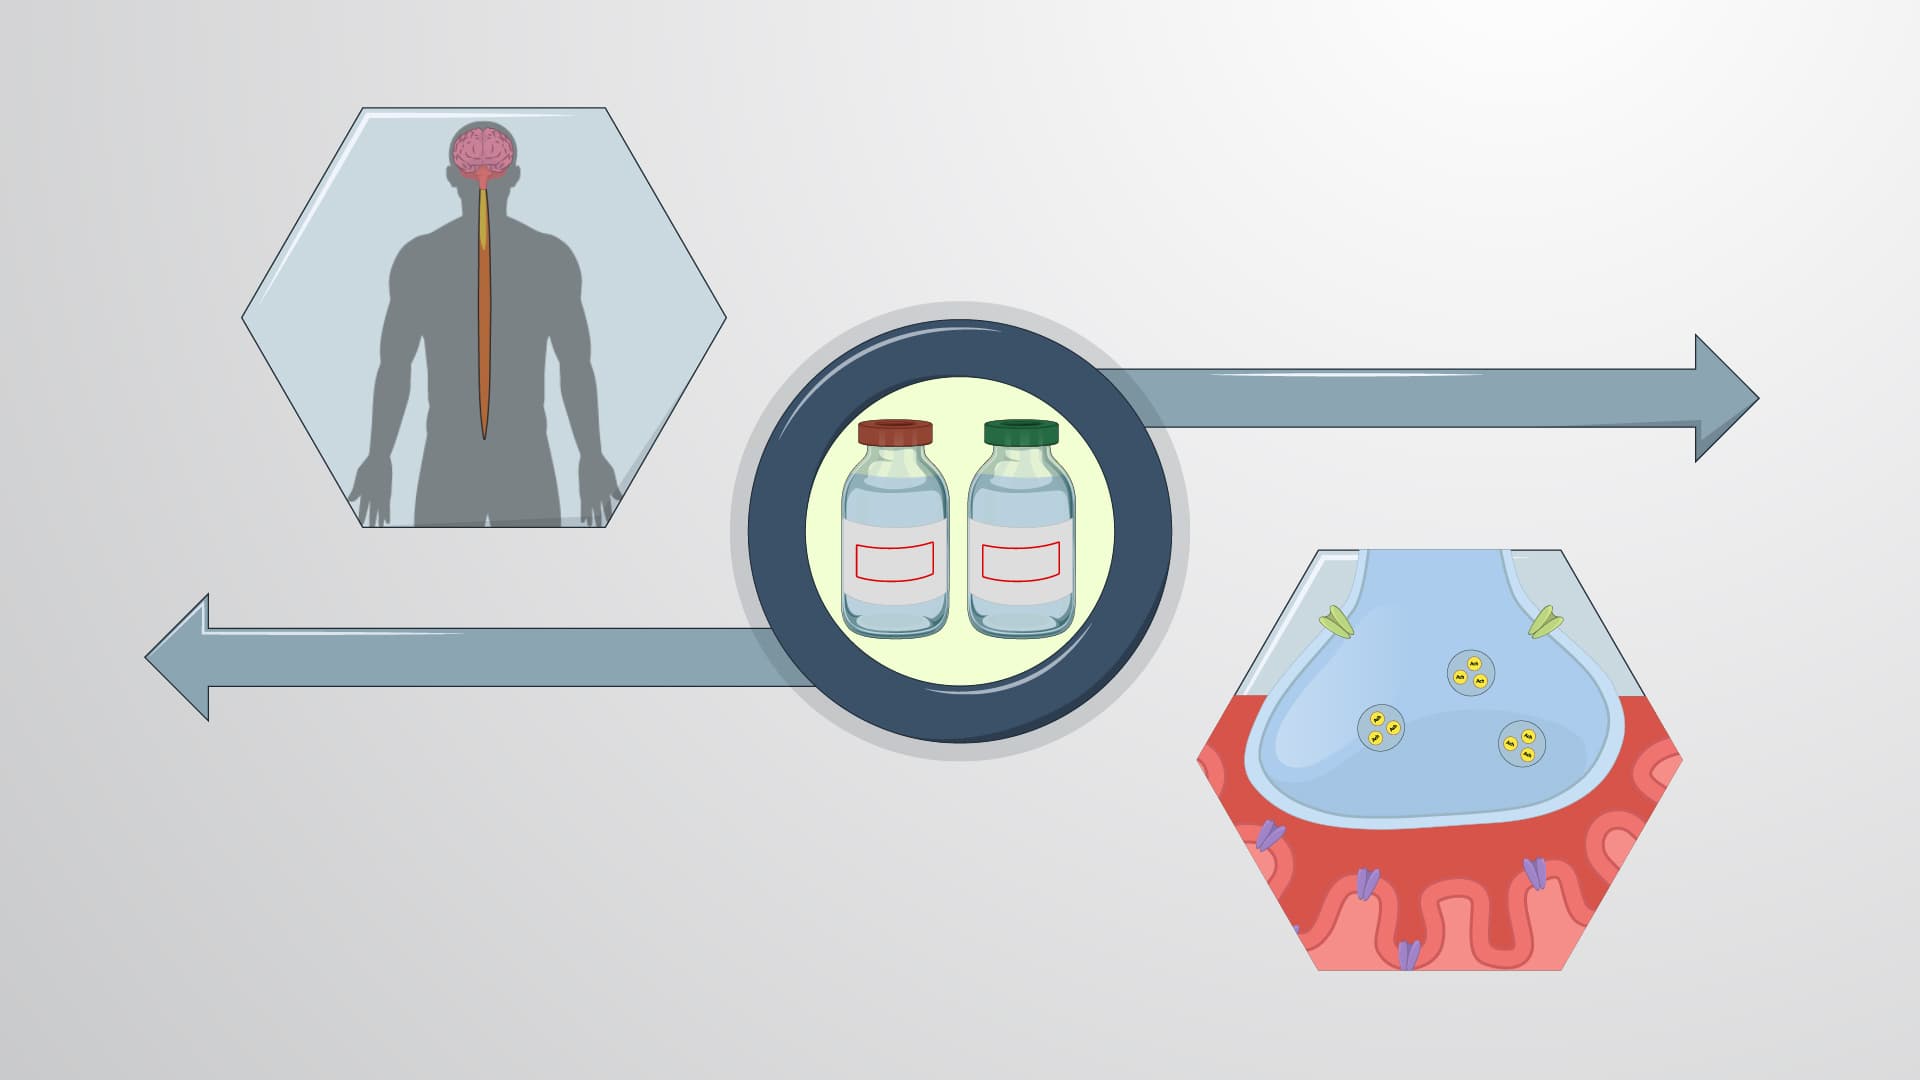
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...