Related Experiment Video
Updated: Apr 15, 2026


Interventional Diagnostic Procedure: A Practical Guide for the Assessment of Coronary Vascular Function
Published on: March 15, 2022
A prospective randomized evaluation of a pharmacogenomic approach to antiplatelet therapy among patients with
D Y F So1, G A Wells2, R McPherson3
1Division of Cardiology, University of Ottawa Heart Institute, Ottawa, Ontario, Canada.

Insights
Pharmacogenomic testing identifies patients at risk for clopidogrel complications after percutaneous coronary intervention (PCI). Prasugrel significantly reduced high on-treatment platelet reactivity compared to clopidogrel in these high-risk STEMI patients.
Area of Science:
- Cardiology
- Pharmacogenomics
- Genetics
Background:
- Clopidogrel treatment in carriers of CYP2C19*2 or ABCB1 TT genotypes increases ischemic complications post-PCI.
- ST-elevation myocardial infarction (STEMI) patients undergoing PCI require effective antiplatelet therapy.
Purpose of the Study:
- To evaluate a pharmacogenomic strategy using point-of-care genetic testing in STEMI patients undergoing PCI.
- To compare the efficacy of prasugrel versus an augmented clopidogrel dosing strategy in reducing high on-treatment platelet reactivity (HPR) in genetically at-risk patients.
Main Methods:
- A randomized trial of 102 STEMI patients undergoing PCI.
- Point-of-care genetic testing for CYP2C19*2, ABCB1 TT, and CYP2C19*17 alleles.
- Random assignment to prasugrel 10mg daily or augmented clopidogrel (150mg daily for 6 days, then 75mg daily).
- Primary endpoint: proportion of at-risk carriers with HPR (P2Y12 reaction units >234 or >208) after 1 month.
Main Results:
- 57.8% of patients were identified as carriers of at least one at-risk genetic variant.
- Prasugrel significantly reduced HPR compared to clopidogrel (0% vs 24.1% for PRU >234, P=0.0046; 3.3% vs 34.5% for PRU >208, P=0.0025).
- Point-of-care testing demonstrated high sensitivity and specificity for identifying genetic variants.
- Carriage of at-risk genotypes was a strong predictor of HPR (OR=6.58, P=0.03).
Conclusions:
- Concurrent, bedside identification of multiple genetic variants in STEMI patients undergoing PCI is feasible.
- In carriers of at-risk genotypes, prasugrel is superior to an augmented clopidogrel dosing strategy in reducing HPR.
- This pharmacogenomic approach can guide antiplatelet therapy selection to mitigate ischemic complications after PCI.
Abstract:
Treatment of carriers of the CYP2C19*2 allele and ABCB1 TT genotype with clopidogrel is associated with increased ischemic complications after percutaneous coronary intervention (PCI). We sought to evaluate a pharmacogenomic strategy among patients undergoing PCI for ST-elevation myocardial infarction (STEMI), by performing a randomized trial, enrolling 102 patients. Point-of-care genetic testing for CYP2C19*2, ABCB1 TT and CYP2C19*17 was performed with carriers of either the CYP2C19*2 allele or ABCB1 TT genotype randomly assigned to a strategy of prasugrel 10 mg daily or an augmented dosing strategy of clopidogrel (150 mg daily for 6 days then 75 mg daily). The primary end point was the proportion of at-risk carriers exhibiting high on-treatment platelet reactivity (HPR), a marker associated with increased adverse cardiovascular events, after 1 month. Fifty-nine subjects (57.8%) were identified as carriers of at least one at-risk variant. Treatment with prasugrel significantly reduced HPR compared with clopidogrel by P2Y12 reaction unit (PRU) thresholds of >234 (0 vs 24.1%, P=0.0046) and PRU>208 (3.3 vs 34.5%, P=0.0025). The sensitivity of point-of-care testing was 100% (95% CI 88.0-100), 100% (86.3-100) and 96.9% (82.0-99.8) and specificity was 97.0% (88.5-99.5), 97.1% (89.0-99.5) and 98.5% (90.9-99.9) for identifying CYP2C19*2, ABCB1 TT and CYP2C19*17, respectively. Logistic regression confirmed carriers as a strong predictor of HPR (OR=6.58, 95% CI 1.24-34.92; P=0.03). We confirmed that concurrent identification of three separate genetic variants in patients with STEMI receiving PCI is feasible at the bedside. Among carriers of at-risk genotypes, treatment with prasugrel was superior to an augmented dosing strategy of clopidogrel in reducing HPR.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 07:00
A Method to Study the C924T Polymorphism of the Thromboxane A2 Receptor Gene
Published on: April 1, 2019
Related Concept Videos
 01:29
Pharmacogenomics: Identification of New Drug Targets
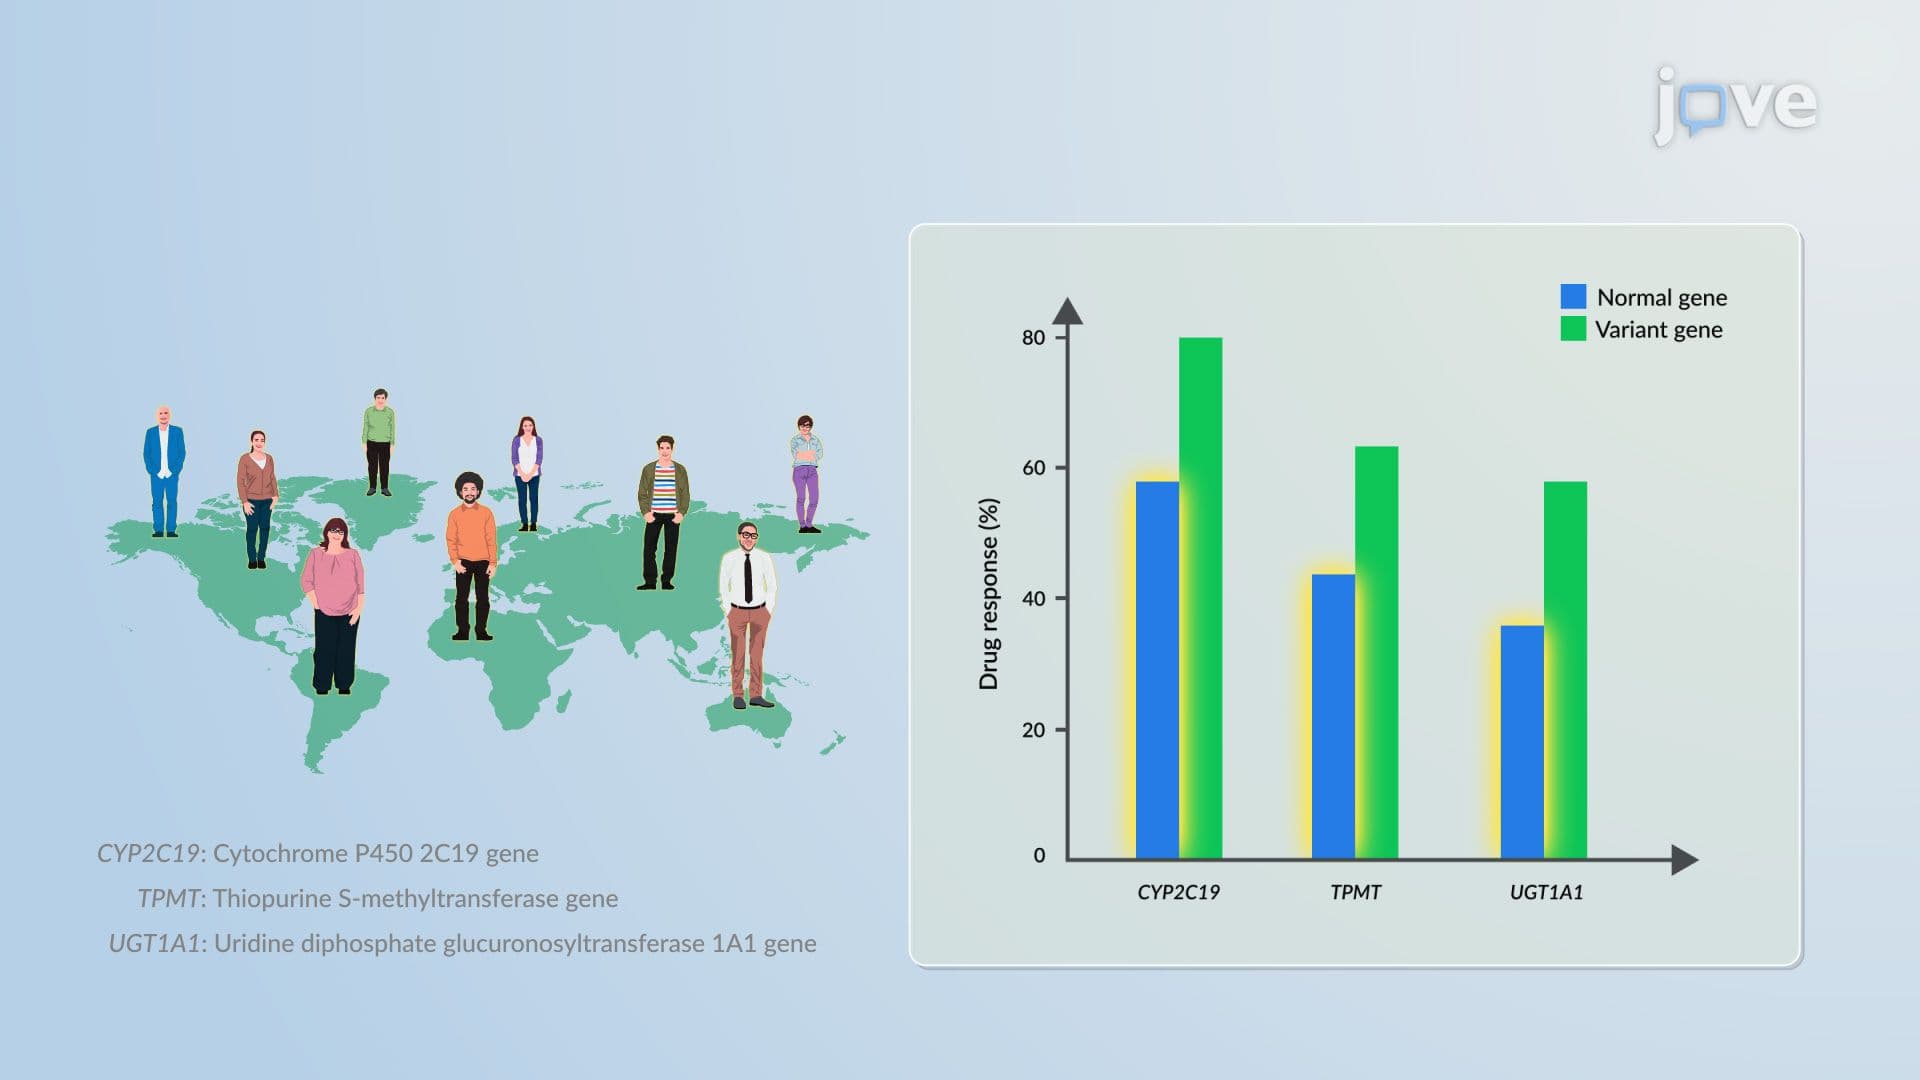 01:29
Pharmacogenetics and Pharmacogenomics: Overview
 01:29
Pharmacogenetic Phenotypes: Alterations in Pharmacokinetics, Drug Targets and Biologic Milieu
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:27
Pharmacogenetics of Drug Metabolism: Overview
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase