Related Experiment Video
Updated: Apr 7, 2026


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
Intrapleural tissue plasminogen activator and deoxyribonuclease therapy for pleural infection
Francesco Piccolo1, Natalia Popowicz1, Donny Wong1
11 Department of Medicine, Swan District Hospital, Perth, Australia ; 2 Respiratory Medicine, Sir Charles Gairdner Hospital, Perth, Australia ; 3 Respiratory Medicine, Auckland City Hospital, Auckland, New Zealand ; 4 Centre for Asthma, Allergy & Respiratory Research, School of Medicine & Pharmacology, University of Western Australia, Perth, Australia.

Abstract:
Pleural infection remains a global health burden associated with significant morbidity. Drainage of the infected pleural fluid is important but can often be hindered by septations and loculations. Intrapleural fibrinolytic therapy alone, to break pleural adhesions, has shown no convincing advantages over placebo in improving clinical outcome. Deoxyribonucleoprotein from degradation of leukocytes contributes significantly to high viscosity of infected pleural fluid. Recombinant deoxyribonuclease (DNase) is effective in reducing pleural fluid viscosity in pre-clinical studies. The combination of tissue plasminogen activator (tPA) and DNase was effective in animal model experiments of empyema. The benefits were established in a randomized clinical trial: those (n=48) treated with tPA/DNase had significantly improved radiological outcomes and reduced need of surgery and duration of hospital stay. A longitudinal observational series of 107 patients further confirmed the effectiveness and safety of tPA/DNase therapy, including its use as 'rescue therapy' when patients failed to respond to antibiotics and chest tube drainage. Overall, a short course of intrapleural tPA (10 mg) and DNase (5 mg) therapy provides a cure in over 90% of patients without requiring surgery. The treatment stimulates pleural fluid formation, enhances radiographic clearance and resolution of systemic inflammation. Serious complications are uncommon; pleural bleeding requiring transfusion occurred in ~2% of cases. Pain can occur, especially with the first dose. Treatment is contraindicated in those with significant bleeding diathesis or a bronchopleural fistula. Future research is required to optimize dosing regimens and in refining patient selection.


Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:28
Pleural Effusion II: Symptoms and Management
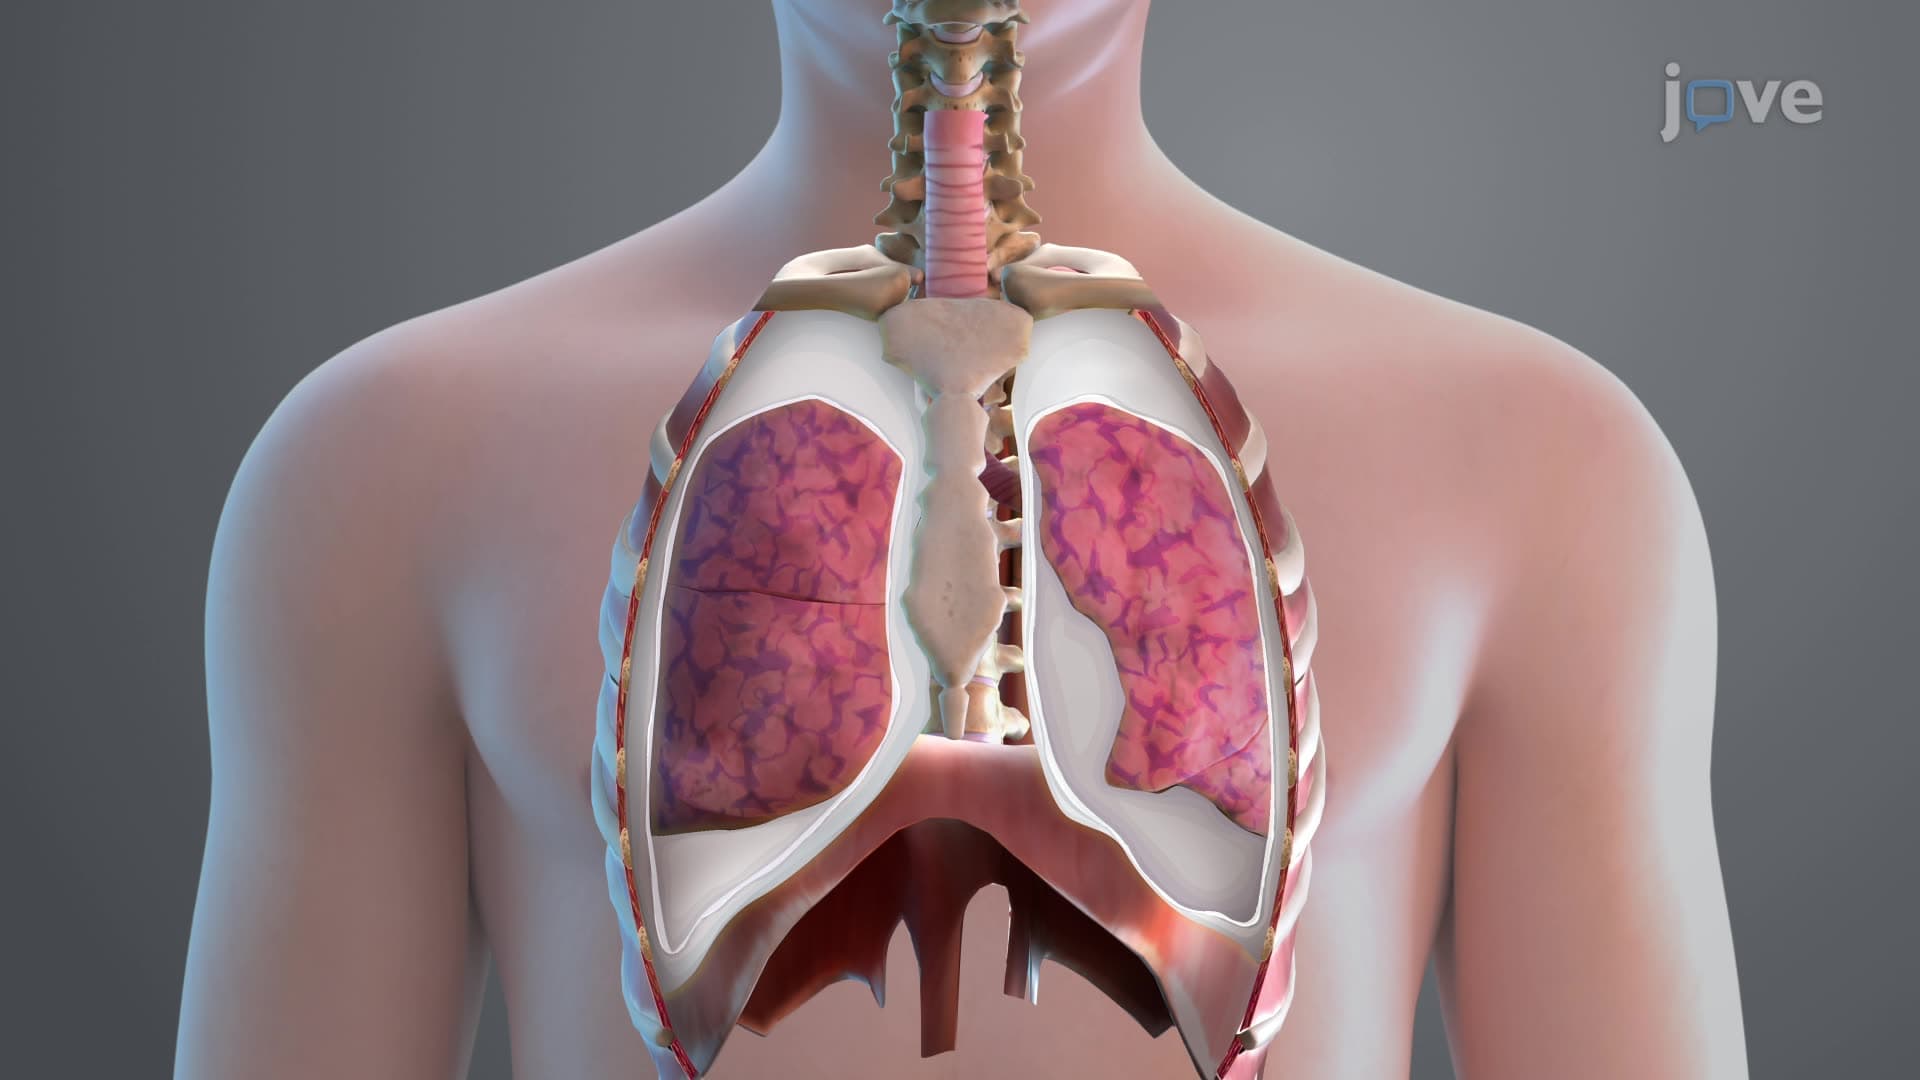
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:27
Pulmonary Embolism III: Nursing Management
 01:13
Pleura of the Lungs
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include: