Related Experiment Video
Updated: Aug 1, 2026


Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Electrocardiographic Left Atrial Abnormality and Risk of Stroke: Northern Manhattan Study
Hooman Kamel1, Madeleine Hunter2, Yeseon P Moon2
1From the Department of Neurology, Feil Family Brain and Mind Research Institute (H.K.) and Division of Cardiology (P.M.O.), Weill Cornell Medical College, New York; Department of Neurology (M.H., Y.P.M., S.Y., K.C., M.S.V.E.) and Division of Cardiology (M.R.D.T.), Columbia College of Physicians and Surgeons, New York; Department of Biostatistics, Columbia Mailman School of Public Health, New York (K.C.); Department of Neurology, Human Genetics, and Public Health Sciences, Miller School of Medicine, University of Miami, FL (R.L.S.); Departments of Epidemiology and Prevention (E.Z.S.) and Internal Medicine-Cardiology (E.Z.S.), Epidemiological Cardiology Research Center, Wake Forest School of Medicine, Winston-Salem, NC; and Department of Epidemiology, Mailman School of Public Health, Columbia University, New York (M.S.V.E.). hok9010@med.cornell.edu.

Background And Purpose:
Electrocardiographic left atrial abnormality has been associated with stroke independently of atrial fibrillation (AF), suggesting that atrial thromboembolism may occur in the absence of AF. If true, we would expect an association with cryptogenic or cardioembolic stroke rather than noncardioembolic stroke.
Methods:
We conducted a case-cohort analysis in the Northern Manhattan Study, a prospective cohort study of stroke risk factors. P-wave terminal force in lead V1 was manually measured from baseline ECGs of participants in sinus rhythm who subsequently had ischemic stroke (n=241) and a randomly selected subcohort without stroke (n=798). Weighted Cox proportional hazard models were used to examine the association between P-wave terminal force in lead V1 and stroke etiologic subtypes while adjusting for baseline demographic characteristics, history of AF, heart failure, diabetes mellitus, hypertension, tobacco use, and lipid levels.
Results:
Mean P-wave terminal force in lead V1 was 4452 (±3368) μV*ms among stroke cases and 3934 (±2541) μV*ms in the subcohort. P-wave terminal force in lead V1 was associated with ischemic stroke (adjusted hazard ratio per SD, 1.20; 95% confidence interval, 1.03-1.39) and the composite of cryptogenic or cardioembolic stroke (adjusted hazard ratio per SD, 1.31; 95% confidence interval, 1.08-1.58). There was no definite association with noncardioembolic stroke subtypes (adjusted hazard ratio per SD, 1.14; 95% confidence interval, 0.92-1.40). Results were similar after excluding participants with a history of AF at baseline or new AF during follow-up.
Conclusions:
ECG-defined left atrial abnormality was associated with incident cryptogenic or cardioembolic stroke independently of the presence of AF, suggesting atrial thromboembolism may occur without recognized AF.
More Related Videos


Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:28
Electrocardiogram Fundamentals
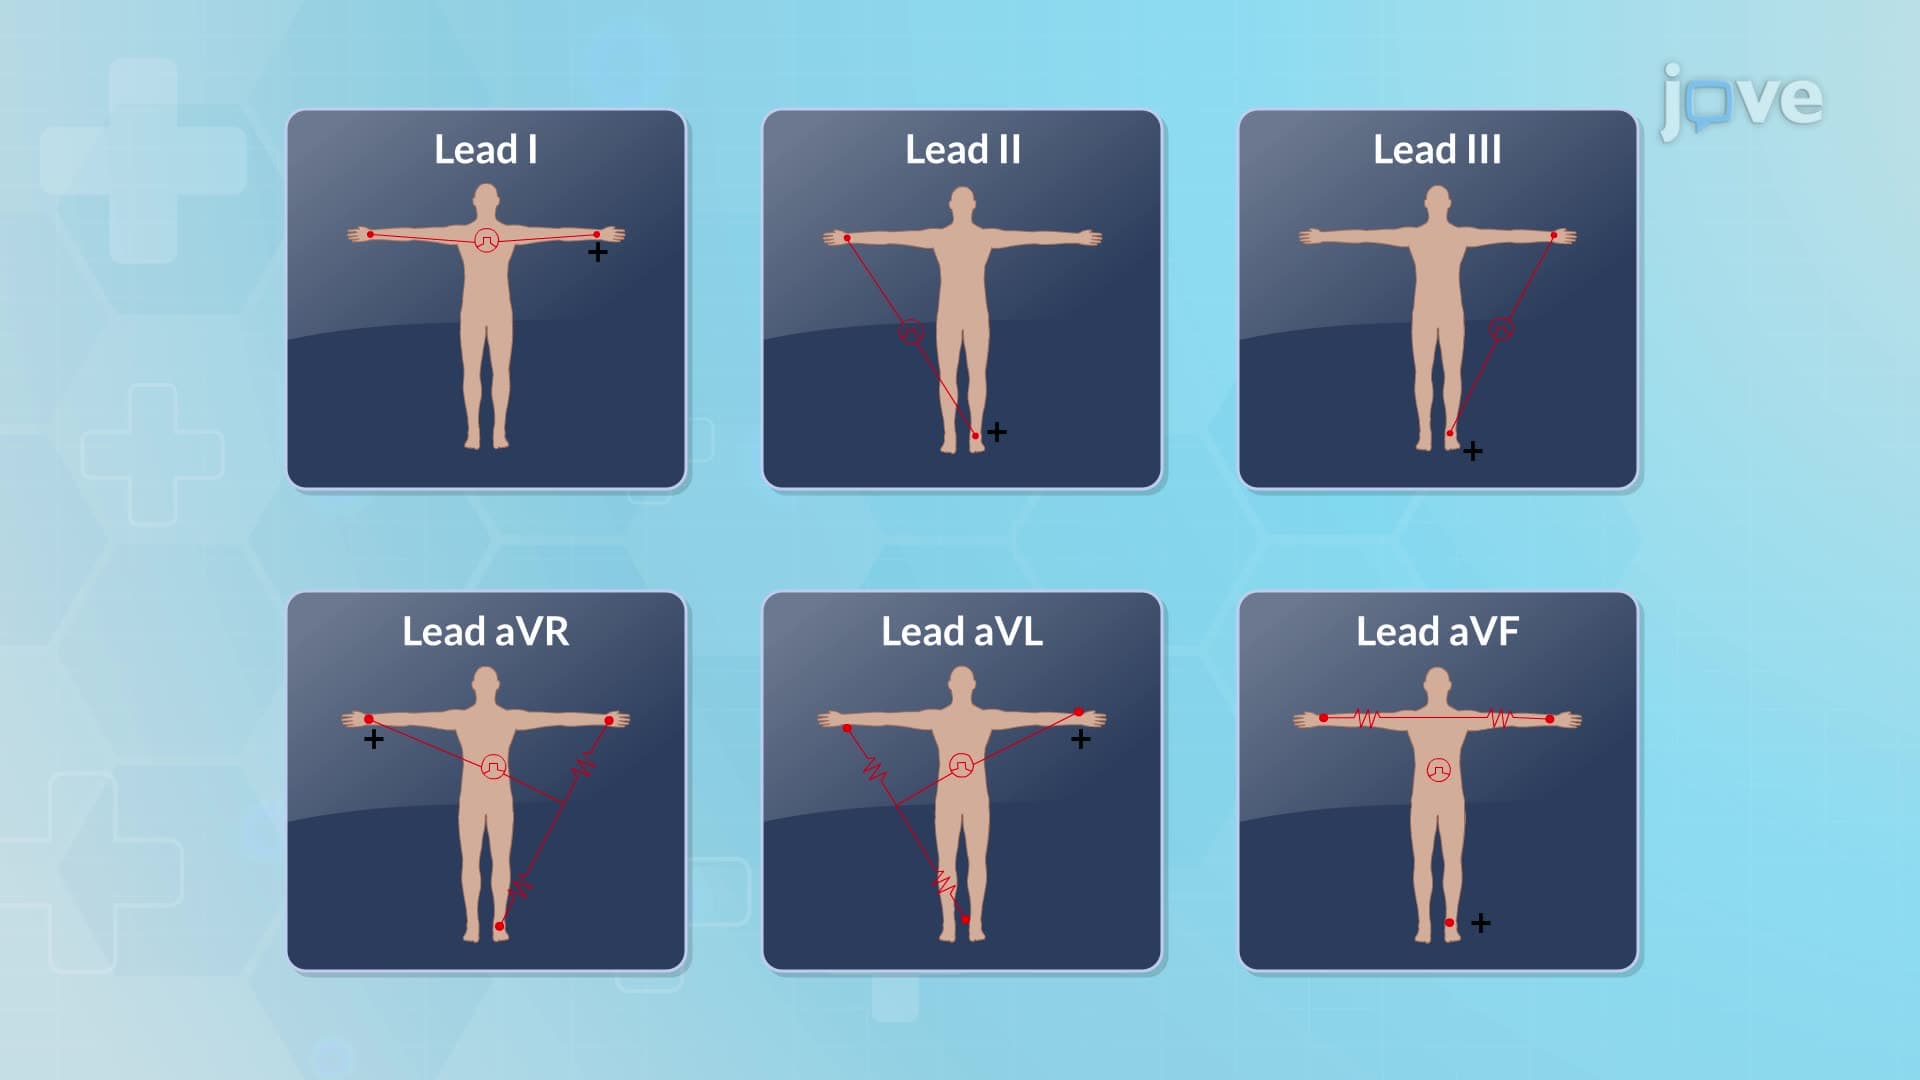
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias