Related Experiment Video
Updated: Mar 26, 2026
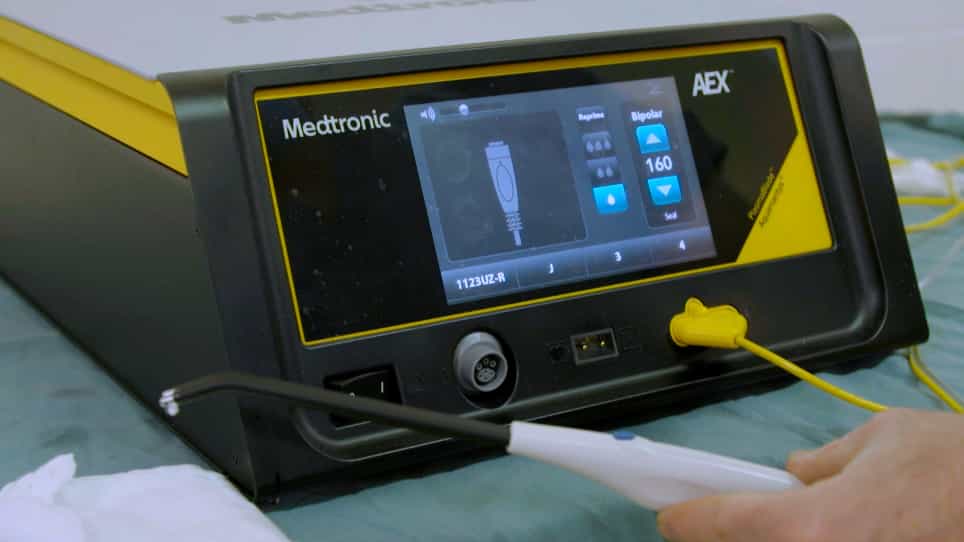

A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Survey of trauma surgeon practice of emergency department thoracotomy
Bradley M Dennis1, Andrew J Medvecz2, Oliver L Gunter1
1Division of Trauma and Acute Care Surgery, Vanderbilt University Medical Center, Vanderbilt University School of Medicine, 1211 21st Avenue S, 404 Medical Arts Building, Nashville, TN, 37212, USA.

Background:
There continues to be significant debate in the trauma community regarding the indications for emergency department thoracotomy (EDT). Numerous studies have focused on the duration of arrest in EDT, whereas few have examined other factors that influence surgeon decision-making. We hypothesize that there is continued variability among surgeons in the use of EDT.
Methods:
A 13-question web-based survey was distributed to the membership of a large, national trauma association, examining demographics, trauma fellowship completion, trauma center designation, professional organization membership, and annual EDTs performed. Consideration of patient's age, comorbidities, total injury burden, and the use of technological adjuncts-such as ultrasound-was assessed. Respondents were asked when they would perform the procedure after loss of vital signs for blunt and penetrating trauma. Logistic regression determined factors influencing consideration of EDT.
Results:
Overall 540 of 1,485 surveys were completed (36.4%). Patient age, total injury burden, and comorbidities are considered by 38.5%, 29.1%, and 55.7% of respondents, respectively. Technological adjuncts are used always or most of the time by 64% of respondents. A majority of respondents (51.9%) would perform an EDT for penetrating trauma with loss of vital signs 5 to 10 minutes before arrival. For blunt trauma, the largest group of respondents (47.0%) would perform an EDT only when loss of vital signs occurred in the ED. In addition, 20.6% would never perform EDT for blunt traumatic arrest.
Conclusions:
EDT decision-making is more nuanced than previously described. Variation continues in the use of thoracotomy after loss of vital signs, in both blunt and penetrating trauma. For both mechanisms, there remains little consensus on the appropriate duration of arrest before performing EDT after arrest despite published guidelines. A large proportion of surgeons consider other factors such as patient age, total injury burden, and comorbidities in addition to vital signs when deciding to perform an EDT. Technological adjuncts are frequently used by surgeons to determine the need for EDT.
More Related Videos
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...