Related Experiment Video
Updated: Mar 25, 2026


Generation, Amplification, and Titration of Recombinant Respiratory Syncytial Viruses
Published on: April 4, 2019
Bacteremia in Children Hospitalized with Respiratory Syncytial Virus Infection
Miriam Cebey-López1,2, Jacobo Pardo-Seco1,2,3, Alberto Gómez-Carballa1,2,3
1Grupo de Investigación en Genética, Vacunas, Infecciones y Pediatría (GENVIP - www.genvip.org), Hospital Clínico Universitario and Universidade de Santiago de Compostela (USC), Galicia, Spain.

Insights
Bacteremia is uncommon in infants hospitalized with RSV respiratory infections. However, it is more prevalent in severe cases requiring intensive care and respiratory support.
Area of Science:
- Pediatrics
- Infectious Diseases
- Microbiology
Background:
- The incidence of bacteremia in children with acute bronchiolitis is generally considered low.
- The precise rate of occult bacteremia in infants diagnosed with respiratory syncytial virus (RSV) infection remains unclear.
- This study aimed to establish the prevalence and identify predictive factors for bacteremia in hospitalized children with confirmed RSV acute respiratory illness (ARI).
Purpose of the Study:
- To determine the actual rate of bacteremia in infants hospitalized with RSV-associated acute respiratory illness (ARI).
- To identify potential predictive factors associated with bacteremia in this pediatric population.
- To compare the incidence of bacteremia using both conventional blood cultures and advanced molecular diagnostic techniques.
Main Methods:
- A prospective, multicenter study was conducted between 2011 and 2013, enrolling children under two years old admitted for ARI.
- Blood samples from RSV-positive patients were analyzed for bacterial presence using polymerase chain reaction (PCR) for common pathogens, alongside traditional culture methods.
- Specific bacteria targeted by PCR included: *Neisseria meningitidis*, *Streptococcus pneumoniae*, *Haemophilus influenzae*, *Streptococcus pyogenes*, *Klebsiella pneumoniae*, *Pseudomonas aeruginosa*, *Escherichia coli*, and *Staphylococcus aureus*.
Main Results:
- Out of 66 children with RSV-positive ARI, bacterial presence was detected in 10.6% (7 children).
- The identified bacteria were *Haemophilus influenzae* (n=4) and *Streptococcus pneumoniae* (n=2).
- Children with detected bacteremia showed significantly higher severity scores, including PICU admission (100% vs. 50%), need for respiratory support (100% vs. 18.6%), and longer hospitalization (12.1 vs. 7.5 days).
Conclusions:
- Bacteremia is infrequent in infants hospitalized for RSV respiratory infections.
- However, the possibility of bacteremia should be seriously considered in infants presenting with severe RSV illness.
- The findings highlight the importance of considering bacterial coinfection in severe pediatric respiratory infections.
Background:
The risk of bacteremia is considered low in children with acute bronchiolitis. However the rate of occult bacteremia in infants with RSV infection is not well established. The aim was to determine the actual rate and predictive factors of bacteremia in children admitted to hospital due to confirmed RSV acute respiratory illness (ARI), using both conventional culture and molecular techniques.
Methods:
A prospective multicenter study (GENDRES-network) was conducted between 2011-2013 in children under the age of two admitted to hospital because of an ARI. Among those RSV-positive, bacterial presence in blood was assessed using PCR for Meningococcus, Streptococcus pneumoniae, Haemophilus influenzae, Streptococcus pyogenes, Klebsiella pneumoniae, Pseudomonas aeruginosa, Escherichia coli, and Staphylococcus aureus, in addition to conventional cultures.
Results:
66 children with positive RSV respiratory illness were included. In 10.6% patients, bacterial presence was detected: H. influenzae (n = 4) and S. pneumoniae (n = 2). In those patients with bacteremia, there was a previous suspicion of bacterial superinfection and had received empirical antibiotic treatment 6 out of 7 (85.7%) patients. There were significant differences in terms of severity between children with positive bacterial PCR and those with negative results: PICU admission (100% vs. 50%, P-value = 0.015); respiratory support necessity (100% vs. 18.6%, P-value < 0.001); Wood-Downes score (mean = 8.7 vs. 4.8 points, P-value < 0.001); GENVIP scale (mean = 17 vs. 10.1, P-value < 0.001); and length of hospitalization (mean = 12.1 vs. 7.5 days, P-value = 0.007).
Conclusion:
Bacteremia is not frequent in infants hospitalized with RSV respiratory infection, however, it should be considered in the most severe cases.
More Related Videos
 09:14
An Improved and High Throughput Respiratory Syncytial Virus RSV Micro-neutralization Assay
Published on: January 26, 2019
 09:01
An In vitro Model to Study Immune Responses of Human Peripheral Blood Mononuclear Cells to Human Respiratory Syncytial Virus Infection
Published on: December 10, 2013
Related Concept Videos
 01:29
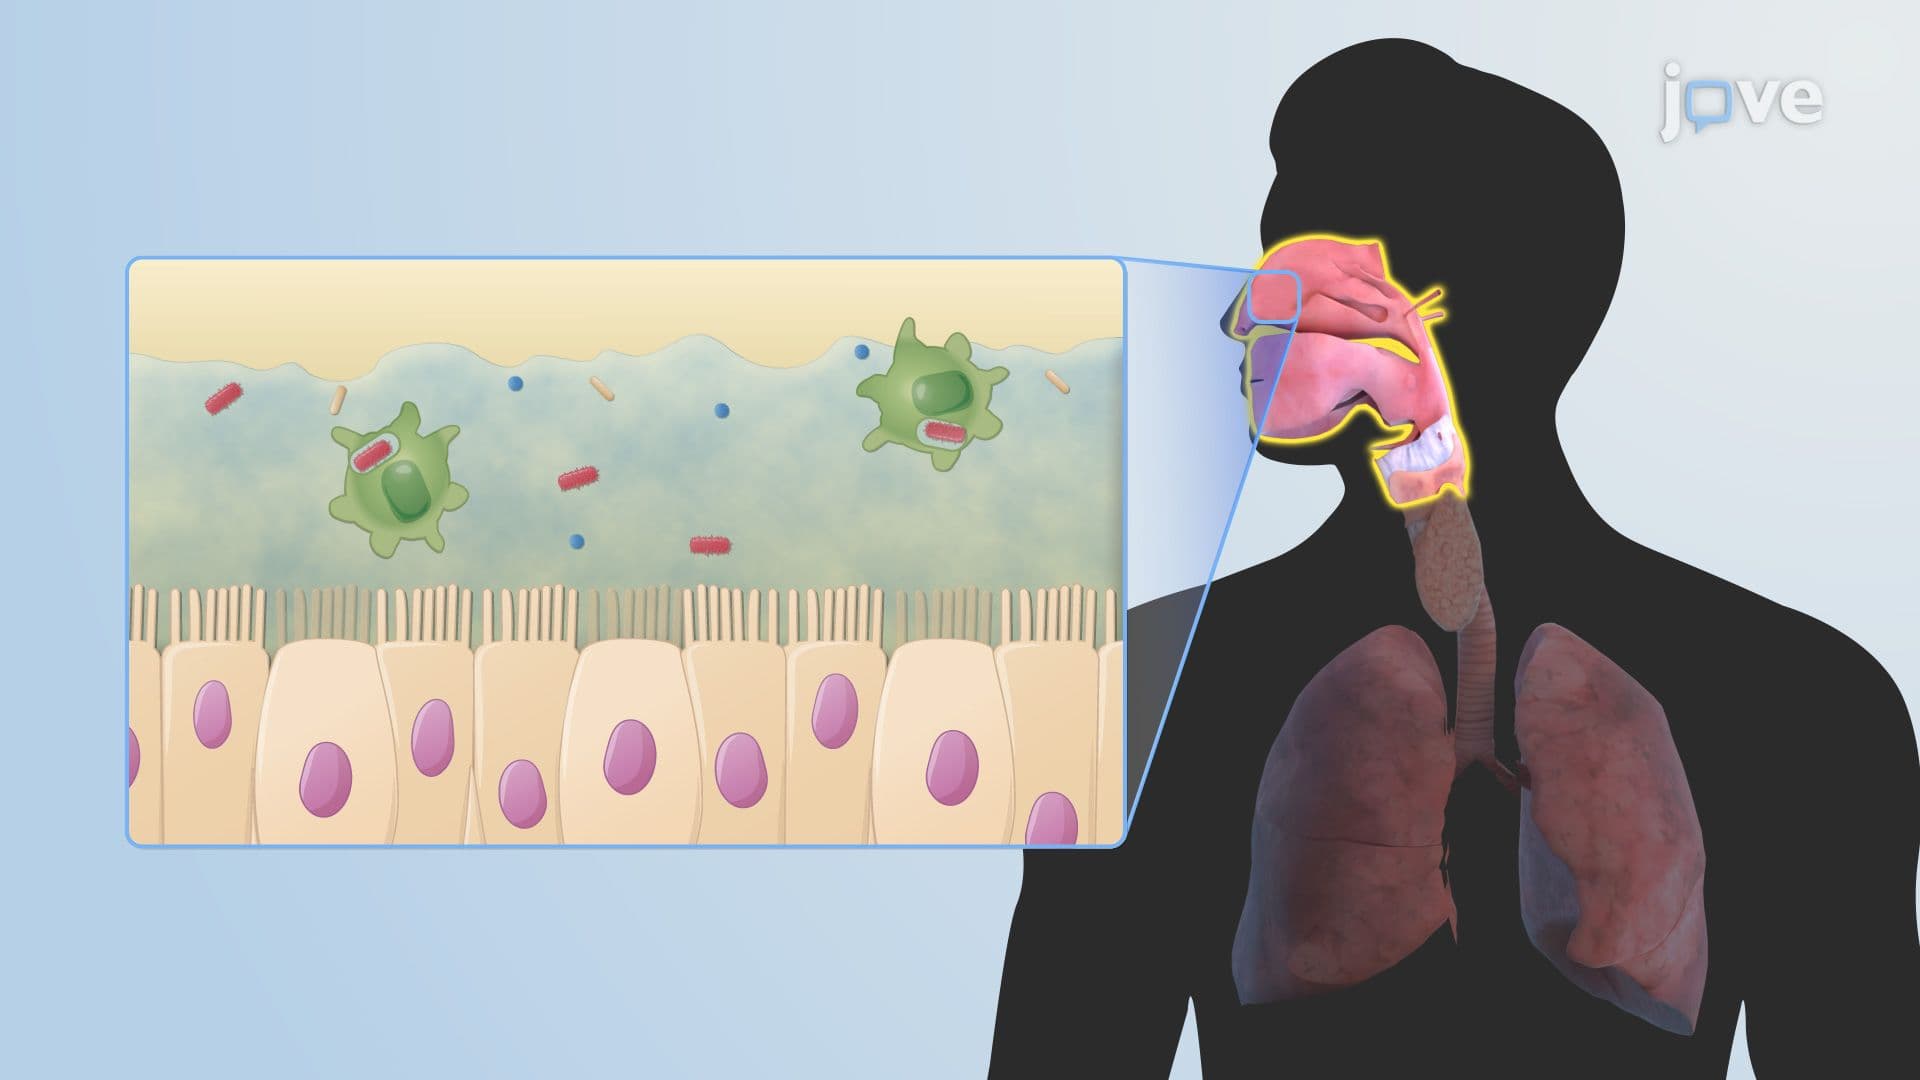
Microbiota of the Respiratory Tract
 01:18
Viral Meningitis
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:14
Atypical Pneumonia
 01:30
Pneumonia III: Complications and Assessment
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...