Related Experiment Video
Updated: Mar 23, 2026


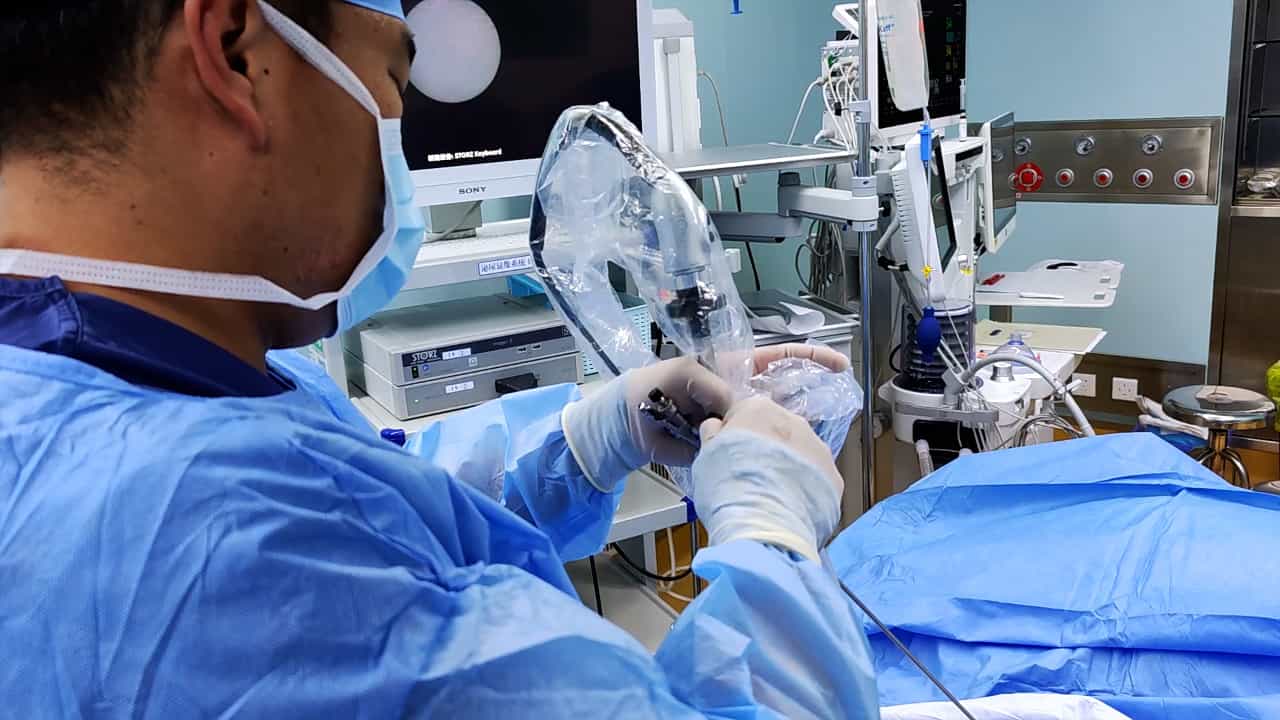
Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
EFFICACY OF ENDOSCOPIC TREATMENT FOR PRIMARY VESICOURETERIC REFLUX IN CHILDREN

Insights
Endoscopic treatment effectively resolves primary vesicoureteral reflux (VUR) in children. This minimally invasive approach offers a viable alternative to surgery for managing VUR, showing high success rates in clinical studies.
Area of Science:
- Pediatric Urology
- Minimally Invasive Surgery
- Urologic Imaging
Background:
- Vesicoureteral reflux (VUR) is a common childhood anomaly, affecting 1-3% of children and up to 50% of those with urinary tract infections (UTIs).
- Historically, febrile VUR and chronic antibiotic prophylaxis were managed with open surgery.
- Endoscopic injection of bulking agents has largely replaced open surgery for primary VUR.
Purpose of the Study:
- To evaluate the efficacy of endoscopic treatment for primary vesicoureteral reflux (VUR) in pediatric patients.
- To assess the success rate of minimally invasive VUR treatment.
Main Methods:
- A descriptive case series involving 105 children (1-12 years) with primary VUR (grades II-IV) treated endoscopically between 2011 and 2014.
- 181 ureters were treated with endoscopic injection.
- Treatment efficacy was assessed via voiding cystourethrogram (VCUG) at 3 months post-injection; success was defined as no or grade I reflux.
Main Results:
- Out of 105 patients, 76 had bilateral and 29 had unilateral VUR.
- Successful treatment (no or grade I reflux) was achieved in 116 out of 181 ureters (64%).
- 27% of ureters showed improved reflux (downgradation), and 8.8% showed no response.
Conclusions:
- Endoscopic treatment for VUR is a safe and effective option for children with primary VUR.
- This minimally invasive procedure can be considered a primary management strategy for pediatric VUR.
Background:
Vesicoureteral reflux (VUR) is a common anomaly affecting 1-3% of all children and 30-50% of those with urinary tract infection (UTI). In the past febrile vesicoureteric reflux on chronic antibiotic prophylaxis were treated by open surgery. Now a day's endoscopic injection of a bulking material has replaced open surgical procedure in cases of primary VUR. Our objective was to assess the efficacy of endoscopic treatment for primary vesico-ureteric reflux in children.
Methods:
This was a descriptive case series. One hundred and five patients with either unilateral or bilateral VUR (181 ureters) underwent endoscopic treatment for primary VUR between January 2011 and January 2014. Children from 1 to 12 years of age with grade-II to IV reflux on preoperative voiding cystourethrogram (VCUG) were enrolled through consecutive non-probability sampling. Efficacy of treatment was evaluated at three months post injection by a standard VCUG. Ureters with no or grade-I reflux were considered successful treatment.
Results:
Out of 105 patients 76 had bilateral while 29 had unilateral reflux. Mean age was 5.7 years (SD ± .7). Among 181 refluxing ureters, 116 (64%) were free of reflux, while 49 (27%) showed down gradation and 16 (8.8%) showed no response to treatment on postoperative VCUG.
Conclusion:
Endoscopic treatment for VUR is a viable option for patients with primary VUR and may be considered in management of such cases.

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:28
Urologic Endoscopic Procedure: Cystoscopic Examination
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:25
Urinary Tract Calculi VI: Surgical Management