

Total internal biliary diversion during liver transplantation for type 1 progressive familial intrahepatic
V P Mali1, A Fukuda2, T Shigeta2
1Organ Transplantation Center, National Center for Child Health and Development, Tokyo, Japan. survpm@nus.edu.sg.

Insights
This study shows that transintestinal biliary diversion (TIBD) during liver transplantation (LT) effectively manages PFIC type 1 by resolving jaundice and preventing graft steatosis. TIBD offers a stoma-free solution for biliary diversion in these patients.
Area of Science:
- Hepatology
- Pediatric Gastroenterology
- Surgical Innovation
Background:
- Progressive familial intrahepatic cholestasis type 1 (PFIC type 1) often presents with severe cholestatic jaundice, pruritus, and growth retardation.
- Liver transplantation (LT) is a potential treatment for PFIC type 1, but complications like postoperative diarrhea and recurrent graft steatosis can occur.
- Current management strategies for PFIC type 1 require effective methods to mitigate post-LT complications.
Observation:
- A 26-month-old female with PFIC type 1, confirmed ATP8B1 defects, and elevated bilirubin underwent LT with a segment 2, 3 graft from her father.
- A transintestinal biliary diversion (TIBD) using a 35-cm jejunum conduit was performed, connecting the graft hepatic duct to the mid-transverse colon.
- Post-diversion, stools immediately became pigmented, and follow-up demonstrated resolution of jaundice and pruritus with improved stool consistency.
Findings:
- Radioisotope hepato-biliary scintigraphy confirmed unobstructed bile drainage into the colon with decreasing transit times (t½: 34, 27, and 19 minutes).
- Contrast studies at 62 and 140 days post-LT showed no colo-jejuno-hepatic reflux and a patent jejuno-colonic anastomosis.
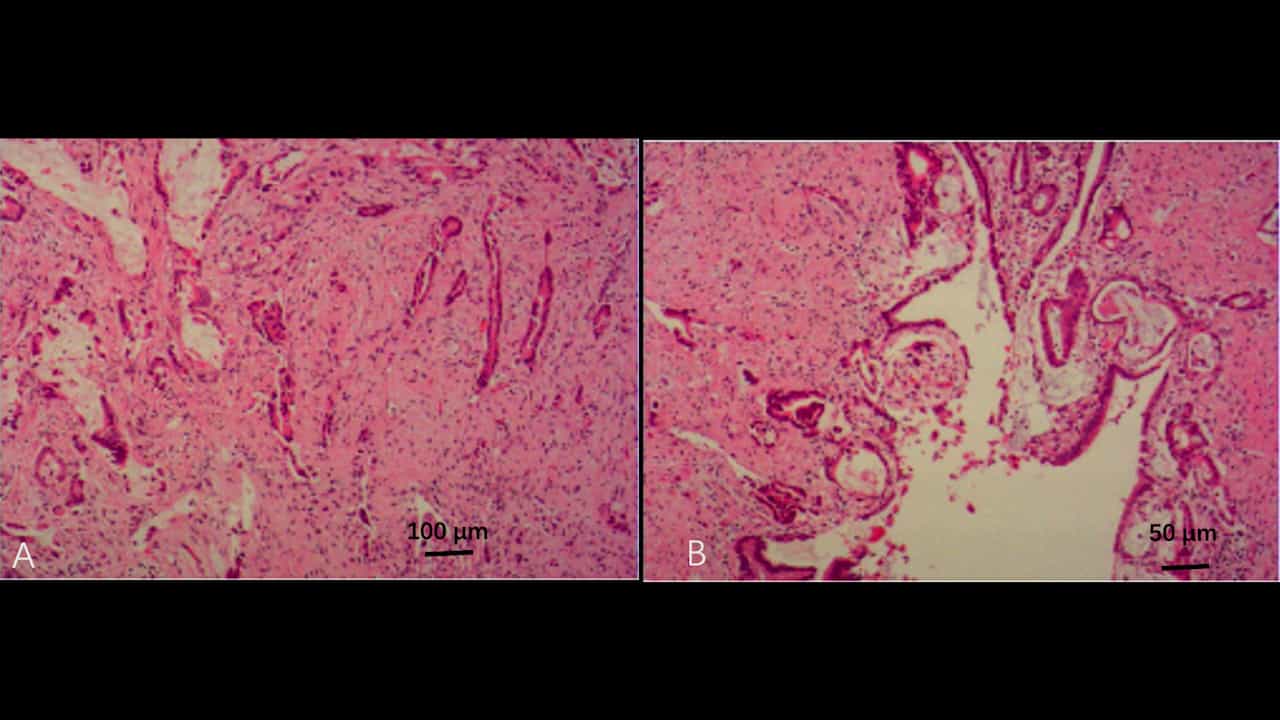
- Graft biopsies revealed stable, low-grade macrovesicular steatosis (<20%) at multiple follow-up points (138 days and 9 months).
Implications:
- Transintestinal biliary diversion (TIBD) during LT appears to be a clinically effective, stoma-free approach for biliary diversion in PFIC type 1.
- This technique may prevent recurrent graft steatosis, a significant complication following LT for PFIC type 1.
- TIBD represents a promising surgical innovation for improving outcomes in pediatric liver transplantation for cholestatic liver diseases.
Abstract:
LT for PFIC type 1 is often complicated by postoperative diarrhea and recurrent graft steatosis. A 26-month-old female child with cholestatic jaundice, pruritus, diarrhea, and growth retardation revealed total bilirubin 9.1 mg/dL, gamma-glutamyl transpeptidase 64 IU/L, and TBA 295.8 μmol/L. Genetic analysis confirmed ATP8B1 defects. A LT (segment 2, 3 graft) from the heterozygous father was performed. Biliary diversion was performed by a 35-cm jejunum conduit between the graft hepatic duct and the mid-transverse colon. Stools became pigmented immediately. Follow-up at 138 days revealed resolution of jaundice and pruritus and soft-to-hard stools (6-8 daily). Radioisotope hepato-biliary scintigraphy (days 26, 68, and 139) confirmed unobstructed bile drainage into the colon (t1/2 34, 27, and 19 minutes, respectively). Contrast meal follow-through at day 62 confirmed the absence of any colo-jejuno-hepatic reflux. At 140 days, contrast follow-through via the biliary stent revealed patent jejuno-colonic anastomosis and satisfactory transit. Graft biopsy at LT, 138 days, and 9 months follow-up revealed comparable grades of macrovesicular steatosis (<20%). TIBD during LT may be a clinically effective stoma-free biliary diversion and may prevent recurrent graft steatosis following LT for PFIC type 1.
More Related Videos
 07:44
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
 05:22
Intraoperative Strategy under Complex Vascular Adhesion for Laparoscopic Radical Resection of Bismuth-Corlette Type IIIb Perihilar Cholangiocarcinoma
Published on: February 13, 2026