Recurrent Acute Myocardial Infarction in a Patient with Severe Coronary Artery Ectasia: Implication of Antithrombotic Therapy

Tomoko Tomioka1, Satoshi Takeuchi1, Yoshitaka Ito1
1Department of Cardiology, South-Miyagi Medical Center, Shibata, Miyagi, Japan.

Insights
Recurrent acute myocardial infarction (AMI) in a patient with coronary artery ectasia was linked to local thrombus formation. Anticoagulation therapy showed effectiveness in preventing further events.
Area of Science:
- Cardiology
- Vascular Medicine
Background:
- Acute myocardial infarction (AMI) has diverse causes beyond plaque rupture, including thromboembolism and coronary thrombosis.
- Coronary artery ectasia is an underrecognized cause of myocardial infarction.
Observation:
- A 78-year-old woman experienced two episodes of AMI within one month in the distal right coronary artery.
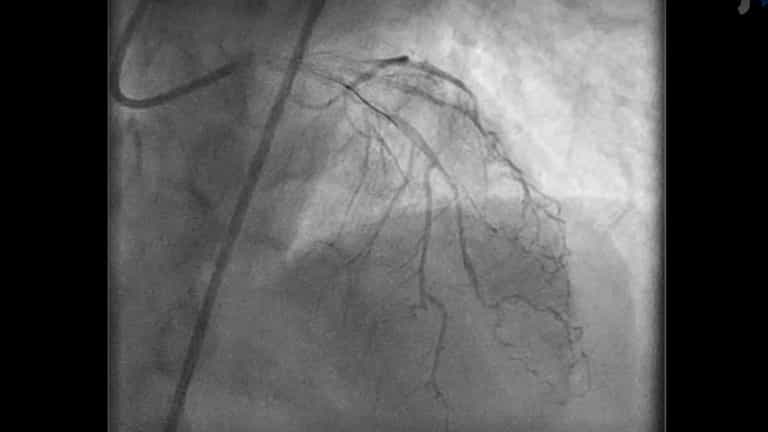
- Coronary angiography revealed no plaque rupture or stenosis, but identified coronary artery ectasia.
- Doppler velocimetry showed sluggish blood flow in the ectatic segment, suggesting local thrombus formation.
Findings:
- The recurrent AMI events were attributed to local thrombus formation within the coronary artery ectasia segment.
- Anticoagulation therapy with warfarin was initiated after the second event.
- Post-treatment evaluation confirmed the absence of plaque rupture and thrombus, indicating therapeutic effectiveness.
Implications:
- Local thrombus formation due to stagnant blood flow in coronary artery ectasia can cause AMI.
- Anticoagulation therapy may be a viable strategy for managing patients with coronary artery ectasia and recurrent AMI, irrespective of atrial fibrillation.
- This case highlights the importance of considering non-atherosclerotic causes of AMI.
Abstract:
BACKGROUND Acute myocardial infarction (AMI) can be caused not only by plaque rupture/erosion, but also by many other mechanisms. Thromboembolism due to atrial fibrillation and coronary thrombosis due to coronary artery ectasia are among the causes. Here we report on a case of recurrent myocardial infarction with coronary artery ectasia. CASE REPORT Our case was a 78-year-old woman with hypertension. Within a one-month interval, she developed AMI twice at the distal portion of her right coronary artery along with coronary artery ectasia. On both events, emergent coronary angiography showed no obvious organic stenosis or trace of plaque rupture at the culprit segment after thrombus aspiration. After the second acute event, we started anticoagulation therapy with warfarin to prevent thrombus formation. In the chronic phase, we confirmed, by using coronary angiography, optimal coherence tomography and intravascular ultrasound, that there was no plaque rupture and no obvious thrombus formation along the coronary artery ectasia segment of the distal right coronary artery, which suggested effectiveness of anticoagulant. Furthermore, by Doppler velocimetry we found sluggish blood flow only in the coronary artery ectasia lesion but not in the left atrium which is generally the main site of systemic thromboembolism revealed by transesophageal echocardiography. CONCLUSIONS These results suggest that the two AMI events at the same coronary artery ectasia segment were caused by local thrombus formation due to local stagnant blood flow. Although it has not yet been generally established, anticoagulation therapy may be effective to prevent thrombus formation in patients with coronary artery ectasia regardless of the prevalence of atrial fibrillation.

Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:14
Myocarditis III: Medical Management
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:26
Angina IV: Management