Related Experiment Video
Updated: Feb 27, 2026


Myocardial Infarction and Functional Outcome Assessment in Pigs
Published on: April 25, 2014
Comparison of Left Ventricular Function and Myocardial Infarct Size Determined by 2-Dimensional Speckle Tracking
Laurien Goedemans1, Rachid Abou1, Georgette E Hoogslag1
1Department of Cardiology, Leiden University Medical Centre, Leiden, The Netherlands.

Insights
Patients with chronic obstructive pulmonary disease (COPD) experience greater left ventricular global longitudinal strain impairment after ST-segment elevation myocardial infarction (STEMI), despite similar infarct sizes. This suggests a more significant functional deficit in these high-risk cardiac patients.
Area of Science:
- Cardiology
- Pulmonology
- Medical Imaging
Background:
- Patients with chronic obstructive pulmonary disease (COPD) face elevated mortality risks following acute ST-segment elevation myocardial infarction (STEMI).
- Assessing left ventricular (LV) systolic function is crucial for understanding outcomes in STEMI patients, particularly those with comorbidities like COPD.
Purpose of the Study:
- To compare infarct size and LV systolic function between STEMI patients with and without COPD.
- To investigate the utility of advanced 2-dimensional speckle tracking echocardiography in evaluating subtle functional impairments.
Main Methods:
- Utilized transthoracic echocardiography to measure left ventricular ejection fraction (LVEF) and wall motion score index.
- Assessed infarct size via creatine kinase and troponin T biomarkers.
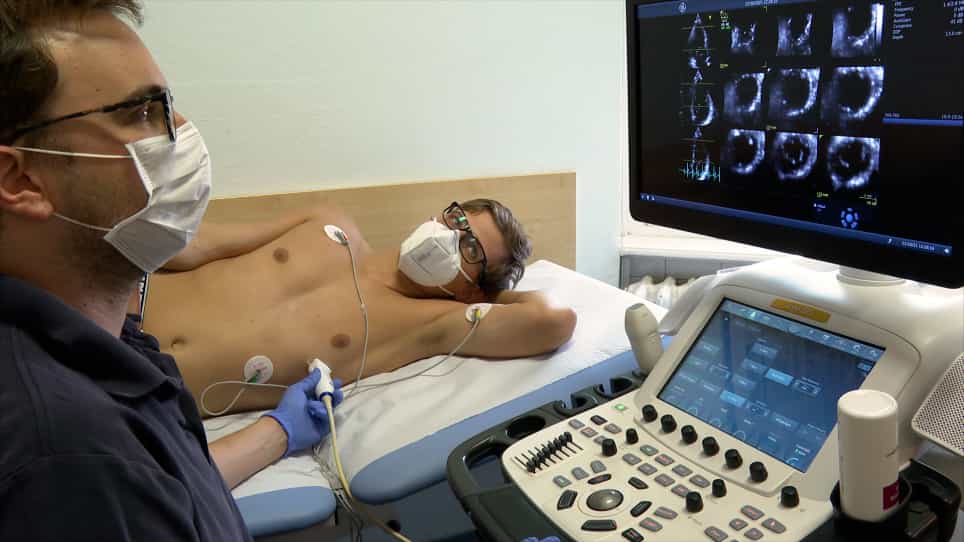
- Employed 2-dimensional speckle tracking echocardiography to measure LV global longitudinal strain (GLS) as a marker of myocardial deformation and systolic function.
Main Results:
- No significant differences were observed in infarct size (creatine kinase, troponin T) or conventional LV systolic function (LVEF, wall motion score index) between STEMI patients with and without COPD.
- LV global longitudinal strain (GLS) was significantly more impaired in STEMI patients with COPD (-13.9 ± 3.0%) compared to those without COPD (-14.7 ± 3.9%).
- STEMI patients with COPD were older, more likely former smokers, and had poorer renal function.
Conclusions:
- Despite comparable infarct size and conventional systolic function, STEMI patients with COPD demonstrate significantly impaired LV GLS.
- Advanced echocardiography, specifically GLS, reveals a greater underlying functional impairment in STEMI patients with COPD early post-infarction.
- These findings highlight the importance of advanced echocardiographic assessment in identifying at-risk cardiac populations with COPD.
Abstract:
Patients with chronic obstructive pulmonary disease (COPD) have a high risk of mortality after acute ST-segment elevation myocardial infarction (STEMI). We compared STEMI patients with versus without COPD in terms of infarct size and left ventricular (LV) systolic function using advanced 2-dimensional speckle tracking echocardiography. Of 1,750 patients with STEMI (mean age 61 ± 12 years, 76% male), 133 (7.6%) had COPD. With transthoracic echocardiography, left ventricular ejection fraction (LVEF) and wall motion score index were measured. Infarct size was assessed using biomarkers (creatine kinase and troponin T). LV global longitudinal strain (GLS), reflecting active LV myocardial deformation, was measured with 2-dimensional speckle tracking echocardiography to estimate LV systolic function and infarct size. STEMI patients with COPD were significantly older, more likely to be former smokers, and had worse renal function compared with patients without COPD. There were no differences in infarct size based on peak levels of creatine kinase (1315 [613 to 2181] vs 1477 [682 to 3047] U/l, p = 0.106) and troponin T (3.3 [1.4 to 7.3] vs 3.9 [1.5 to 7.8] µg/l, p = 0.489). Left ventricular ejection fraction (46% vs 47%, p = 0.591) and wall motion score index (1.38 [1.25 to 1.66] vs 1.38 [1.19 to 1.69], p = 0.690) were comparable. In contrast, LV GLS was significantly more impaired in patients with COPD compared with patients without COPD (-13.9 ± 3.0% vs -14.7 ± 3.9%, p = 0.034). In conclusion, despite comparable myocardial infarct size and LV systolic function as assessed with biomarkers and conventional echocardiography, patients with COPD exhibit more impaired LV GLS on advanced echocardiography than patients without COPD, suggesting a greater functional impairment at an early stage after STEMI.