Early versus late tracheostomy after decompressive craniectomy for stroke
Related Experiment Video
Updated: Feb 16, 2026
Microvascular Decompression: Salient Surgical Principles and Technical Nuances
Published on: July 5, 2011
Michael P Catalino1, Feng-Chang Lin2, Nathan Davis1
1Department of Neurosurgery, University of North Carolina School of Medicine, 170 Manning Drive, Campus Box 7025, Chapel Hill, NC 27599-7025 USA.

Background:
Stroke patients requiring decompressive craniectomy are at high risk of prolonged mechanical ventilation and ventilator-associated pneumonia (VAP). Tracheostomy placement may reduce the duration of mechanical ventilation. Predicting which patients will require tracheostomy and the optimal timing of tracheostomy remains a clinical challenge. In this study, the authors compare key outcomes after early versus late tracheostomy and develop a useful pre-operative decision-making tool to predict post-operative tracheostomy dependence.
Methods:
We performed a retrospective analysis of prospectively collected registry data. We developed a propensity-weighted decision tree analysis to predict tracheostomy requirement using factors present prior to surgical decompression. In addition, outcomes include probability functions for intensive care unit length of stay, hospital length of stay, and mortality, based on data for early (≤ 10 days) versus late (> 10 days) tracheostomy.
Results:
There were 168 surgical decompressions performed on patients with acute ischemic or spontaneous hemorrhagic stroke between 2010 and 2015. Forty-eight patients (28.5%) required a tracheostomy, 35 (20.8%) developed VAP, and 126 (75%) survived hospitalization. Mean ICU and hospital length of stay were 15.1 and 25.8 days, respectively. Using GCS, SOFA score, and presence of hydrocephalus, our decision tree analysis had 63% sensitivity and 84% specificity for predicting tracheostomy requirement. The early group had fewer ventilator days (7.3 versus 15.2, p < 0.001) and shorter hospital length of stay (28.5 versus 44.4 days, p = 0.014). VAP rates and mortality were similar between the two groups. Withdrawal of treatment interventions shortly post-operatively confounded mortality outcomes.
Conclusion:
Early tracheostomy shortens duration of mechanical ventilation and length of stay after surgical decompression for stroke, but it did not impact mortality or VAP rates. A decision tree is a practical tool that may be helpful in guiding pre-operative decision-making with patients' families.
Related Concept Videos
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:23
Tracheostomy Suctioning II: Procedure
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
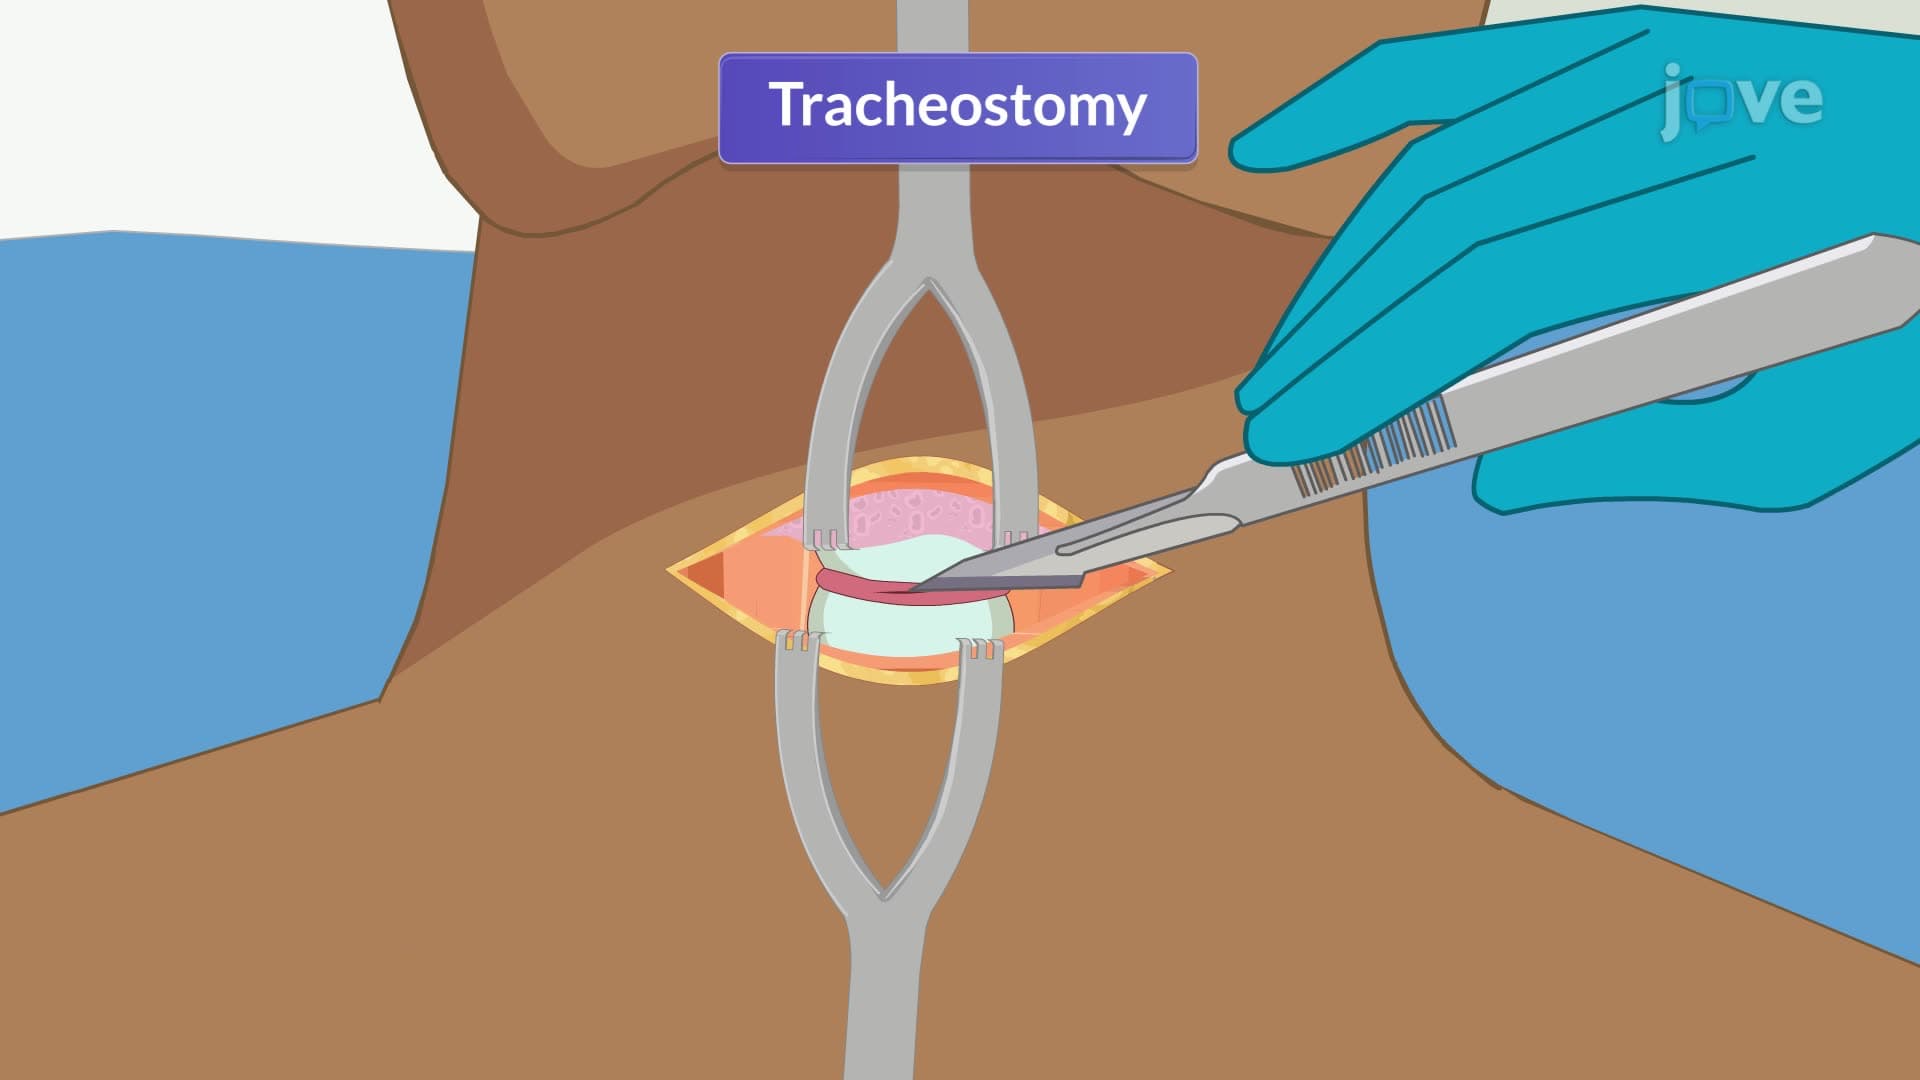
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...