Related Experiment Video
Updated: Feb 15, 2026


Decellularization and Recellularization Methodology for Human Saphenous Veins
Published on: July 27, 2018
Investigation of non-saphenous veins in C0S patients
Marzia Lugli1, Oscar Maleti2, M Letizia Iabichella2
1Department of Cardiovascular Surgery, Hesperia Hospital, Modena, Italy - lugli@chirurgiavascolaremodena.it.

Background:
C0S patients have symptoms of chronic venous disorders (CVDs), though an anatomical or pathophysiological explanation is lacking. C0 and C1 classified lower limbs can present with valve incompetence from the second to sixth generation of tributaries of saphenous veins despite the absence of a detectable saphenous truncal reflux. We hypothesized that C0S venous symptoms could stem from the second to sixth generation of saphenous tributaries and small veins that are not connected to the saphenous system. The aim was to explore these veins in C0S subjects and compare them with asymptomatic C0A subjects.
Methods:
This was an open, controlled study enrolling 36 subjects, where C0S patients (N.=18) were compared with asymptomatic C0A subjects (N.=18). The VAS (visual analog scale) was used to assess leg pain. Veins were assessed using B-flow ultrasound (valve anatomy), continuous-wave (CW) Doppler (flow patterns), biomicroscopy (visualization of nutritional vessels), laser Doppler flowmetry (quantify supine microvascular perfusion) and quantitative digital photo-plethysmography (PPG) (measuring post-exercise venous refilling time [VRT]).
Results:
There were no significant differences between C0S and C0A subjects in terms of microvascular perfusion (laser-Doppler), nutritional vessels (biomicroscopy) and VRT (PPG). B-flow ultrasound was unable to acquire sufficient data in second generation saphenous tributaries. However, the CW Doppler identified two different flow patterns: uni- and bidirectional. Bidirectional flow was significantly (P=0.05) higher in C0S versus C0A patients.
Conclusions:
CW Doppler, using a flat high-sensitivity probe, revealed the presence of a bidirectional flow that was significantly (P=0.05) higher in C0S than in control patients, suggesting the presence of reflux in non axial veins. These data give a new perspective on the management of C0S patients.
More Related Videos
 09:04
Synergizing Antegrade Endoscopic with Bridging Vein Harvesting for Improvement of Great Saphenous Vein Graft Quality from the Lower Leg
Published on: November 19, 2019
 08:05
Occlusion of the Great and Small Saphenous Vein Using Copolymeric Glue Based on N-Butyl Cyanoacrylate and Methacryloxy Sulfolane
Published on: December 9, 2022
Related Concept Videos
 01:17
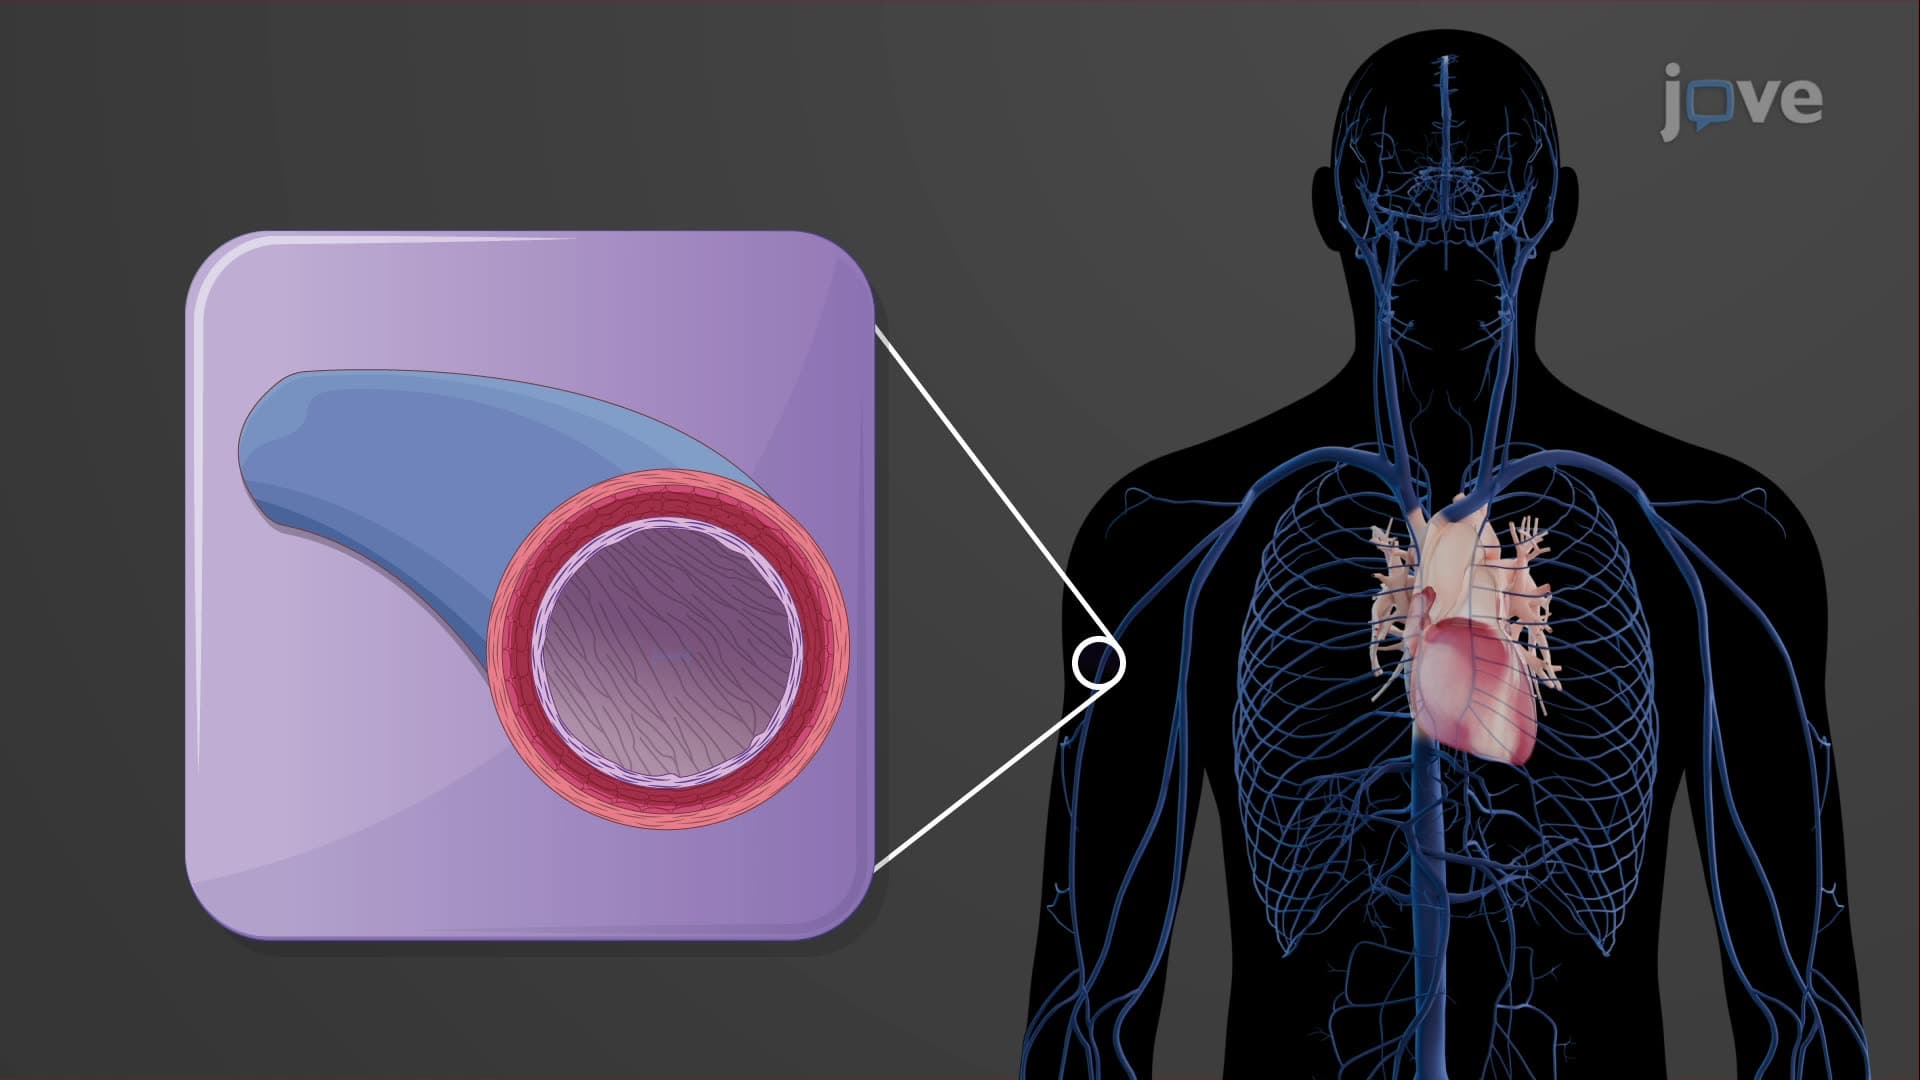
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:19
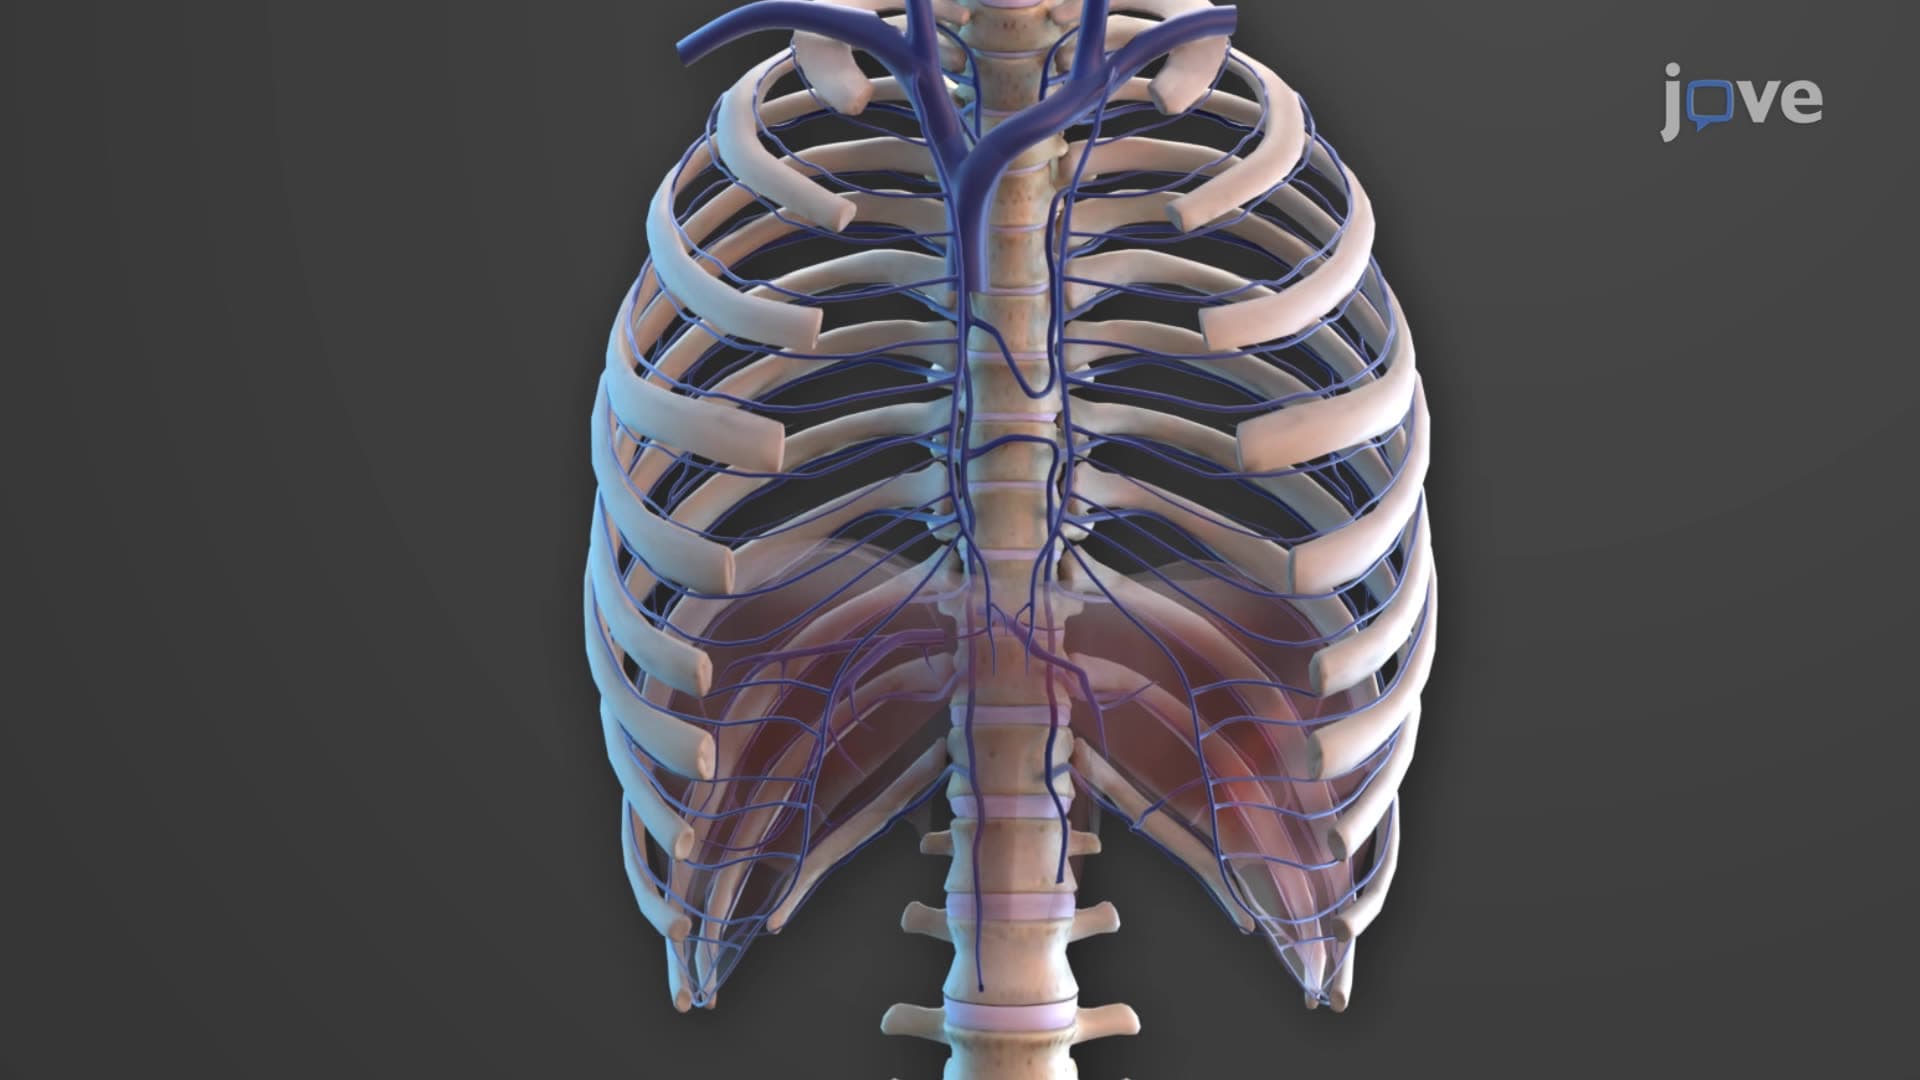
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:15
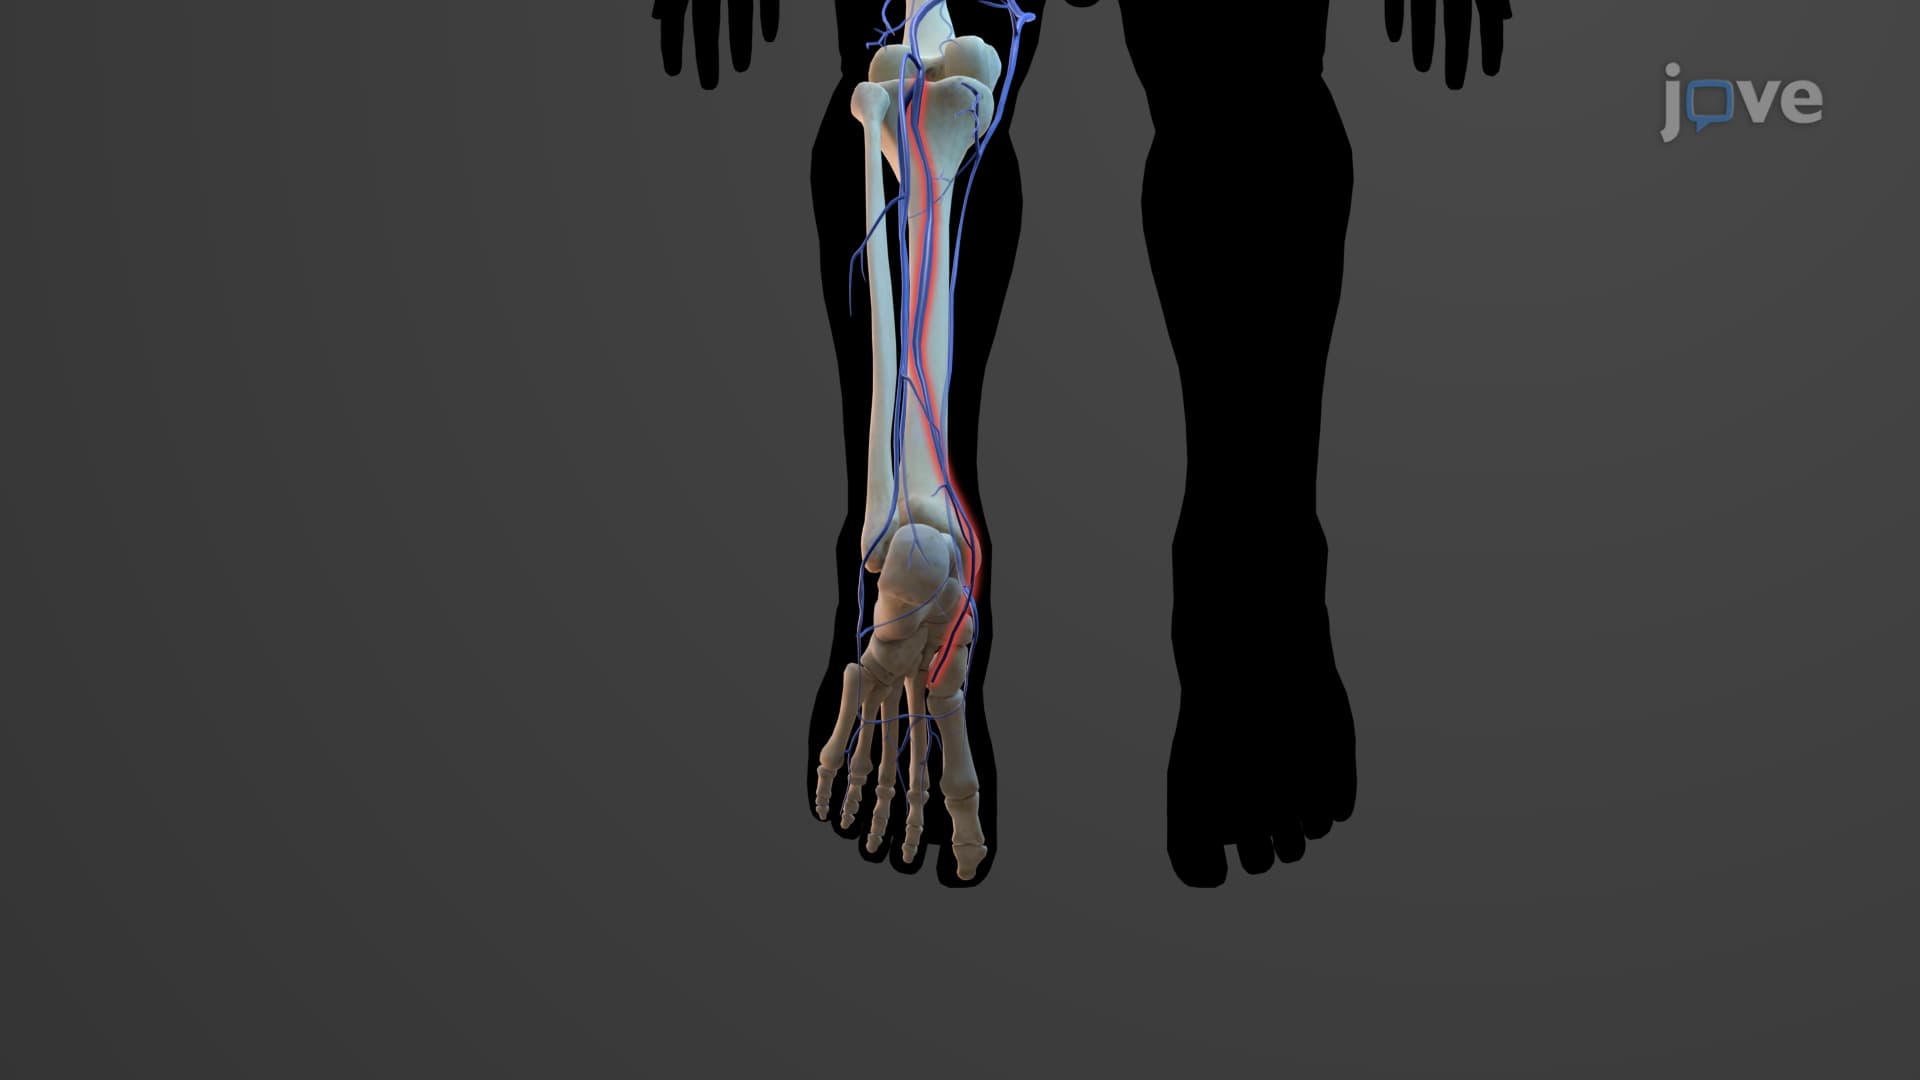
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:26
Varicose Veins I: Introduction
 01:10
Veins as Blood Reservoirs
 01:11
Overview of Systemic Veins
The coronary sinus, the heart's principal vein, resides in the coronary sulcus on the heart's posterior aspect. This broad venous channel receives nearly all venous blood from the myocardium, the heart muscle. It is fed by three primary veins: the great cardiac vein, the...