Related Experiment Video
Updated: Feb 14, 2026
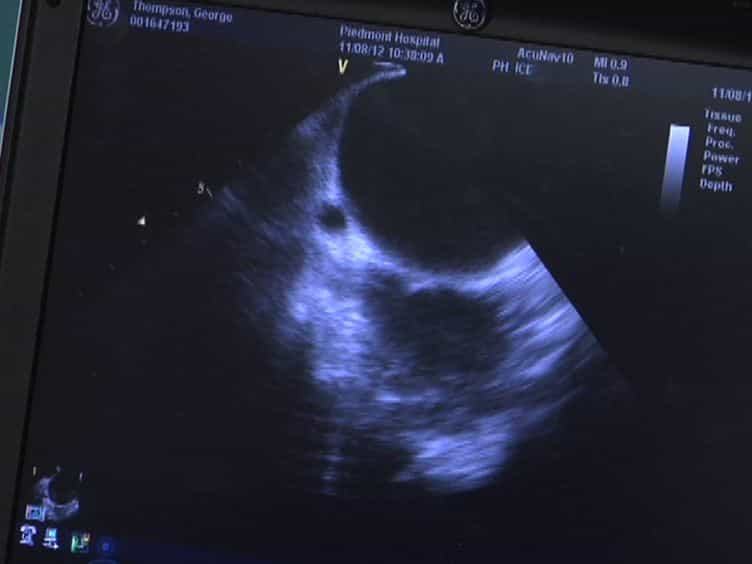

Direct Pressure Monitoring Accurately Predicts Pulmonary Vein Occlusion During Cryoballoon Ablation
Published on: February 26, 2013
Additional cryoapplications at the pulmonary vein antrum using a 28-mm second-generation cryoballoon: a pilot study
Shinsuke Miyazaki1,2, Takatsugu Kajiyama3, Tomonori Watanabe3
1Department of Cardiovascular Medicine, Fukui University, 23-3 Shimo-aiduki, Matsuoka, Eiheiji-cho, Yoshida-gun, Fukui, 910-1193, Japan. mshinsuke@k3.dion.ne.jp.

Abstract:
Isolation areas post-28-mm cryoballoon pulmonary vein isolation (CB-PVI) are smaller than post-radiofrequency PV antrum isolation at the left superior PV (LSPV) antrum and recurrent atrial fibrillation (AF) can originate from this area. This pilot study evaluated the impact of additional extra-PV CB applications at the LSPV antrum following conventional CB-PVI. Eighteen paroxysmal AF patients underwent CB-PVI with single 3-min freeze techniques. Following the CB-PVI, 2-min CB applications were added once or twice at the LSPV antrum. Before and after extra-PV ablation, left atrial (LA) 3-D electroanatomical maps were created. Seventy-two total PVs were successfully isolated with 4.2 ± 0.4 applications/patient with 28-mm CBs. The mean LA posterior wall (LAPW) and non-isolated LAPW areas were 14.9 ± 3.6 and 6.9 ± 2.8 cm2, respectively. After 1.6 ± 0.5 mean extra-PV applications, the upper non-isolated LAPW area significantly decreased from 3.3 ± 1.8 to 2.5 ± 1.8 cm2 (p < 0.001). The lowest esophageal temperatures during the extra-PV ablation were 27 °C. The total procedure and fluoroscopic times were 72.8 ± 13.1 and 15.2 ± 5.9 min, respectively. Silent gastric hypomotility was detected in 2/9 patients 1 day later, and mild PV stenosis was observed in 4/72 PVs 3 months later, but did not progress. At 12-month after single procedures, 16 (88.9%) patients were free from recurrent AF off antiarrhythmic drugs. A median of 8.0 [6.0-10.0] months later, PV reconnections were detected in 3/12 (25.0%) PVs. The non-isolated LAPW area was significantly larger in the chronic than acute phase (14.3 ± 5.2 cm2, p = 0.016). This pilot study suggested the potential feasibility of additional LSPV antral cryoapplications following a conventional CB-PVI. The strategy warrants further study in more patients.


Related Concept Videos
 01:17
Veins
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:19
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:15
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...