Related Experiment Video
Updated: Feb 13, 2026

Parameterizing V-notch Weir Equations for Flow Monitoring in a Drainage Control Structure
Published on: April 25, 2025
ICP Monitoring by Open Extraventricular Drainage: Common Practice but Not Suitable for Advanced Neuromonitoring and
Konstantin Hockel1, Martin U Schuhmann2
1Department of Neurosurgery, University Hospital Tübingen, University of Tübingen, Tübingen, Germany. konstantin.hockel@med.uni-tuebingen.de.

Objective:
A drawback in the use of an external ventricular drain (EVD) originates in the fact that draining cerebrospinal fluid (CSF) (open system) and intracranial pressure (ICP) monitoring can be done at the same time but is considered to be unreliable regarding the ICP trace. Furthermore, with the more widespread use of autoregulation monitoring using blood pressure and ICP signals, the question arises of whether an ICP signal from an open EVD can be used for this purpose. Using an EVD system with an integrated parenchymal ICP probe we compared the different traces of an ICP signal and their derived parameters under opened and closed CSF drainage.
Methods:
Twenty patients with either subarachnoid or intraventricular hemorrhage and indication for ventriculostomy plus ICP monitoring received an EVD in combination with an air-pouch-based ICP probe. ICP was monitored via an open ventricular catheter (ICP_evd) and ICP probe (ICP_probe) simultaneously. Neuromonitoring data (ICP, arterial blood pressure, cerebral perfusion pressure, pressure reactivity index (PRx)) were recorded by ICM+ software for the time of ICU intensive care treatment. Routinely (at least every 4 h) ICP was recorded with a closed CSF drainage system for at least 15 min. ICP, ICP amplitude, and the autoregulation parameters (PRx_probe, PRx_evd) were evaluated for every episode with closed CSF drainage and during the 3 h prior with an open drainage system.
Results:
One hundred and forty-four episodes with open/closed drainage were evaluated. During open drainage, overall mean ICP_evd levels were nonsignificantly different from those of ICP_probe, with 9.8 + 3.3 versus 8.2 + 3.2 mmHg, respectively. Limits of agreement ranged between 5.2 and -8.3 mmHg. However, 51 increases of ICP >20 mmHg with a duration of 3-30 min were missed by ICP_evd, and in 101 episodes the difference between ICPs was greater than 10 mmHg. After closure of the EVD, ICP increased moderately using both methods. Mean PRx_evd was significantly higher (falsely indicating impaired autoregulation) and more subjected to fluctuations than PRx_probe.
Conclusion:
The general practice of draining CSF and monitoring ICP via a (usually open) EVD plus frequently performed catheter closure for ICP reading is feasible for assessment of overall ICP trends. However, it does have clinically relevant drawbacks, namely, a significant amount of undetected increases in ICP above thresholds, and continuous assessment of cerebrovascular autoregulation is less reliable. In conclusion, all patients who need CSF drainage plus ICP monitoring due to the severity of their brain insult need either an EVD with integrated ICP probe or an EVD line plus a separate ICP probe.
More Related Videos
 08:53
Using a Classroom-Based Deese Roediger McDermott Paradigm to Assess the Effects of Imagery on False Memories
Published on: November 14, 2018
 07:44
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
Related Concept Videos
 01:18
False Memories
One primary source of false memories is misattribution, where individuals incorrectly associate external information...
 03:24
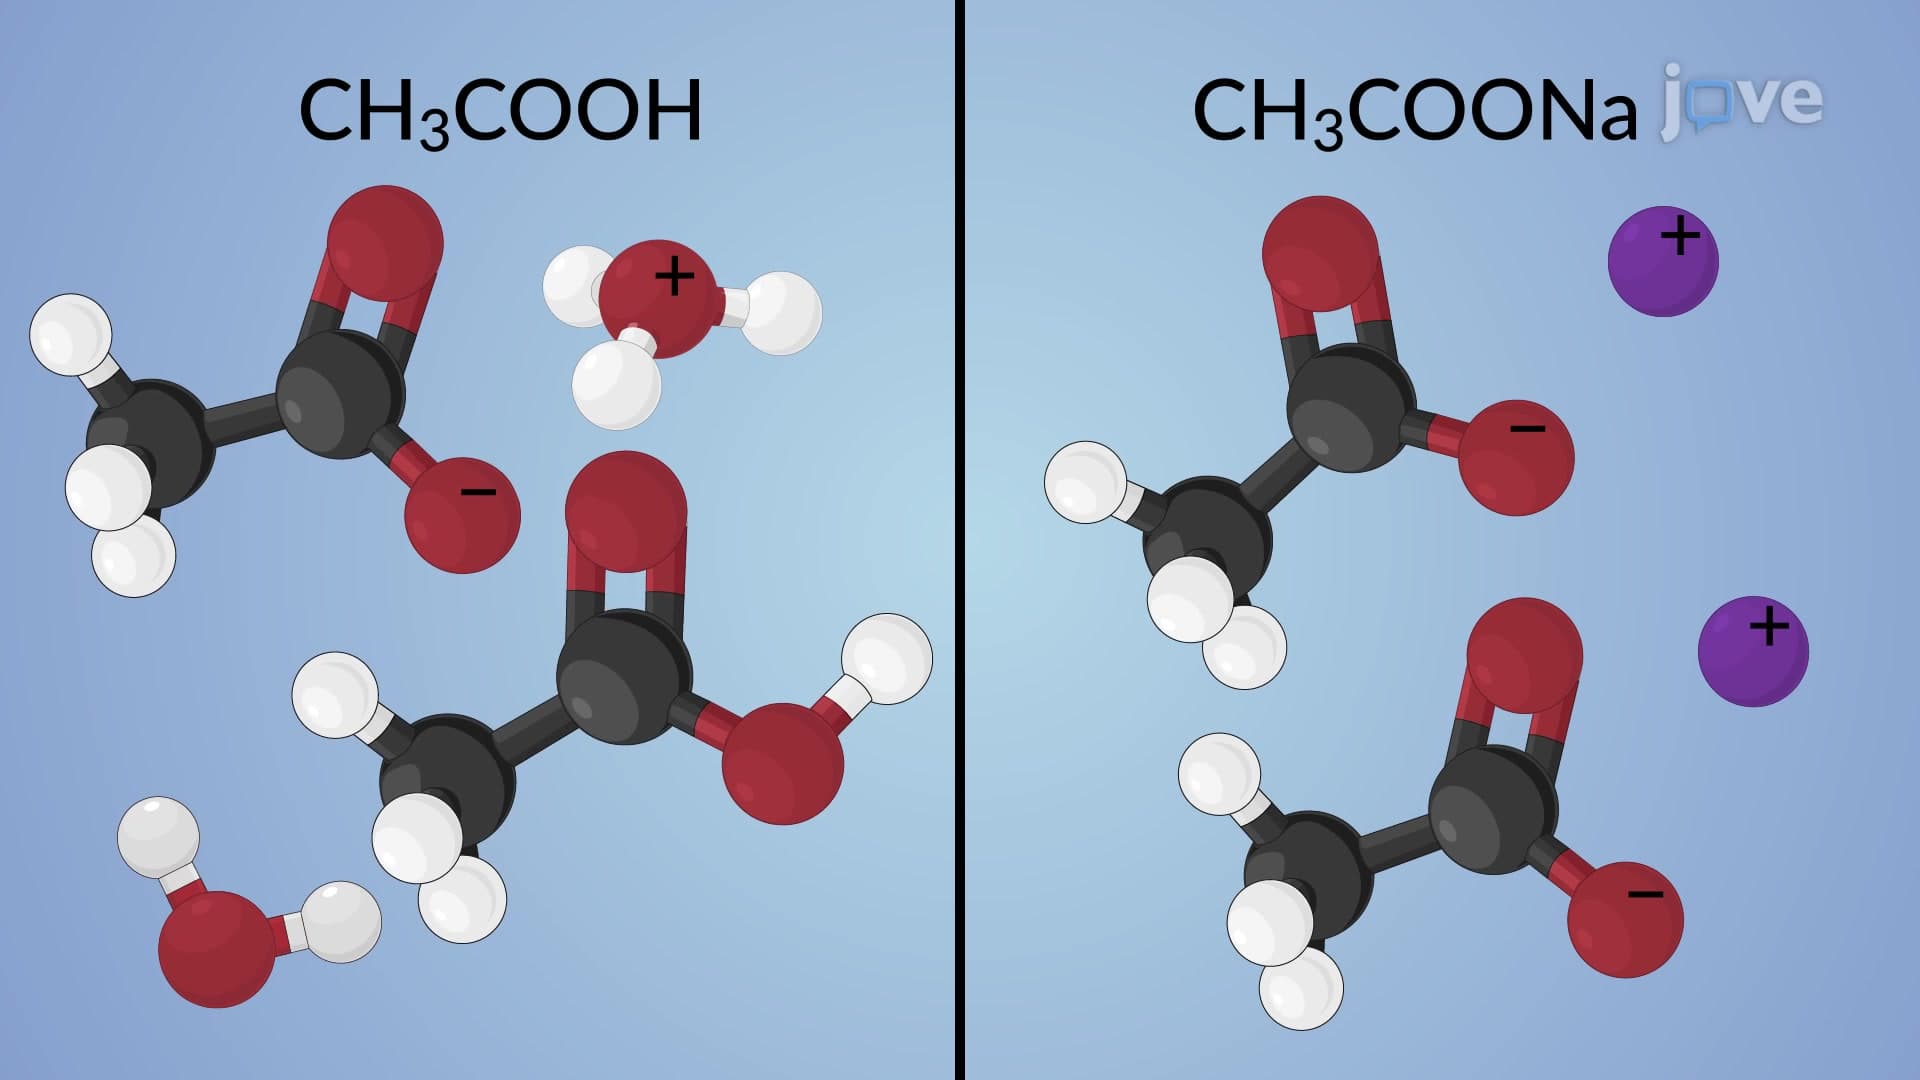
Common Ion Effect
 01:20
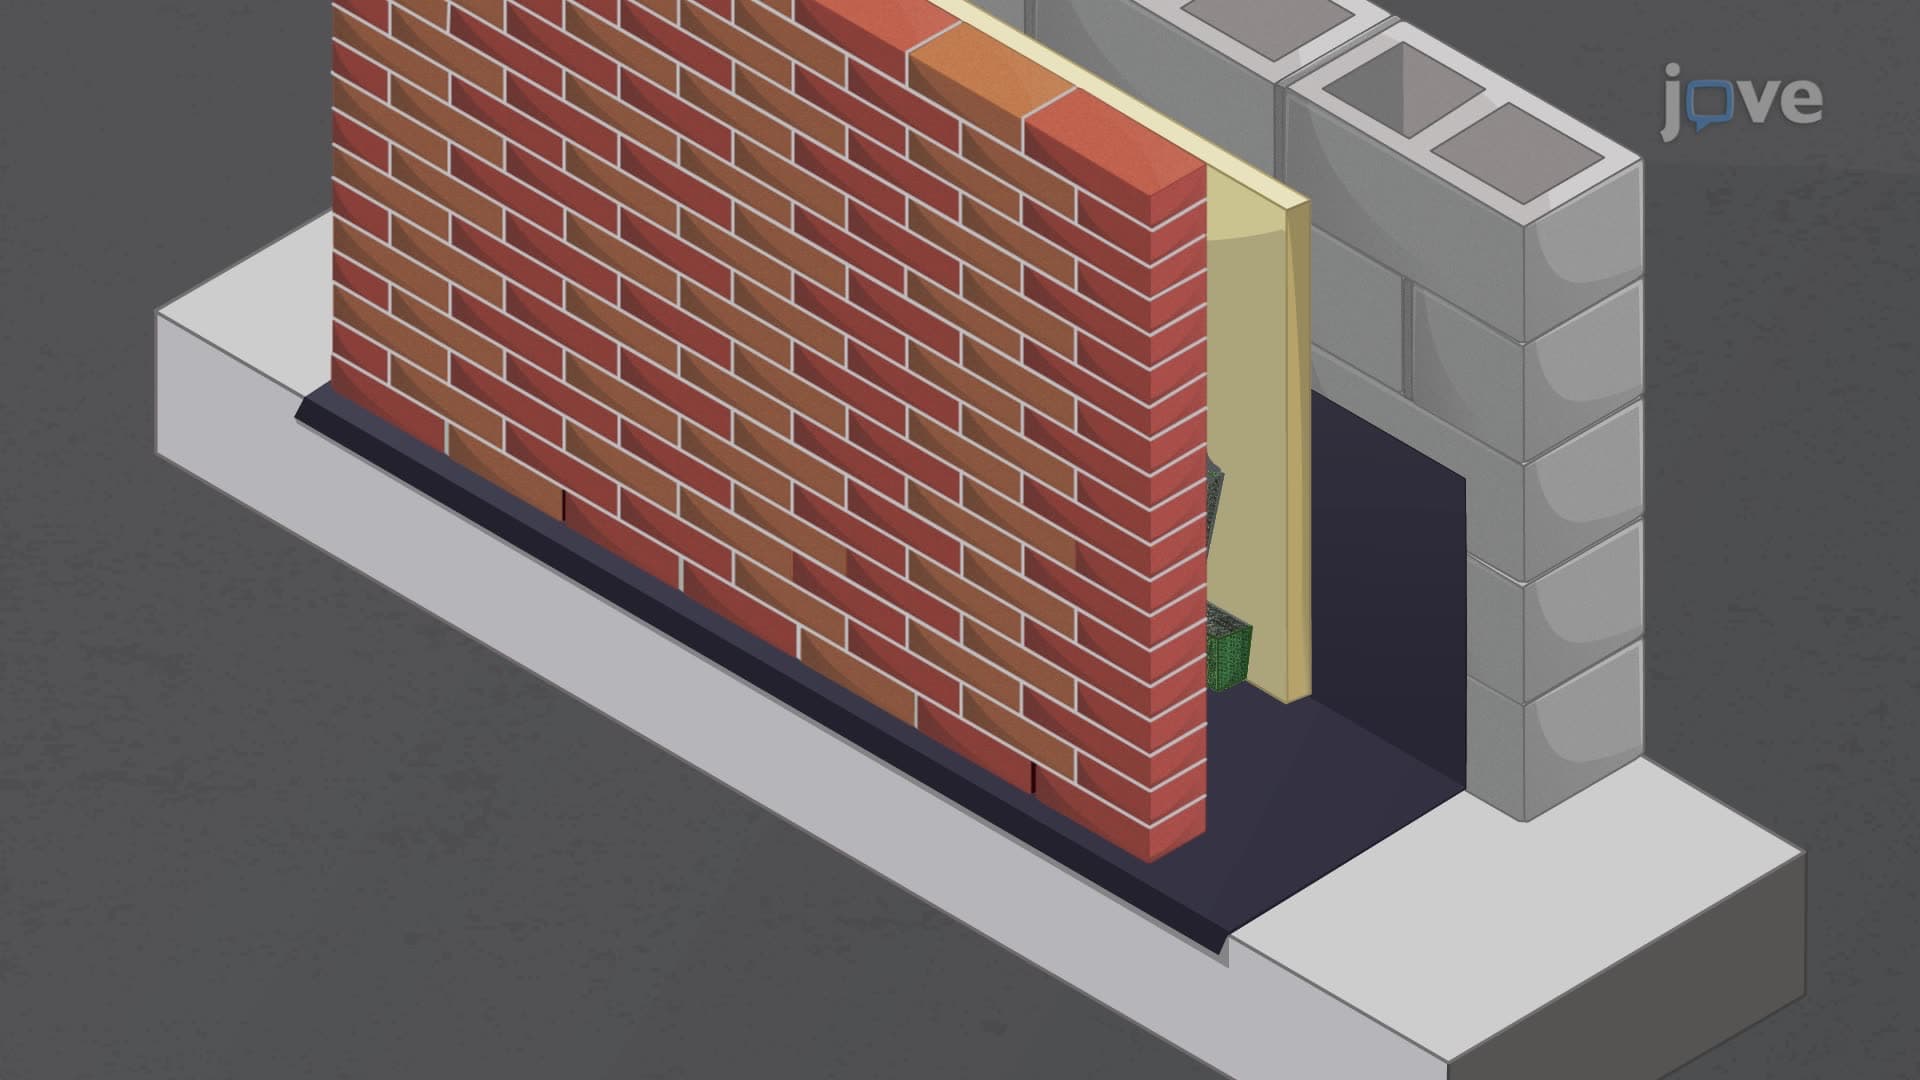
Cavity Drainage and Flashings in Masonry walls
Weep holes, strategically placed at the base of the cavity, are critical for draining accumulated water. These openings are created by leaving head...
 01:23
Negative Regulator Molecules
 00:58
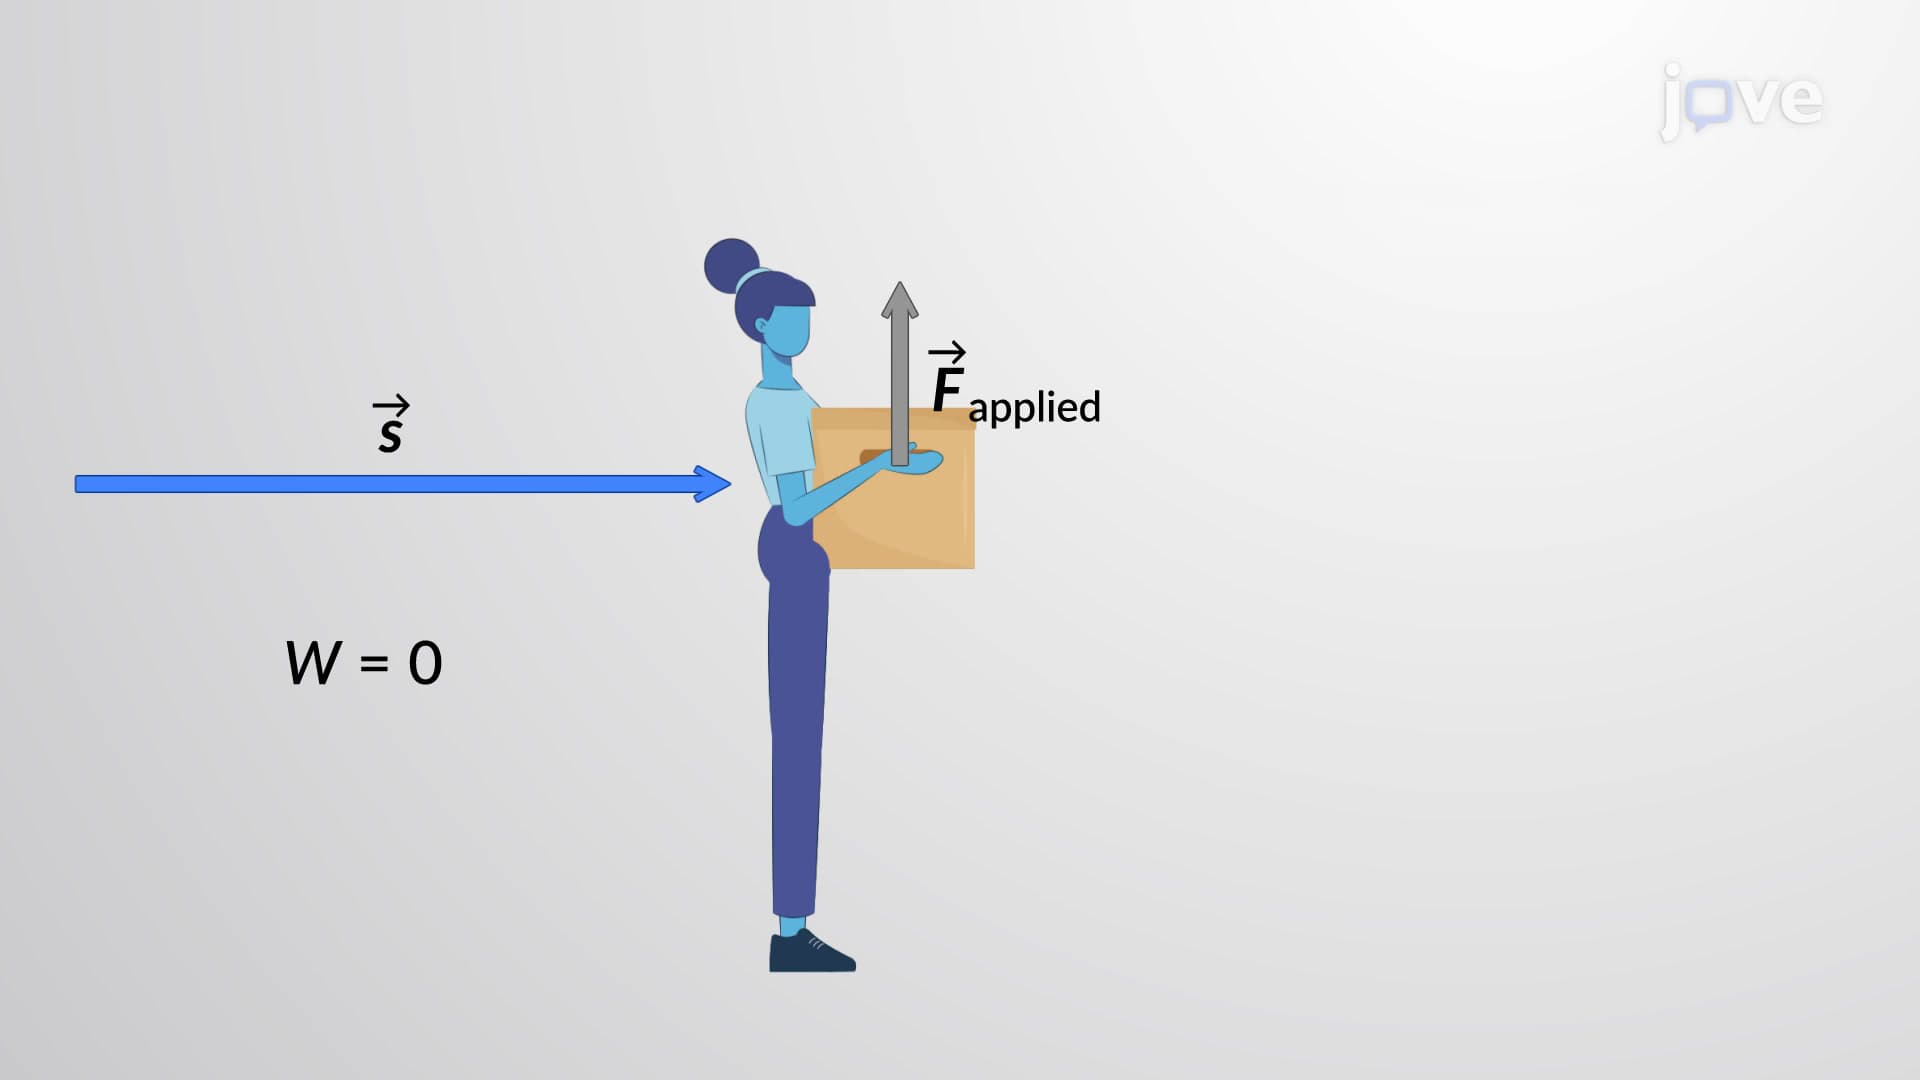
Positive, Negative, and Zero Work
 01:20
Inductively Coupled Plasma-Mass Spectrometry (ICP-MS): Interferences