Late Pancreatic Anastomosis Stricture Following Pancreaticoduodenectomy: a Systematic Review
Related Experiment Video
Updated: Feb 8, 2026
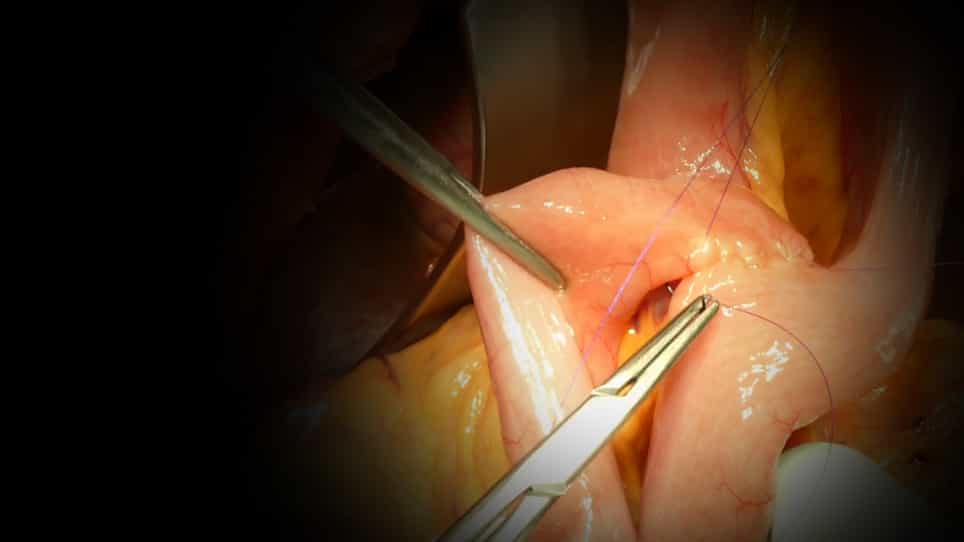
Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019
Alban Zarzavadjian Le Bian1, Manuela Cesaretti2, Nicolas Tabchouri3
1Department of Digestive Surgery and Surgical Oncology - Hôpital Avicenne, Assistance Publique - Hôpitaux de Paris, Université Paris XIII, 125 rue de Stalingrad, 93000, Bobigny, France. spleen2008@live.fr.

Background:
With an increasing postoperative survival and prolonged follow-up, late complications following pancreaticoduodenectomy (PD) have yet to be thoroughly described and analyzed. Among those, pancreatic anastomosis stricture may lead to severe consequences.
Methods:
A systematic review focusing on pancreaticojejunostomy anastomosis (PJA) stricture.
Results:
PJA stricture incidence reached 1.4-11.4% with a median time interval of 34 months after PD. No risk factor was identified. PJA stricture repercussions were inconsistent but postprandial abdominal pain and recurrent acute pancreatitis were the most common symptoms, followed by impaired pancreatic function. To confirm diagnosis, secretin-enhanced magnetic resonance cholangiopancreatography (SMRCP) sensitivity reached 56-100%. As impaired pancreatic function is not improved by any procedure, only PJA stricture leading to abdominal pain or acute pancreatitis should be considered for treatment. Endoscopic techniques (mainly ultrasound-assisted "rendezvous") should be proposed prior to surgical repair, with a morbidity, an overall technical and clinical success reaching 16.5-33% and 28.6-100% and 33-100%, respectively. Regarding surgical repair, overall morbidity varied between 14.3 and 33%, with a clinical success reaching 26.1-100%. Finally, total pancreatectomy with islet auto-transplantation should be considered only for pain intractable to medical management and recurrent acute pancreatitis which has failed medical, endoscopic, and traditional surgical management strategies.
Conclusion:
PJA stricture following PD is a late, unusual, and potentially serious complication. When there is currently no clear consensus, PJA stricture leading to abdominal pain or acute pancreatitis should be considered treatment. With increasing survival after PD, further studies should focus on late complications.
Core Tip:
Stricture of pancraticojejunostomy is a late and potentially serious complication after pancreaticoduodenectomy. Incidence reaches 1.4-11.4% and no risk factor is identified. Symptoms are inconsistent but postprandial abdominal pain, recurrent acute pancreatitis, and impaired pancreatic function are the most frequent. To confirm diagnosis, secretin-enhanced magnetic resonance cholangiopancreatography is the best modality. Only PJA stricture leading to abdominal pain or acute pancreatitis should be considered for treatment. Endoscopic techniques (mainly ultrasound-assisted "rendezvous") should be proposed prior to surgical repair. Finally, total pancreatectomy with islet auto-transplantation should be considered only for pain intractable to medical management and recurrent acute pancreatitis which has failed medical, endoscopic, and traditional surgical management strategies.
Related Concept Videos
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:20
Random and Systematic Errors
 01:17
Systematic Sampling Method
Systematic sampling is one of the simplest methods...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...