Related Experiment Video
Updated: Feb 5, 2026
Duodenal-Jejunal Bypass Surgery in Diet-Induced Obese Diabetic Mice
Published on: October 18, 2024
Cerebral Bypass Surgery: Level of Evidence and Grade of Recommendation
Giuseppe Esposito1, Martina Sebök2, Sepideh Amin-Hanjani3
1Department of Neurosurgery, University Hospital Zurich, University of Zurich, Zürich, Switzerland. giuseppe.esposito@usz.ch.

Insights
Cerebral bypass surgery indications are narrowing for ischemic conditions. However, bypass remains crucial for complex aneurysms and Moyamoya disease with hemodynamic compromise.
Area of Science:
- Neurosurgery
- Vascular Surgery
- Neurology
Background:
- Cerebral bypass surgery is categorized by function (flow augmentation/preservation) and type (direct/indirect, intra/extracranial, capacity).
- Current evidence and recommendations for cerebral bypass surgery require critical summarization.
Purpose of the Study:
- To critically summarize the current state of evidence and grades of recommendation for cerebral bypass surgery.
- To discuss indications for cerebral bypass based on function (flow preservation or augmentation) and analyze them according to level of evidence criteria.
Main Methods:
- Review of current literature and evidence grading for cerebral bypass indications.
- Analysis of bypass function (flow preservation vs. augmentation) in relation to specific cerebrovascular conditions.
Main Results:
- Flow-preservation bypass is important for complex intracranial aneurysms (Level 4; Grade C) but rarely indicated for tumors involving major cerebral arteries (Level 5; Grade D).
- Flow-augmentation bypass is recommended for Moyamoya patients with ischemic symptoms and hemodynamic compromise (Level 4; Grade C) or hemorrhagic onset (Level 1B; Grade A).
- Flow-augmentation bypass is not recommended for symptomatic carotid occlusion (Level 1A; Grade A) but may be considered as a last resort for refractory symptoms (Level 5; Grade D).
Conclusions:
- Recent trials narrow indications for cerebral bypass in ischemic cerebrovascular disease.
- Cerebral bypass remains essential for complex intracranial aneurysms untreatable by other methods.
- Cerebral bypass is the sole treatment for symptomatic Moyamoya vasculopathy with impaired brain hemodynamics.
Background And Aims:
Cerebral bypasses are categorized according to function (flow augmentation or flow preservation) and to characteristics: direct, indirect or combined bypass, extra-to-intracranial or intra-to-intracranial bypass, and high-, moderate- or low-capacity bypass. We critically summarize the current state of evidence and grades of recommendation for cerebral bypass surgery.
Methods:
The current indications for cerebral bypass are discussed depending on the function of the bypass (flow preservation or augmentation) and analyzed according to level of evidence criteria.
Results:
Flow-preservation bypass plays an important role in managing complex intracranial aneurysms (level of evidence 4; grade of recommendation C). Flow-preservation bypass is currently only very rarely indicated in the treatment of cerebral tumors involving major cerebral arteries (level of evidence 5; grade of recommendation D). The trend has evolved in favor of partial resection and radiotherapy. To preserve the flow, the bypass is always a direct bypass.Flow-augmentation bypass is currently recommended for Moyamoya patients with ischemic symptoms and compromised hemodynamics (level of evidence 4; grade of recommendation C) and patients with hemorrhagic onset (level of evidence 1B; grade of recommendation A). Flow-augmentation bypass is currently not recommended for patients with recently symptomatic carotid artery occlusion, even in the setting of compromised cerebral hemodynamics (level of evidence 1A; grade of recommendation A), but may be considered in patients with hemodynamic failure and recurrent medically refractory symptoms as a final resort (level of evidence 5; grade of recommendation D).
Conclusions:
The results of recent randomized clinical trials narrow the indication for cerebral bypass in the setting of ischemic cerebrovascular disease. However, cerebral bypass is still very useful for managing complex intracranial aneurysms (not amenable to selective clipping or endovascular therapies) and is the only treatment option for managing symptomatic patients with Moyamoya vasculopathy and impaired brain hemodynamics.


Related Concept Videos
 02:55
The Evidence for Evolution
 01:19
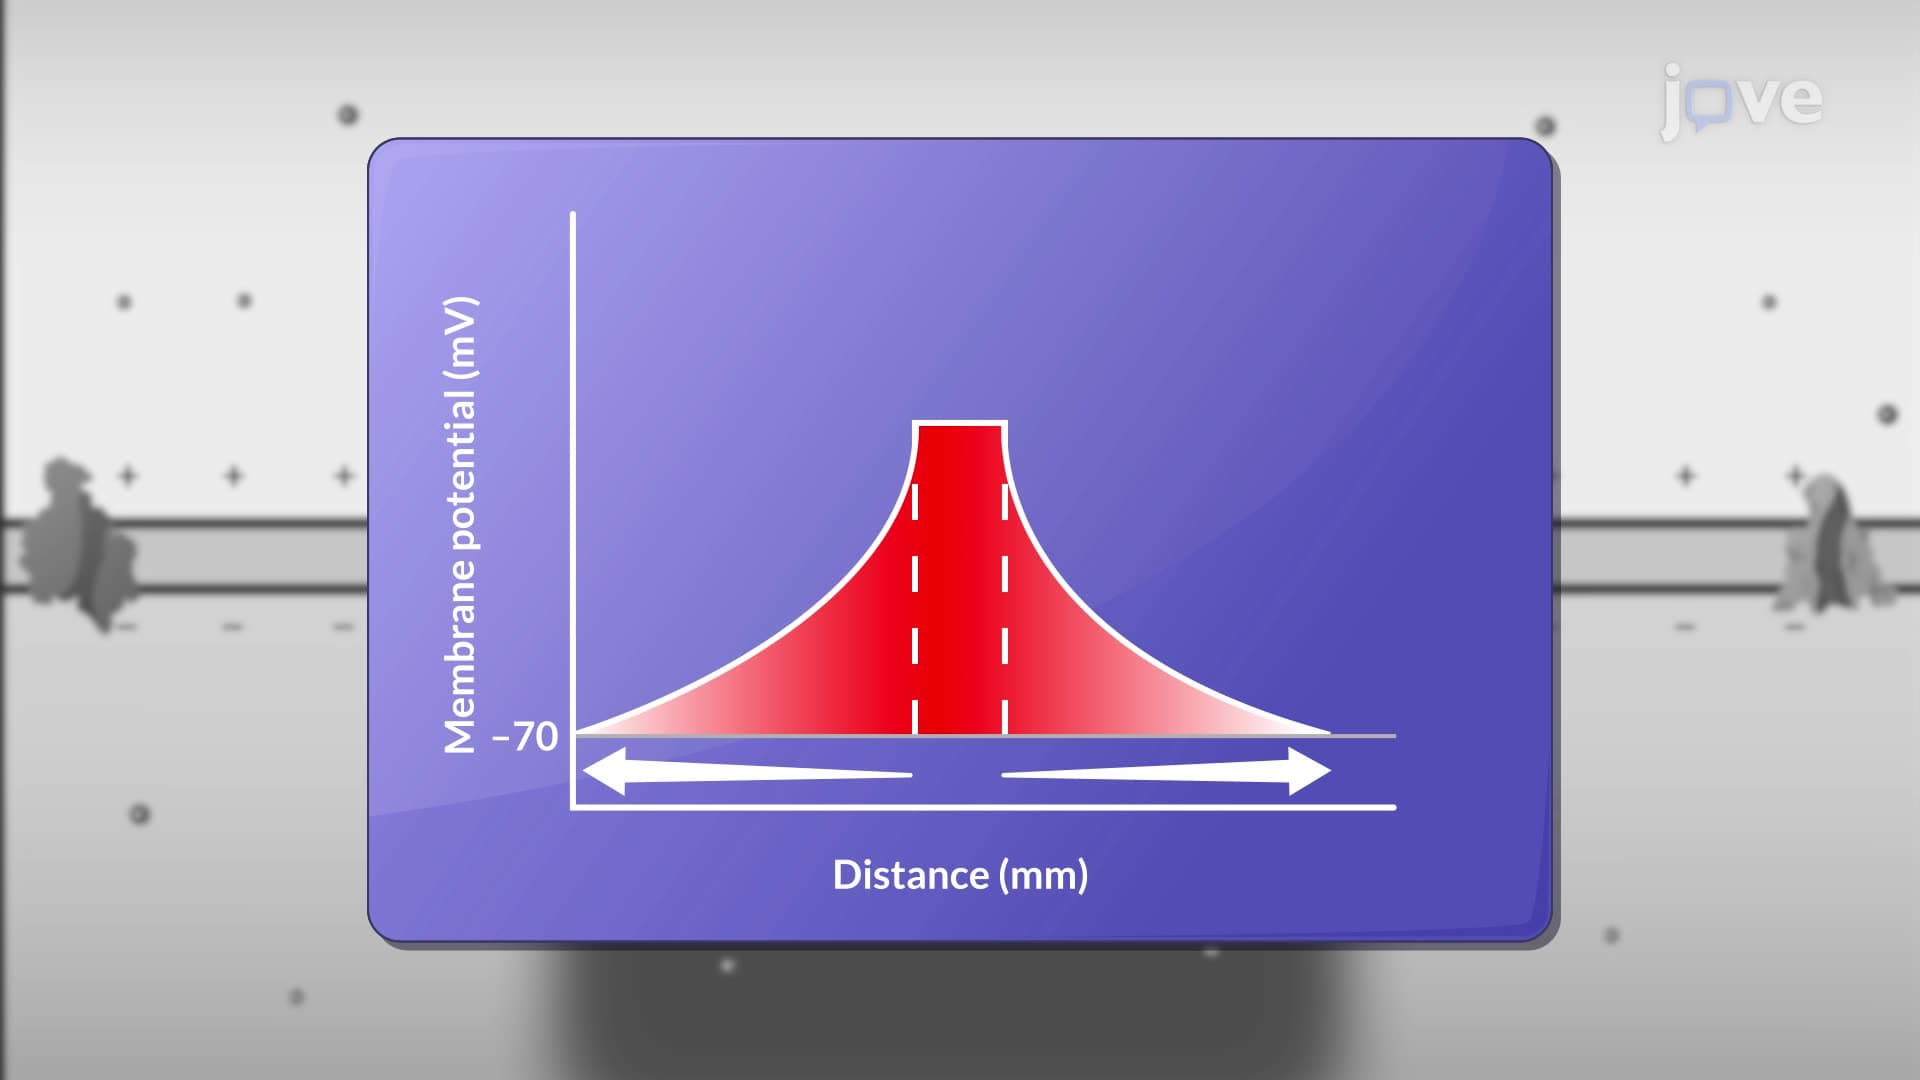
Graded Potential
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:15
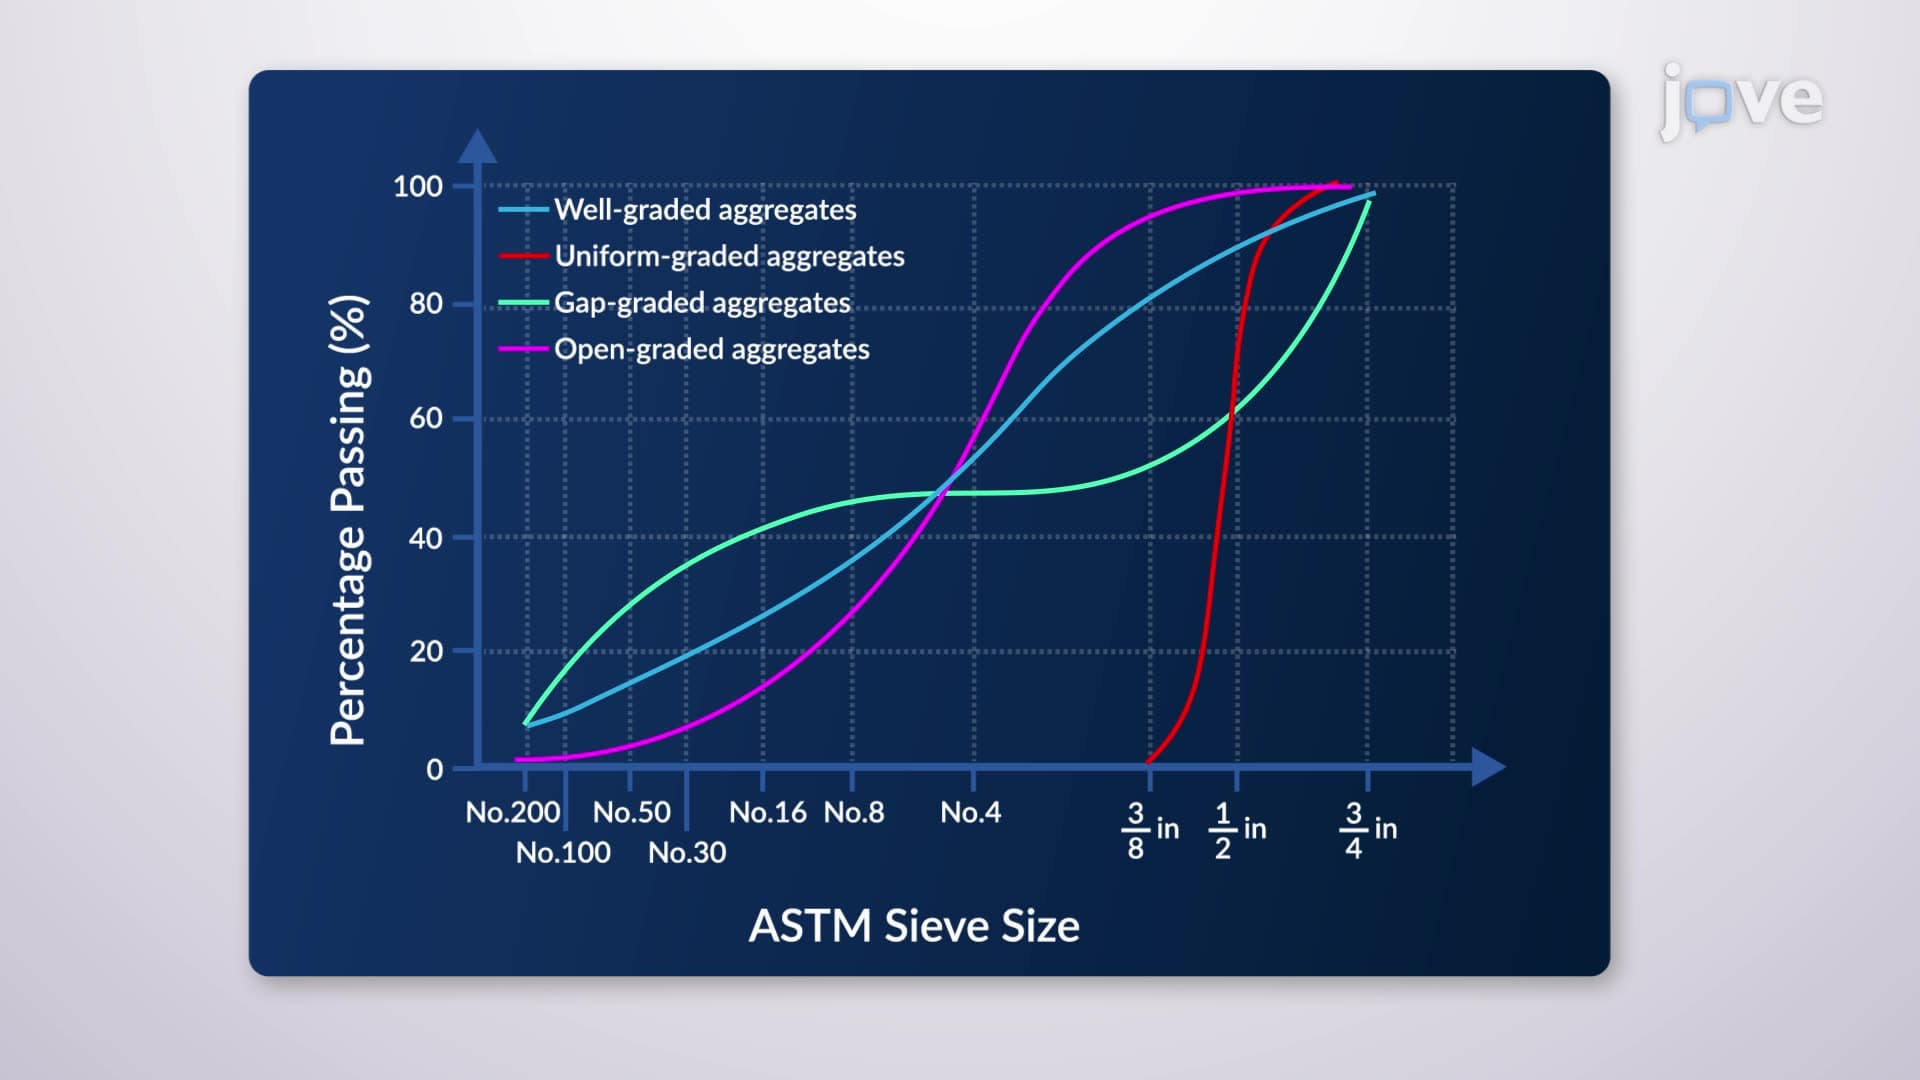
Types of Aggregate Grading
Well-graded aggregates include a complete range of necessary size fractions that fit together to create a dense matrix with minimal voids, represented by a smooth, continuous gradation curve. This type of grading ensures good...
 01:29
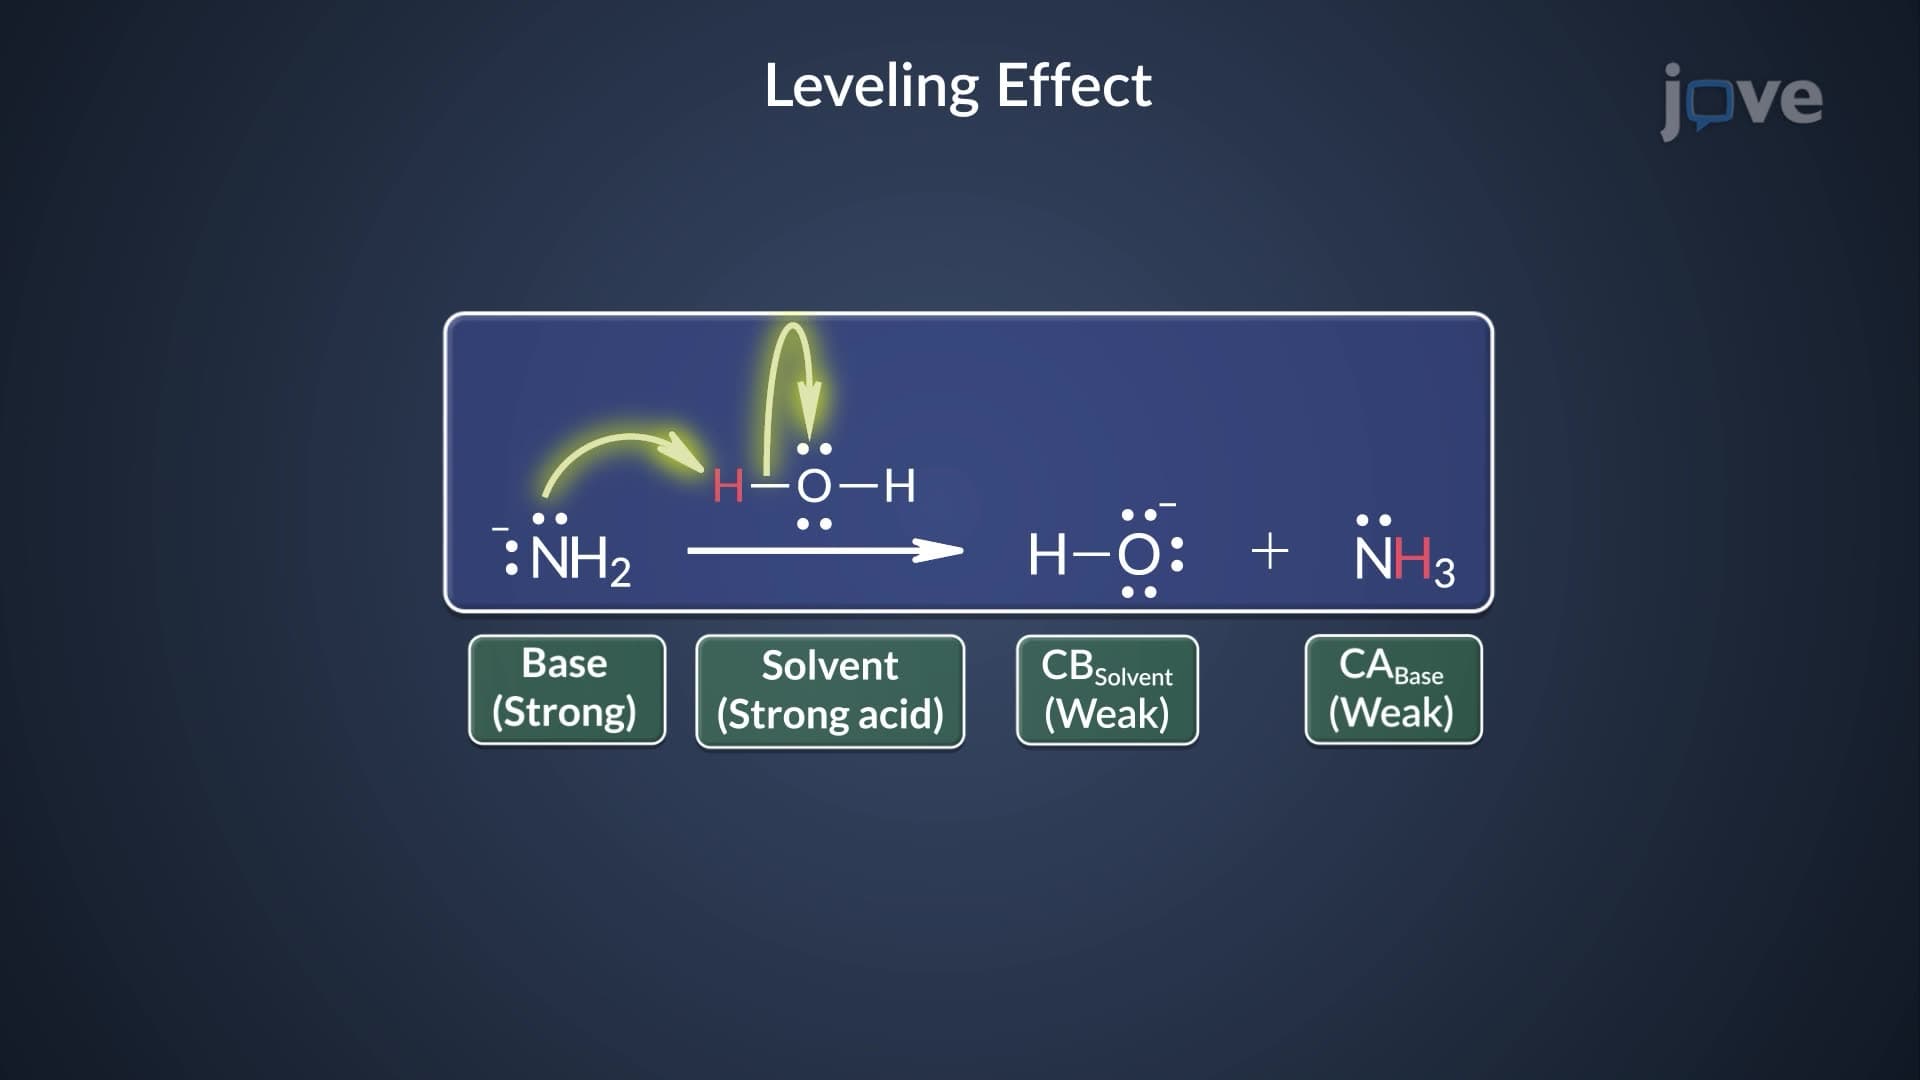
Leveling Effect
 01:19
Sieve Analysis and Grading Curves
 01:19
High-Level and Low-Level Awareness