Related Experiment Video
Updated: Feb 5, 2026


A Protocol for Lentiviral Transduction and Downstream Analysis of Intestinal Organoids
Published on: April 20, 2015
Intestinal and non-intestinal nasal cavity adenocarcinoma: Impact of wood dust exposure
P Gallet1, D T Nguyen2, A Russel2
1Service d'ORL et de chirurgie cervico-faciale, hôpitaux de Brabois, institut Louis-Mathieu, CHRU de Nancy, rue du Morvan, 54511 Vandoeuvre-les-Nancy cedex, France; Unité Inserm U954, nutrition génétique et exposition aux risques environnementaux, 54505 Vandoeuvre-les-Nancy cedex, France.

Abstract:
The aim of the present study was to investigate the role of wood dust exposure in intestinal (ITAC) and non-intestinal type (non-ITAC) nasal adenocarcinoma, so as to improve understanding of the oncogenic mechanisms in the light of the recent literature and of evo-devo concepts.
Materials And Methods:
All consecutive patients operated in our institution for nasal adenocarcinoma diagnosed on anatomopathology between May 2004 and February 2014 were included. Surgical specimens were examined twice by independent pathologists, blind to wood dust exposure status. Clinical and demographic data, including wood dust exposure, were collected for the two groups (ITAC and non-IATC).
Results:
90 patients (84 ITAC, 6 non-ITAC) were included. No non-ITAC patients had history of wood dust exposure, versus 83/84 cases (99%) in ITAC (mean exposure duration: 30±16 years; range 2-65 years). Only 12 ITAC patients (18%) were still exposed at diagnosis. ITAC may develop long after the end of wood dust exposure (up to 60 years). Eight patients (12%) had exposure durations of less than 5 years. Latency between onset of exposure and onset of disease did not decrease with exposure duration.
Conclusion:
Exposure to wood dust, even for short periods of time, incurs a risk of developing ITAC, usually after a long latency period. Any exposure requires lifetime follow-up, to ensure prompt treatment. Factors leading to the development of nasal ITAC and non-ITAC are probably different. The analogy with Barret's esophagus and esophageal adenocarcinoma may shed light on the oncogenesis of nasal ITAC.
More Related Videos
Related Concept Videos
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:24
Nose and Nasal Cavity
 01:15
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
Large Intestine
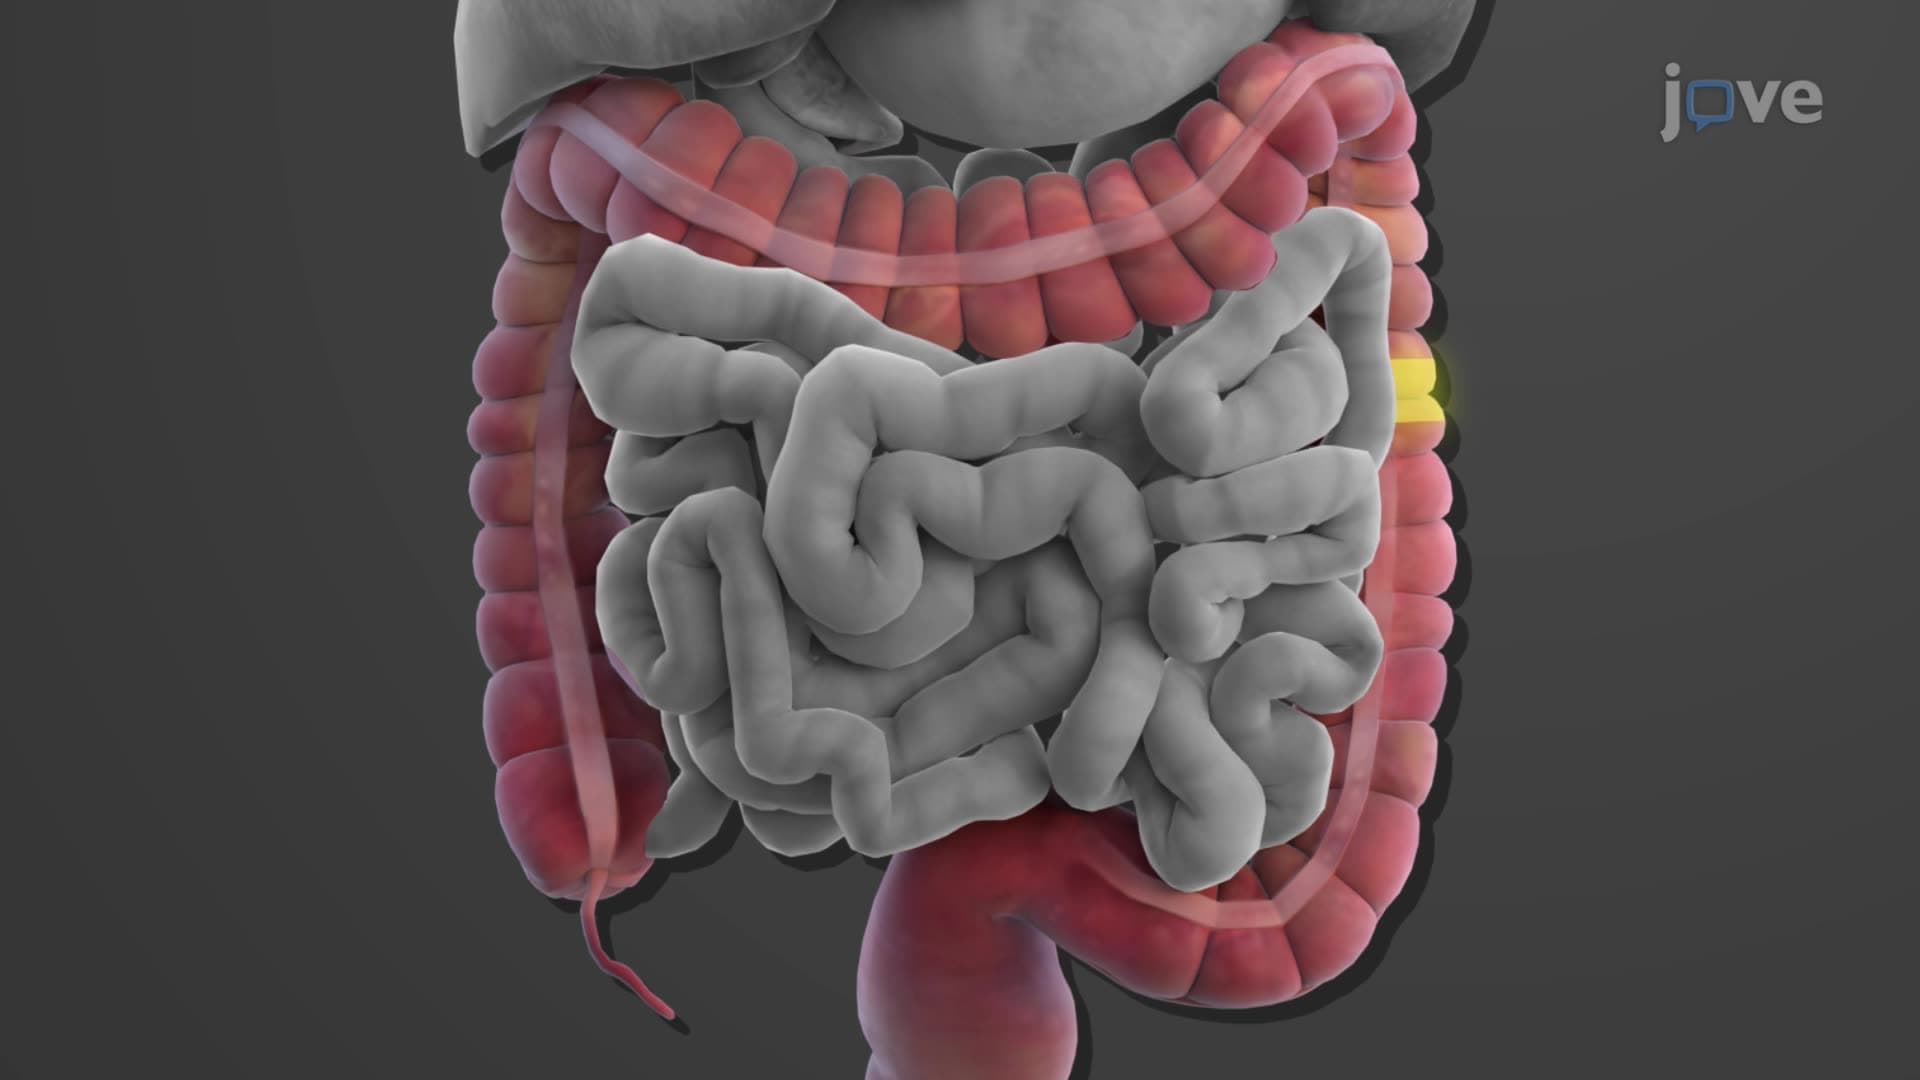
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
Histology of the Large Intestine
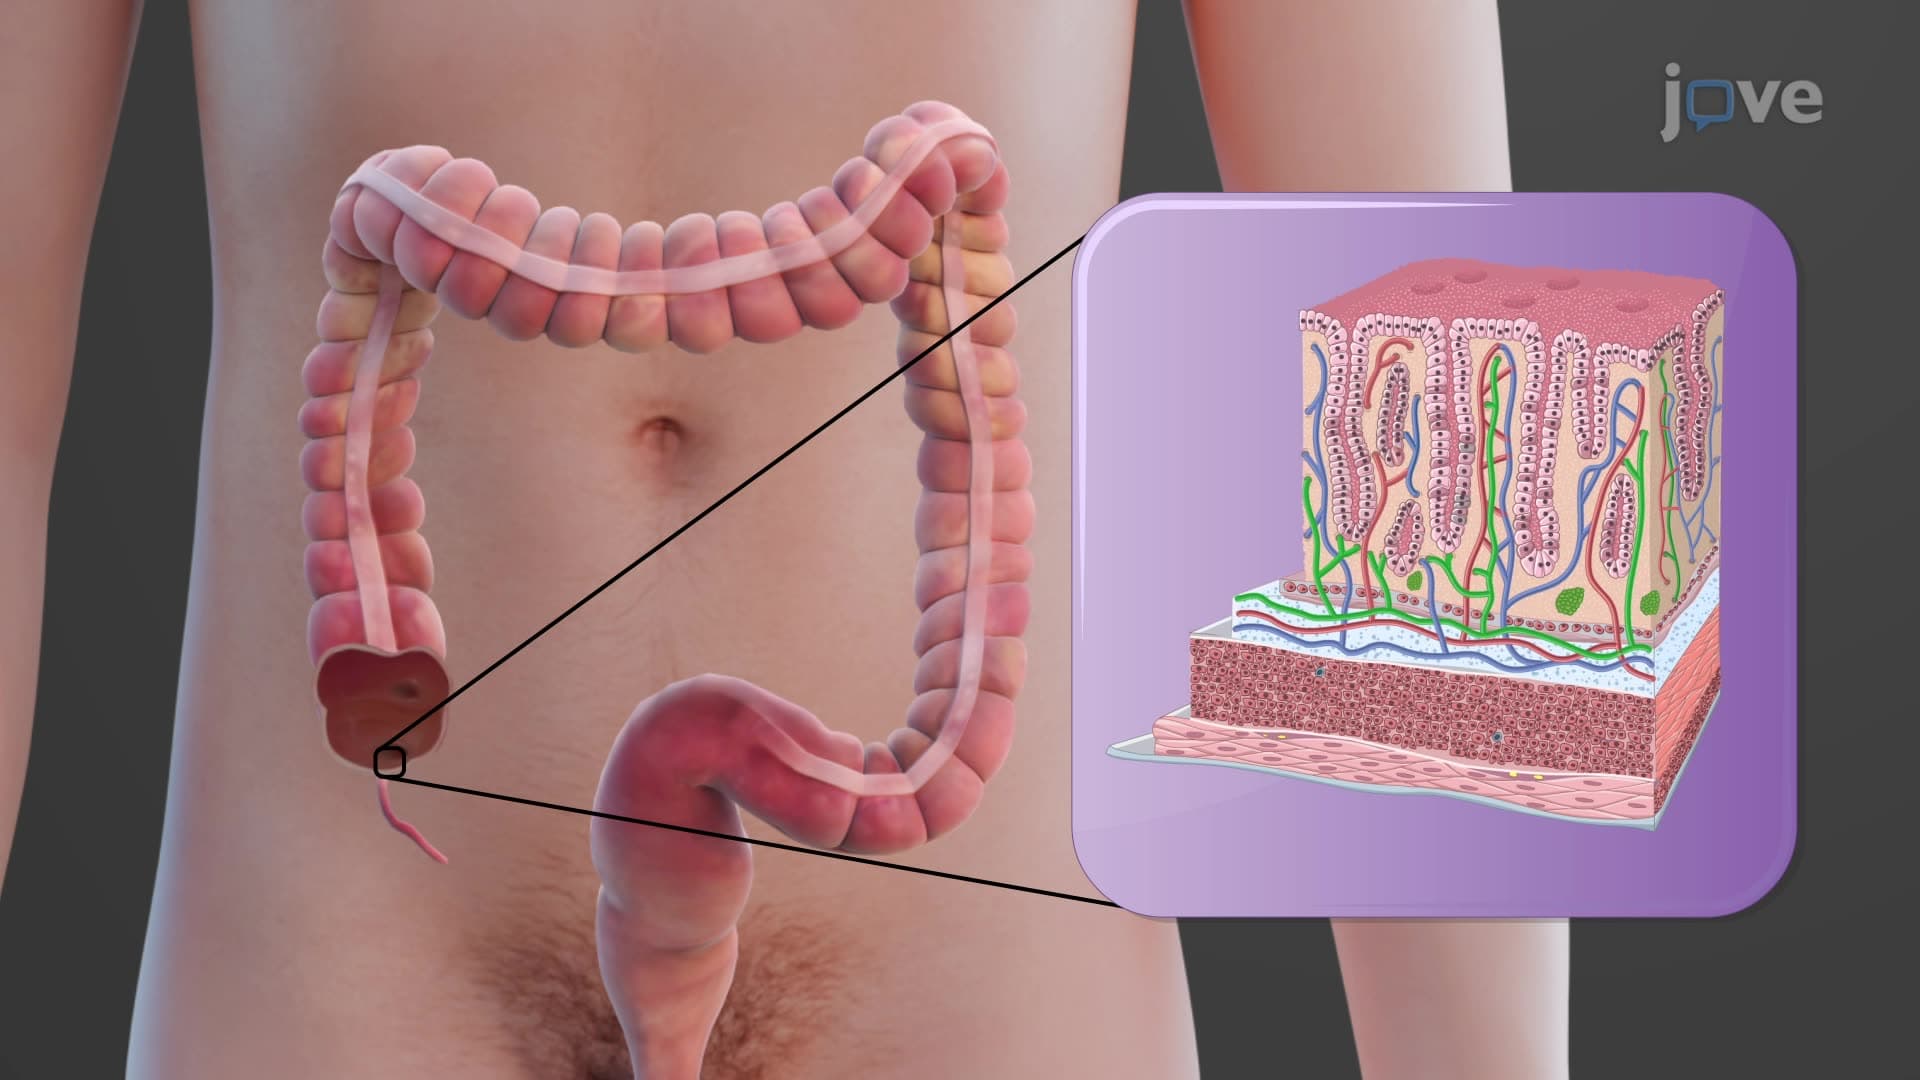
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
Histology of the Small Intestine
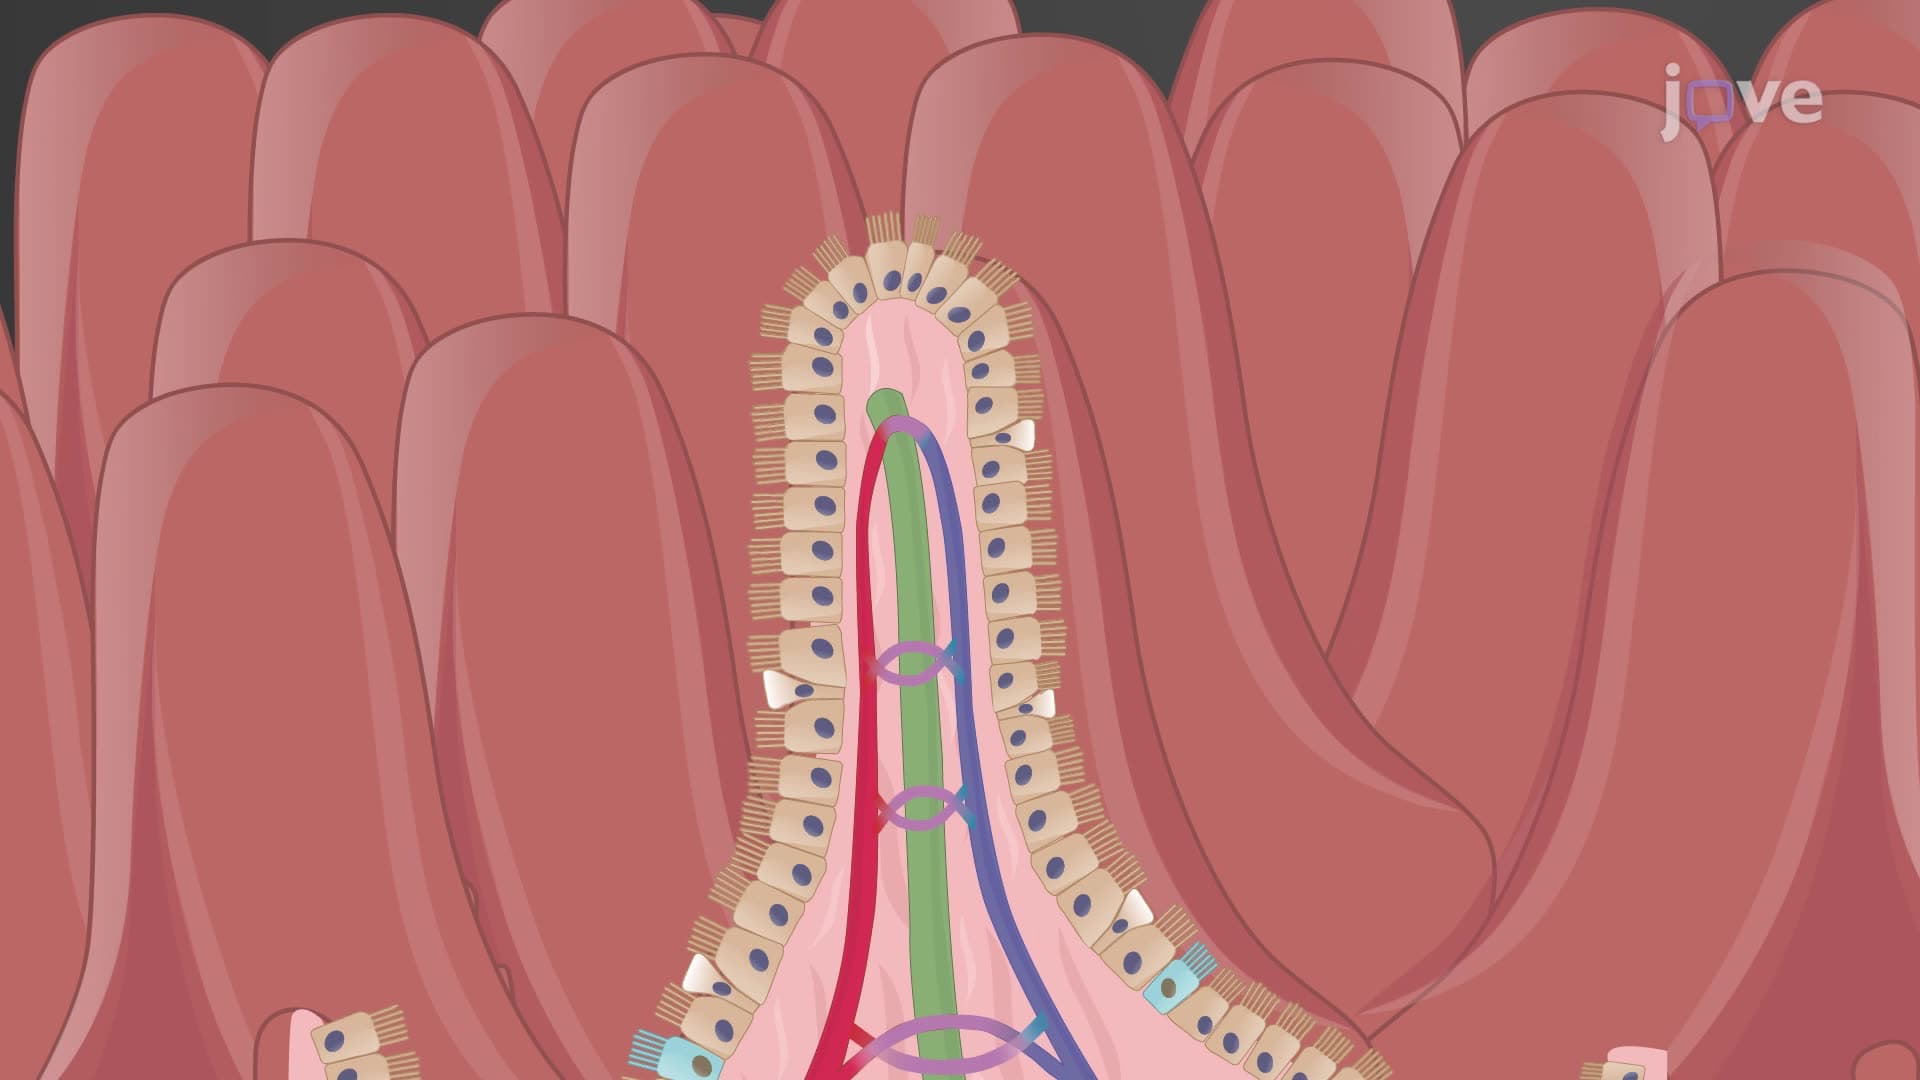
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...