Related Experiment Video
Updated: Jan 28, 2026
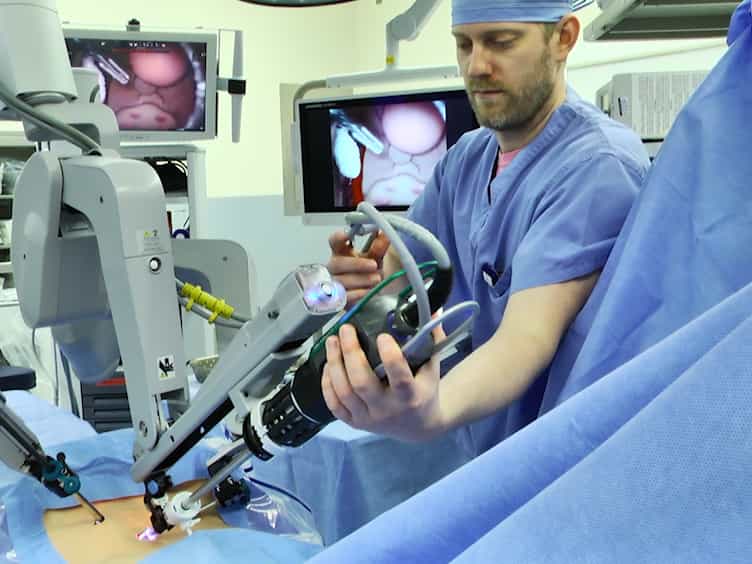

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Transition to active learning in rural Nepal: an adaptable and scalable curriculum development model
Stephen Mehanni1,2,3, Lena Wong1,2,4, Bibhav Acharya1,5
1Possible, Kathmandu, Nepal.

Background:
Traditional medical education in much of the world has historically relied on passive learning. Although active learning has been in the medical education literature for decades, its incorporation into practice has been inconsistent. We describe and analyze the implementation of a multidisciplinary continuing medical education curriculum in a rural Nepali district hospital, for which a core objective was an organizational shift towards active learning.
Methods:
The intervention occurred in a district hospital in remote Nepal, staffed primarily by mid-level providers. Before the intervention, education sessions included traditional didactics. We conducted a mixed-methods needs assessment to determine the content and educational strategies for a revised curriculum. Our goal was to develop an effective, relevant, and acceptable curriculum, which could facilitate active learning. As part of the intervention, physicians acted as both learners and teachers by creating and delivering lectures. Presenters used lecture templates to prioritize clarity, relevance, and audience engagement, including discussion questions and clinical cases. Two 6-month curricular cycles were completed during the study period. Daily lecture evaluations assessed ease of understanding, relevance, clinical practice change, and participation. Periodic lecture audits recorded learner talk-time, the proportion of lecture time during which learners were talking, as a surrogate for active learning. Feedback from evaluation and audit results was provided to presenters, and pre- and post-curriculum knowledge assessment exams were conducted.
Results:
Lecture audits showed a significant increase in learner talk-time, from 14% at baseline to 30% between months 3-6, maintained at 31% through months 6-12. Lecture evaluations demonstrated satisfaction with the curriculum. Pre- and post-curriculum knowledge assessment scores improved from 50 to 64% (difference 13.3% ± 4.5%, p = 0.006). As an outcome for the measure of organizational change, the curriculum was replicated at an additional clinical site.
Conclusion:
We demonstrate that active learning can be facilitated by implementing a new educational strategy. Lecture audits proved useful for internal program improvement. The components of the intervention which are transferable to other rural settings include the use of learners as teachers, lecture templates, and provision of immediate feedback. This curricular model could be adapted to similar settings in Nepal, and globally.

Related Concept Videos
 02:31
Phase Transitions
 01:58
Cooperative Allosteric Transitions
01:58Cooperative Allosteric Transitions
 02:58
Properties of Transition Metals
 02:39
Phase Transitions: Vaporization and Condensation
 02:33
Phase Transitions: Sublimation and Deposition