Related Experiment Video
Updated: Jan 28, 2026
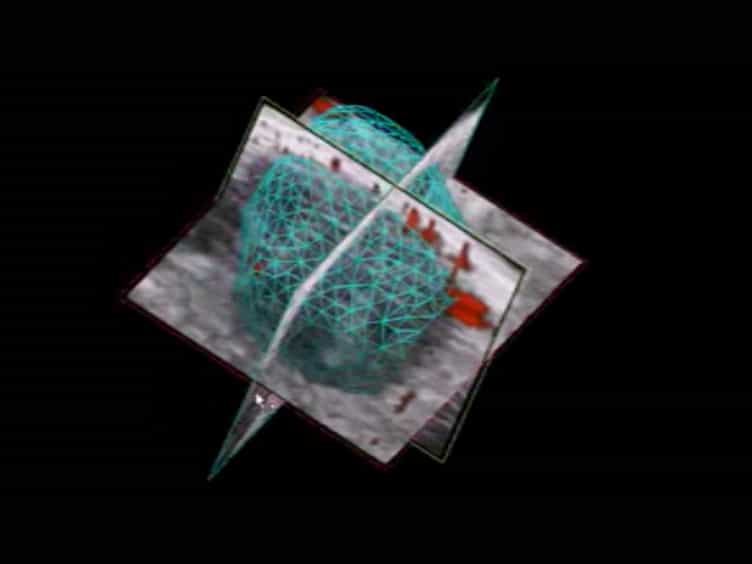

High-frequency Ultrasound Imaging of Mouse Cervical Lymph Nodes
Published on: July 25, 2015
Unilateral or bilateral irradiation in cervical lymph node metastases of unknown primary? A retrospective cohort
Carole Pflumio1, Idriss Troussier2, Xu Shan Sun3
1Department of Medical Oncology, Institut de Cancérologie de Lorraine, Vandoeuvre-lès-Nancy, France.

Introduction:
Patients with cervical lymphadenopathy of unknown primary carcinoma (CUP) usually undergo neck dissection and irradiation. There is an ongoing controversy regarding the extent of nodal and mucosal volumes to be irradiated. We assessed outcomes after bilateral or unilateral nodal irradiation.
Methods:
This retrospective multicentre study included patients with CUP and squamous cellular carcinoma who underwent radiotherapy (RT) between 2000 and 2015.
Results:
Of 350 patients, 74.5% had unilateral disease and 25.5% had bilateral disease. Of 297 patients with available data on disease and irradiation sides, 61 (20.5%) patients had unilateral disease and unilateral irradiation, 155 (52.2%), unilateral disease and bilateral irradiation and 81 (27.3%), bilateral disease and bilateral irradiation. Thirty-four (9.7%) and 217 (62.0%) patients received neoadjuvant and/or concomitant chemotherapy, respectively. Median follow-up was 37 months. Three-year local, regional, locoregional failure rates and CUP-specific survival were 5.6%, 11.7%, 15.0% and 84.7%, respectively. In patients with unilateral disease, the 3-year cumulative incidence of regional/local relapse was 7.7%/4.3% after bilateral irradiation versus 16.9%/11.1% after unilateral irradiation (hazard ratio = 0.56/0.61, p = 0.17/0.32). The cumulative incidence of CUP-specific deaths was 9.2% after bilateral irradiation and 15.5% after unilateral irradiation (p = 0.92). In multivariate analysis, mucosal irradiation was associated with better local control, whereas no neck dissection, ≥N2b and interruption of RT for more than 4 days were associated with poorer regional control. Toxicity was higher after bilateral irradiation (p < 0.05). No positron-emission tomography-computed tomography, largest node diameter, ≥N2b, neoadjuvant chemotherapy and interruption of RT were associated with poorer cause-specific survival.
Conclusion:
Bilateral nodal irradiation yielded non-significant better nodal and mucosal control rates but was associated with higher rates of severe toxicity.
More Related Videos

Related Concept Videos
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:21
Testing a Claim about Mean: Unknown Population SD
Estimating a population mean requires the samples to be approximately normally distributed. The data should be collected from the randomly selected samples having no sampling bias. There is no specific requirement for sample size. But if the sample size is less than 30, and we don't know the population standard deviation, a different approach is used;...
 01:22
Estimating Population Mean with Unknown Standard Deviation
William S. Gosset (1876–1937) of the...
 01:14
Node Analysis for AC Circuits
To unravel the complexities of this system, nodal analysis is employed, a powerful technique founded on Kirchhoff's current law (KCL), which remains valid for phasors. AC circuits can effectively be...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular...
 01:20
Fluid Connective Tissues: Blood and Lymph
Blood
The blood flows through blood vessels— arteries, capillaries, and veins. Blood plasma is primarily made of proteins, solutes, and...