Related Experiment Video
Updated: Jan 27, 2026
Quantitative Mapping of Specific Ventilation in the Human Lung using Proton Magnetic Resonance Imaging and Oxygen as a Contrast Agent
Published on: June 5, 2019
High inspired oxygen fraction impairs lung volume and ventilation heterogeneity in healthy children: a double-blind
Béatrice de la Grandville1, Ferenc Petak2, Gergely Albu3
1Department of Anaesthesiology, Fribourg Hospital, Fribourg, Switzerland; Department of Anaesthesiology, Pharmacology and Intensive Care, University Hospitals of Geneva, Geneva, Switzerland; Faculty of Medicine, University of Geneva, Geneva, Switzerland.

Insights
High inspired oxygen fraction (FiO2>0.8) in anaesthetised children reduces postoperative lung volume and increases ventilation inhomogeneity. Avoid high FiO2 in paediatric anaesthesia to protect lung function.
Area of Science:
- Anaesthesiology
- Pediatric Pulmonology
- Critical Care Medicine
Background:
- High inspired oxygen fraction (FiO2) is common in pediatric anesthesia, but its effect on postoperative lung function is not well understood.
- This study investigated the impact of different intraoperative FiO2 levels on lung mechanics and gas exchange in children.
Purpose of the Study:
- To compare lung volume, ventilation heterogeneity, and respiratory mechanics in anesthetized children receiving low versus high FiO2 intraoperatively.
- To determine the optimal FiO2 strategy to preserve postoperative lung function in pediatric patients.
Main Methods:
- A double-blind randomized controlled trial involving children undergoing elective surgery.
- Patients were assigned to receive FiO2 100% or 80% during induction/emergence, with maintenance FiO2 of 80% or 35% respectively.
- Functional residual capacity (FRC), lung clearance index (ventilation inhomogeneity), airway resistance, and respiratory elastance were measured using multiple-breath nitrogen washout and forced oscillations.
Main Results:
- Fifty-eight children were randomized. FRC decreased significantly in the FiO2>0.8 group immediately post-recovery (-12.0%).
- Ventilation inhomogeneity increased in both groups post-recovery, but persisted longer in the FiO2>0.8 group (6.1% at 24 hours).
- No significant differences in airway resistance or respiratory elastance were observed between groups.
Conclusions:
- Intraoperative FiO2>0.8 in anesthetized children leads to decreased lung volume and persistent ventilation inhomogeneity in the early postoperative period.
- These findings suggest that high FiO2 should be used cautiously and potentially avoided in anesthetized children with healthy lungs.
Background:
Although a high inspired oxygen fraction (FiO2) is commonly used in paediatric anaesthesia, the impact on postoperative lung function is unclear. We compared lung volume, ventilation heterogeneity, and respiratory mechanics in anaesthetised children randomised to receive low or high FiO2 intraoperatively.
Methods:
In a double-blind randomised controlled trial, children scheduled for elective surgery were randomly assigned FiO2 100% (n=29) or FiO2 80% (n=29) during anaesthesia induction and emergence. During maintenance of anaesthesia, participants assigned FiO2=100% at induction/emergence received FiO2=80% (FiO2>0.8 group); those randomised to FiO2=80% at induction/emergence received FiO2=35% intraoperatively (FiO2 [0.8→0.35 group]). During spontaneous breathing, we measured the (i) functional residual capacity (FRC) and lung clearance index (ventilation inhomogeneity) by multiple-breath nitrogen washout; and (ii) airway resistance and respiratory tissue elastance by forced oscillations, before operation, after discharge from the recovery room, and 24 h after operation. Mean (95% confidence intervals) are reported.
Results:
Fifty eight children (12.9 [12.3-13.5] yr) were randomised; 22/29 (high group) and 21/29 (low group) children completed serial multiple-breath nitrogen washout measurements. FRC decreased in the FiO2>0.8 group after discharge from recovery (-12.0 [-18.5 to -5.5]%; P=0.01), but normalised 24 h later. Ventilation inhomogeneity increased in both groups after discharge from recovery, but persisted in the FiO2>0.8 group 24 h after surgery (6.1 [2.5-9.8%]%; P=0.02). Airway resistance and respiratory elastance did not differ between the groups at any time point.
Conclusions:
FiO2>0.8 decreases lung volume in the immediate postoperative period, accompanied by persistent ventilation inhomogeneity. These data suggest that FiO2>0.8 should be avoided in anaesthetised children with normal lungs.
Clinical Trial Registration:
NCT02384616.

Related Concept Videos
 02:07
Blind Procedures
 01:16
Control Volume and System Representations
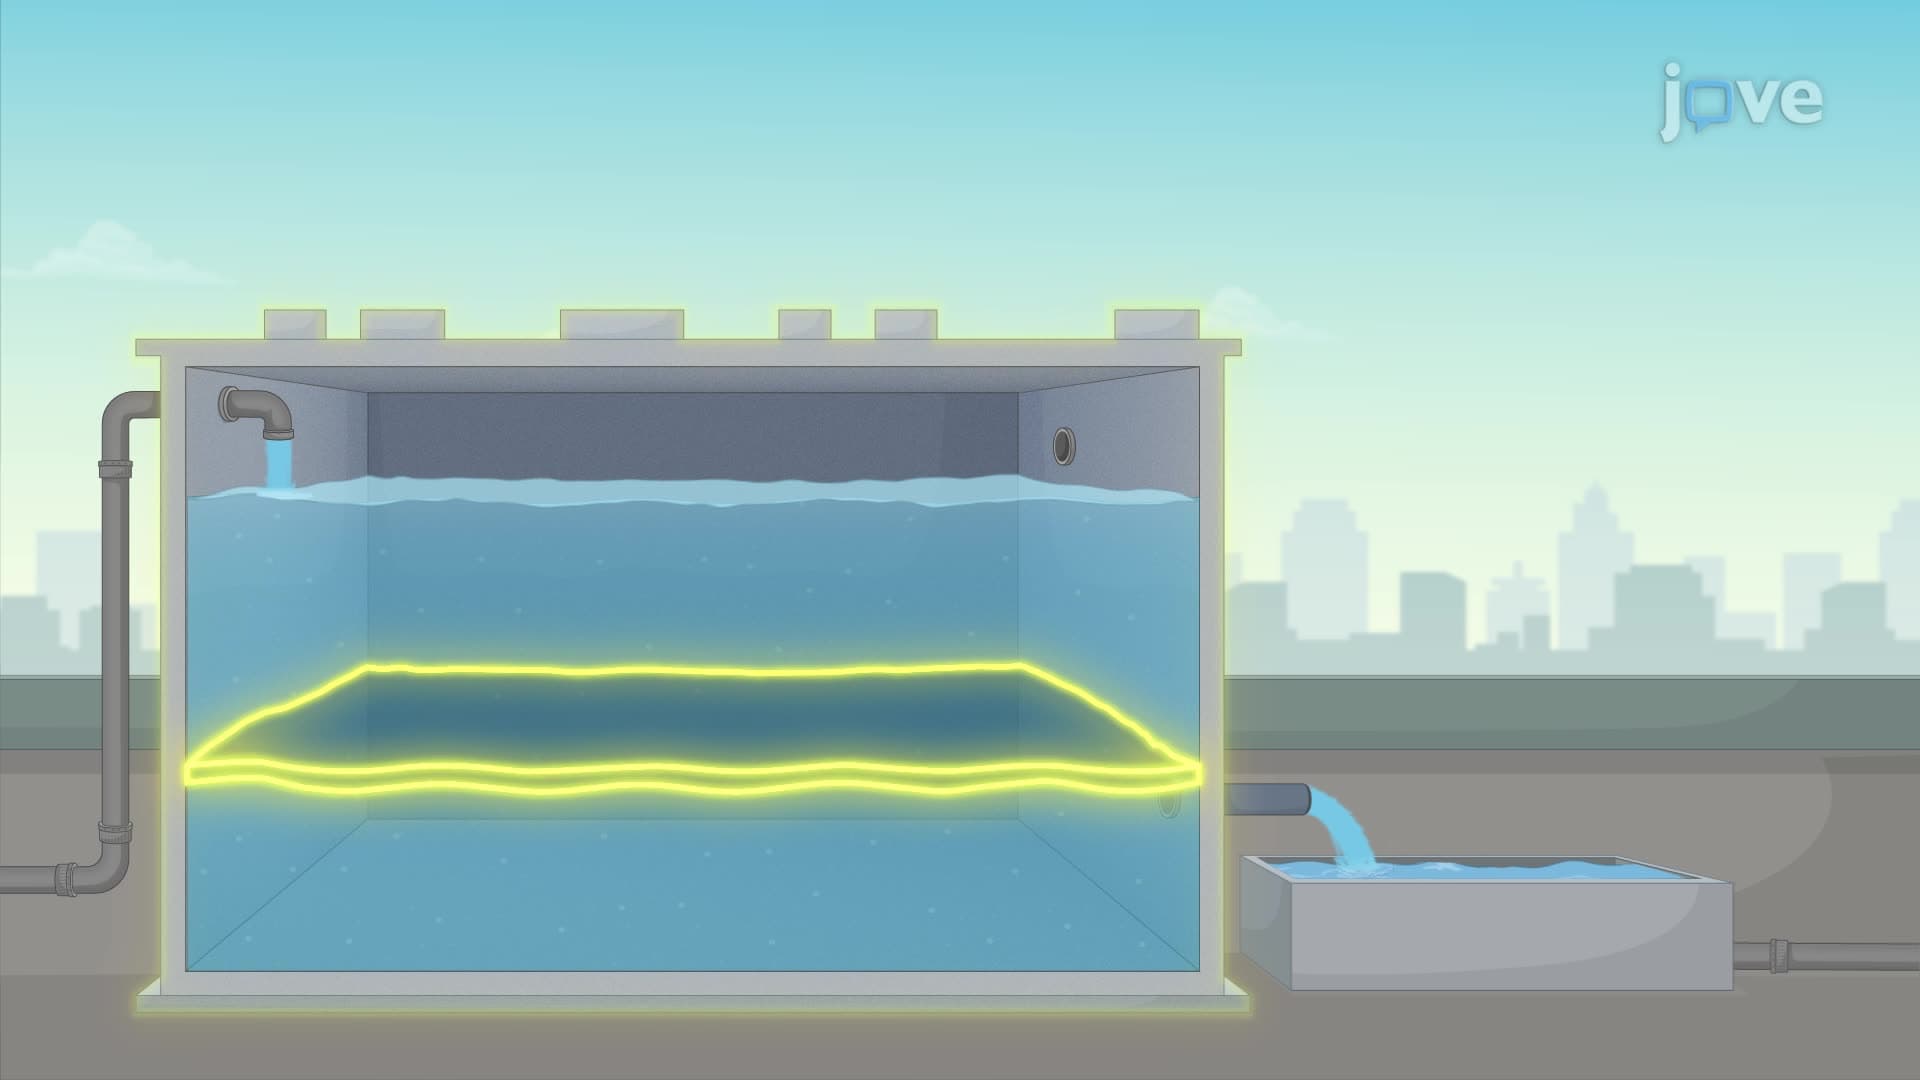
The control volume approach considers a stationary region in space through which fluid flows. This region is bounded by a control surface. For instance, in the case of water...
 01:13
Linear Momentum in Control Volume
 01:14
Conservation of Energy in Control Volume
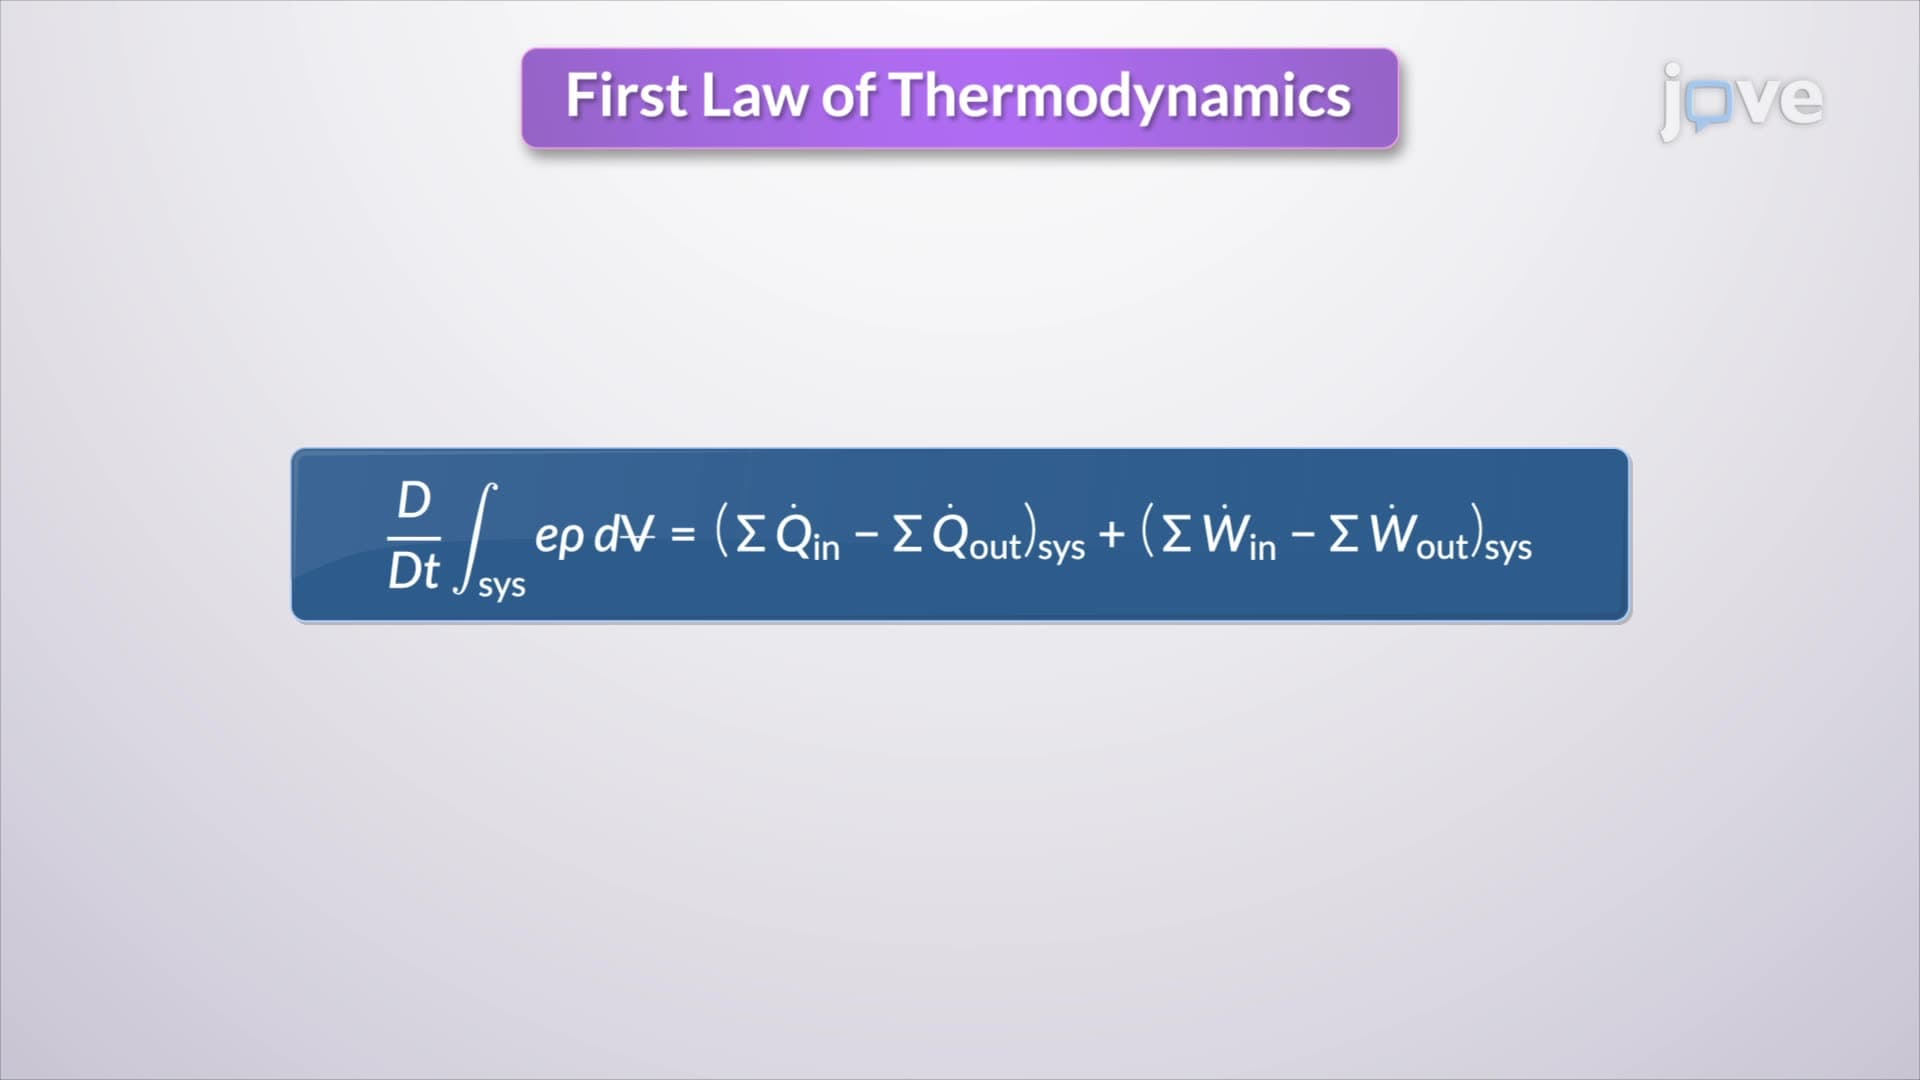
For steady flow systems, the time derivative of the stored energy becomes zero since there is no energy accumulation within the control volume. This simplifies the energy equation to:
 01:11
Blinding
 01:07
Conservation of Mass in Fixed, Nondeforming Control Volume
In the case of a sewer pipe, which can be modeled...