Related Experiment Video
Updated: Jan 21, 2026


Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
Additional Risk Stratification Using Local and Systemic Factors for Patients with Critical Limb Ischaemia Undergoing
Yosuke Hata1, Osamu Iida1, Shin Okamoto1
1Kansai Rosai Hospital Cardiovascular Centre, Inabaso, Amagasaki, Hyogo, Japan.

Insights
Systemic factors like non-ambulatory status, haemodialysis, and low albumin levels significantly impact wound healing in critical limb ischaemia (CLI) patients, especially those with advanced WIfI stage 4. Managing these factors can improve outcomes.
Area of Science:
- Vascular Surgery
- Wound Healing Research
- Critical Limb Ischaemia (CLI) Management
Background:
- Current guidelines emphasize limb characteristics for critical limb ischaemia (CLI) prognosis.
- Emerging evidence suggests systemic factors also influence CLI outcomes.
- This study investigates the role of systemic factors in wound healing for CLI patients undergoing endovascular therapy.
Purpose of the Study:
- To evaluate the impact of systemic factors on wound healing in CLI patients.
- To compare the influence of systemic factors versus limb characteristics (Wound, Ischaemia, and foot Infection [WIfI] classification) on healing.
- To identify specific systemic risk factors for impaired wound healing in CLI.
Main Methods:
- Retrospective analysis of 735 CLI patients with tissue loss from a prospective registry (April 2010 - December 2015).
- Utilized the Wound, Ischaemia, and foot Infection (WIfI) classification system.
- Employed Cox proportional hazards regression to identify predictors of wound healing.
Main Results:
- One-year wound healing rates were 60.2% for WIfI stage 1-3 and 53.6% for WIfI stage 4.
- In WIfI stage 4, non-ambulatory status, haemodialysis, and albumin <3.0 g/dL were independent risk factors for healing failure.
- Wound healing in WIfI stage 4 patients with zero or one risk factor was similar to WIfI stage 1-3 patients (67.7% vs. 63.6%).
Conclusions:
- Non-ambulatory status, haemodialysis, and low albumin are significant systemic risk factors for poor wound healing in advanced CLI (WIfI stage 4).
- CLI patients in WIfI stage 4 with minimal systemic risk factors exhibit wound healing comparable to less severe stages.
- These findings highlight the importance of addressing systemic health in CLI wound management.
Objectives:
While current guidelines describe the importance of assessing limb characteristics for predicting limb prognosis in patients with critical limb ischaemia (CLI), several reports have also suggested that systemic factors are associated with limb prognosis. The aim of this study was to evaluate whether systemic factors have the same impact on wound healing as limb characteristics in CLI patients undergoing endovascular therapy.
Methods:
A total of 735 patients who were treated for the first time for CLI with tissue loss between April 2010 and December 2015 were extracted from a prospective registry and data for the Wound, Ischaemia, and foot Infection (WIfI) classification were searched retrospectively. The predictors of wound healing were explored with Cox proportional hazards regression.
Results:
The one year wound healing rate was 60.2% in WIfI stage 1-3 patients and 53.6% in WIfI stage 4 (p = .01). In WIfI stage 1-3, no systemic factors were significantly associated with wound healing, whereas, in WIfI stage 4 patients, non-ambulatory status [hazard ratio (HR) 1.98; 95% confidence interval (CI) 1.37-2.84], haemodialysis (HR 1.90; 95% CI 1.33-2.72) and an albumin level under 3.0 g/dL (HR 1.53; 95% CI 1.02-2.31), were identified as independent risk factors for failure to achieve wound healing. If none or one of these risk factors were present, wound healing was comparable with WIfI 4 and WIfI 1-3 patients (67.7% vs. 63.6%, p = .89), whereas in patients with two or more risk factors wound healing was worse in WIfI 4 than in WIfI 1-3 patients (35.7% vs. 49.5%, p = .01).
Conclusion:
Non-ambulatory status, haemodialysis, and a low albumin level were additional systemic risk factors for impaired wound healing in patients with WIfI stage 4. The wound healing rate in WIfI stage 4 patients with one or fewer of these risk factors was comparable to that in WIfI stage 1-3.

Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:27
Conjugate Addition (1,4-Addition) vs Direct Addition (1,2-Addition)
Conjugate addition results in a thermodynamically stable product. The reaction retains the stronger C=O bond at the expense of the weaker C=C π bond. The process is slow as the β carbon is less electrophilic than the carbonyl carbon.
Direct addition products are...
 01:16
Critical Region, Critical Values and Significance Level
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...
 02:10
Additional Subnuclear Structures
The nucleus contains many membrane-less subnuclear organelles or nuclear bodies, such as nucleoli, Cajal bodies, speckles,...
 01:08
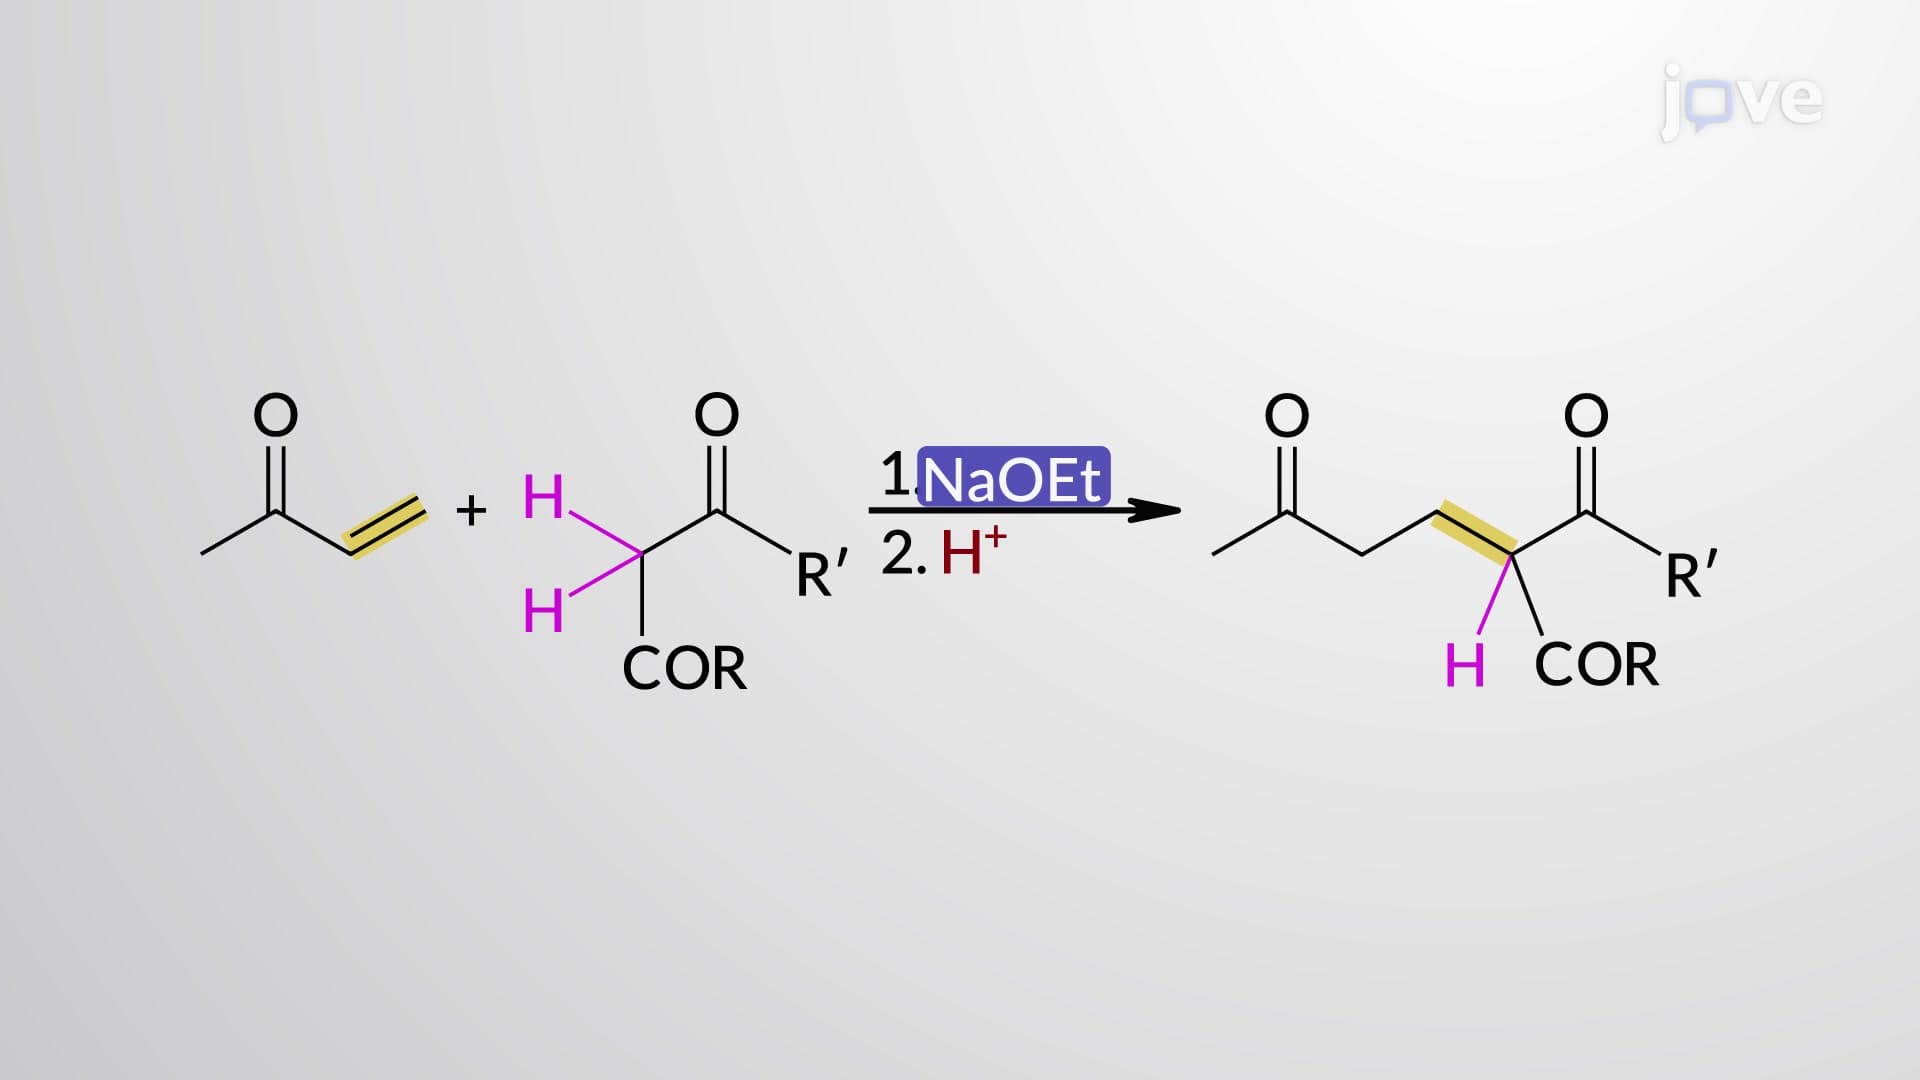
Conjugate Addition of Enolates: Michael Addition