Related Experiment Video
Updated: Jan 20, 2026


Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
[Risk factor analysis on anastomotic leakage after laparoscopic surgery in rectal cancer patient with neoadjuvant

Abstract:
Objective: To investigate the risk factors of anastomotic leakage (AL) after laparoscopic surgery in rectal cancer patient with neoadjuvant therapy and construct a nomogram prediction model. Methods: This study was a retrospective case-control study that collected and reviewed the clinicopathological data of 359 patients who underwent laparoscopic surgery from January 2012 to January 2018, including 202 patients from the Department of General Surgery, Nanfang Hospital of Southern Medical University and 157 patients from the Department of Gastrointestinal Surgery of Fujian Provincial Cancer Hospital. Inclusion criteria: (1) age ≥ 18 years old; (2) diagnosis as rectal cancer by biopsy before treatment; (3) distance from tumor to anus within 12 cm; (4) locally advanced stage (T3-T4 or N+) diagnosed by imaging (CT, MRI, PET or ultrasound); (5) standardized neoadjuvant therapy followed by laparoscopic radical operation. Exclusion criteria: (1) previous history of colorectal cancer surgery; (2) short-term or incomplete standardized neoadjuvant therapy; (3) Miles, Hartmann, emergency surgery, palliative resection; (4) conversion to open surgery. Clinicopathological data, including age, gender, body mass index (BMI), preoperative albumin, distance from tumor to anus, operation hospital, American Society of Anesthesiologists score (ASA score), operation time, T stage, N stage, M stage, TNM stage, pathological complete response (pCR) were analyzed with univariate analysis to identify predictors for AL after laparoscopic surgery in rectal cancer patient with neoadjuvant therapy. Then, incorporated predictors of AL, which were screened by multivariate logistic regression, were plotted by the "rms" package in R software to establish a nomogram model. According to the scale of the nomogram of each risk factor, the total score could be obtained by adding each single score, then the corresponding probability of postoperative AL could be acquired. The area under ROC curve (AUC) was used to evaluate the predictive ability of each risk factor and nomogram on model. AUC > 0.75 indicated that the model had good predictive ability. The Bootstrap method (1000 bootstrapping resamples) was applied as internal verification to show the robustness of the model. The discrimination of the nomogram was determined by calculating the average consistency index (C-index) whose rage was 0.5 to 1.0. Higher C-index indicated better consistency with actual risk. The calibration curve was used to assess the calibration of prediction model. The Hosmer-Lemeshow test yielding a non-significant statistic (P>0.05) suggested no departure from the perfect fit. Results: Of 359 cases, 224 were male, 135 were female, 189 were ≥ 55 years old, 98 had a BMI > 24 kg/m(2), 176 had preoperative albumin ≤ 40 g/L, 128 had distance from tumor to anus ≤ 5 cm, 257 were TNM 0-II stage, 102 were TNM III-IV stage, and 84 achieved pCR after neoadjuvant therapy. The incidence of postoperative AL was 9.5% (34/359). Univariate analysis showed that gender, preoperative albumin and distance from tumor to the anus were associated with postoperative AL (All P<0.05). Multivariate logistic regression analysis revealed that male (OR=2.480, 95% CI: 1.012-6.077, P=0.047), preoperative albumin ≤40 g/L (OR=5.319, 95% CI: 2.106-13.433, P<0.001) and distance from tumor to anus ≤ 5 cm (OR=4.339, 95% CI: 1.990-9.458, P<0.001) were significant independent risk factors for postoperative AL. According to these results, a nomogram prediction model was constructed. The male was for 55 points, the preoperative albumin ≤ 40 g/L was for 100 points, and the distance from tumor to the anus ≤ 5 cm was for 88 points. Adding all the points of each risk factor, the corresponding probability of total score would indicated the morbidity of postoperative AL predicted by this nomogram modal. The AUC of the nomogram was 0.792 (95% CI: 0.729-0.856), and the C-index was 0.792 after internal verification. The calibration curve showed that the predictive results were well correlated with the actual results (P=0.562). Conclusions: Male, preoperative albumin ≤ 40 g/L and distance from tumor to the anus ≤ 5 cm are independent risk factors for AL after laparoscopic surgery in rectal cancer patient with neoadjuvant therapy. The nomogram prediction model is helpful to predict the probability of AL after surgery.


Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 01:26
Modeling in Therapy
Participant Modeling
Participant modeling involves therapists demonstrating calm and effective behaviors in...
 01:27
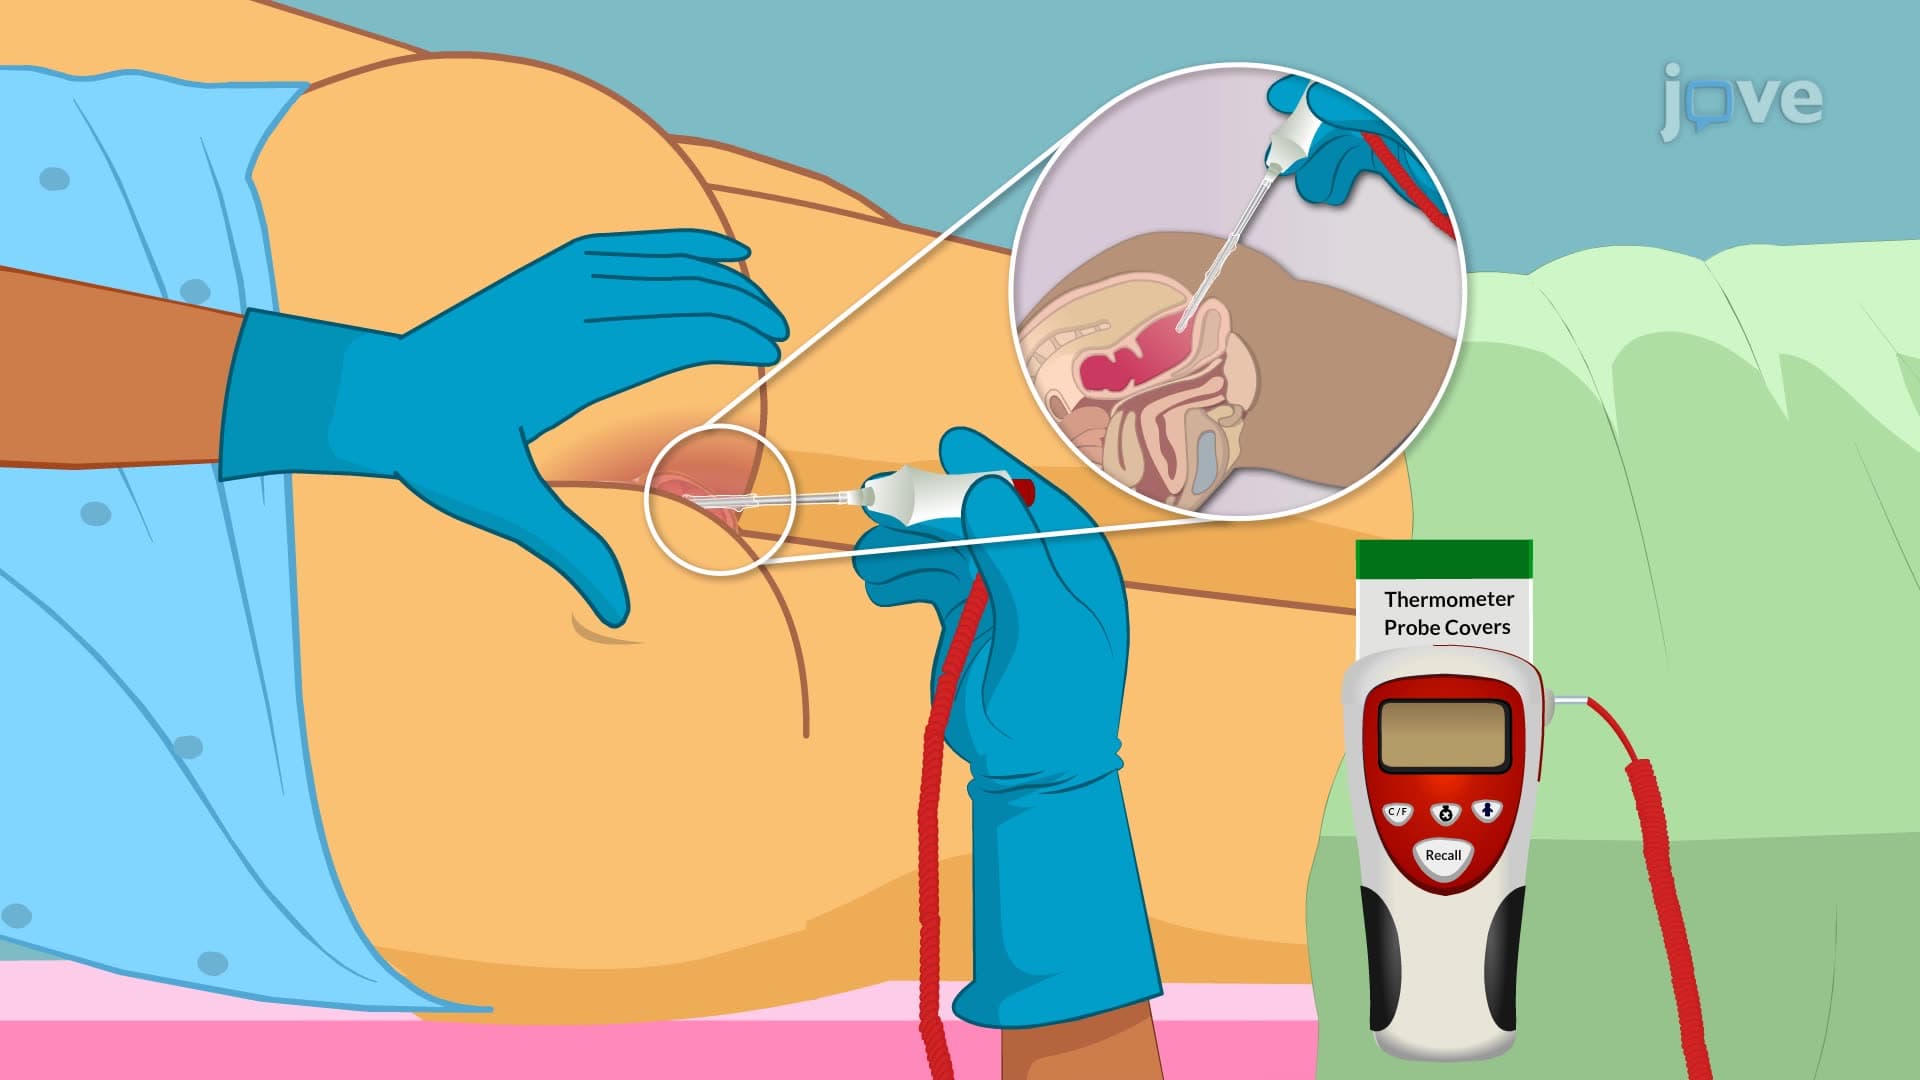
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...