Related Experiment Video
Updated: Jan 4, 2026

Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Robotic-assisted breast-axillo insufflation thyroidectomy (RABIT): a retrospective case series of thyroid carcinoma
Sandeep P Nayak1, Abhilasha Sadhoo2, Bharath Gangadhara2
1Department of Surgical Oncology, Fortis Hospitals, 154, 9, Bannerghatta Main Rd, Opposite IIM, Sahyadri Layout, Panduranga Nagar, Bangalore, Karnataka, 560076, India. nayak.dr@gmail.com.

Objective:
To evaluate the feasibility and safety of robotic-assisted breast-axillo insufflation thyroidectomy (RABIT) for differentiated thyroid cancer.
Methods:
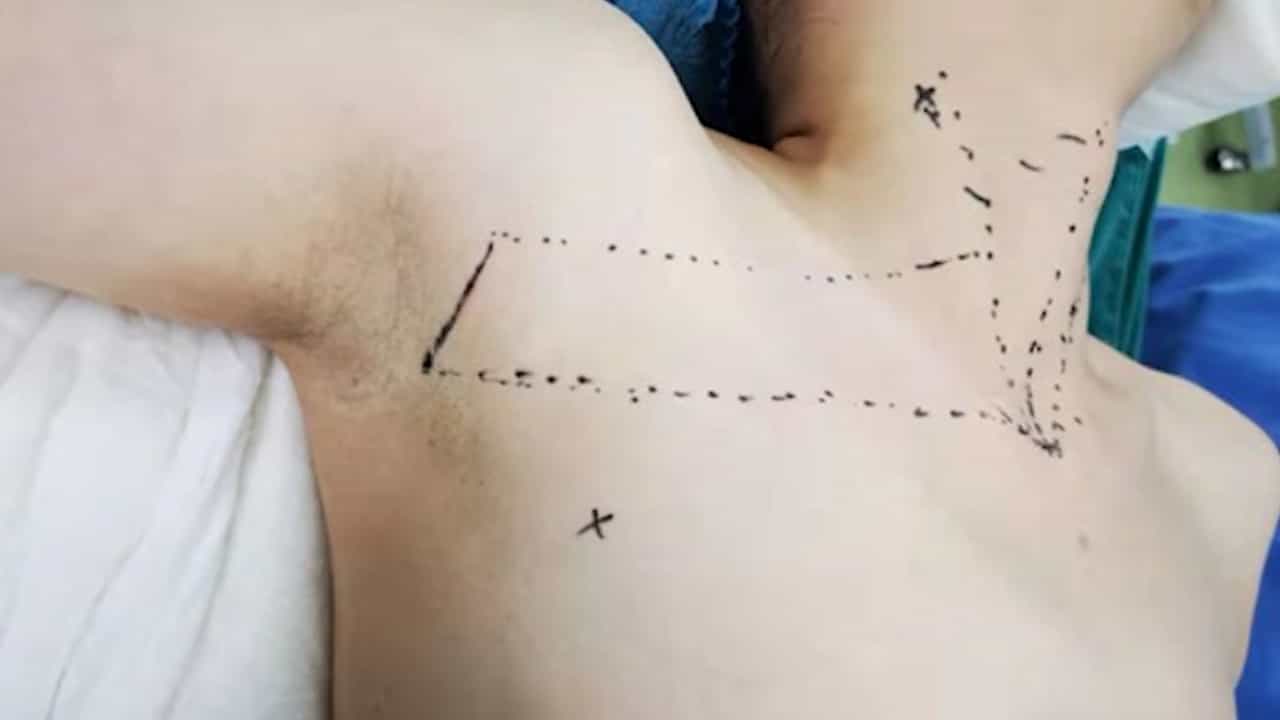
In this retrospective case series, patients with differentiated thyroid carcinoma were enrolled in our hospital from January 2018 to December 2018. All patients underwent indirect laryngoscopy to assess the status of vocal cord preoperatively. RABIT was performed with five separate breast-axillo incisions. All the procedures were performed using da Vinci Xi Robotic Surgical System, a single docking method using CO2 insufflation.
Results:
Twelve patients completed RABIT, in which one case needed conversion to open thyroidectomy. The mean age was 30.25 ± 7 with male to female ratio being 1:1. Preoperative diagnosis showed papillary carcinoma (n = 9) and follicular neoplasm (n = 3). The mean operative time for RABIT was 140 ± 50.45 min and average blood loss during surgery was 22.92 ± 9 mL. Mean hospital stay was 4.42 ± 1.08 days. Final pathology confirmed classical papillary thyroid carcinoma (n = 10; 83.3%) and follicular variant of papillary carcinoma (n = 2; 16.7%). None of the cases reported injury or paralysis to the recurrent laryngeal nerves.
Conclusion:
RABIT is a safe and feasible approach for thyroidectomy. It has several advantages in that it provides similar symmetrical view to conventional open surgery and enables to maintain specimen integrity and use of assistant port permits better handling of the gland. Additionally, the largest operating angles with this technique prevent collision between the robotic arms and provide excellent cosmetic satisfaction due to very small, five separate breast-axillo incisions.