Related Experiment Video
Updated: Jan 4, 2026
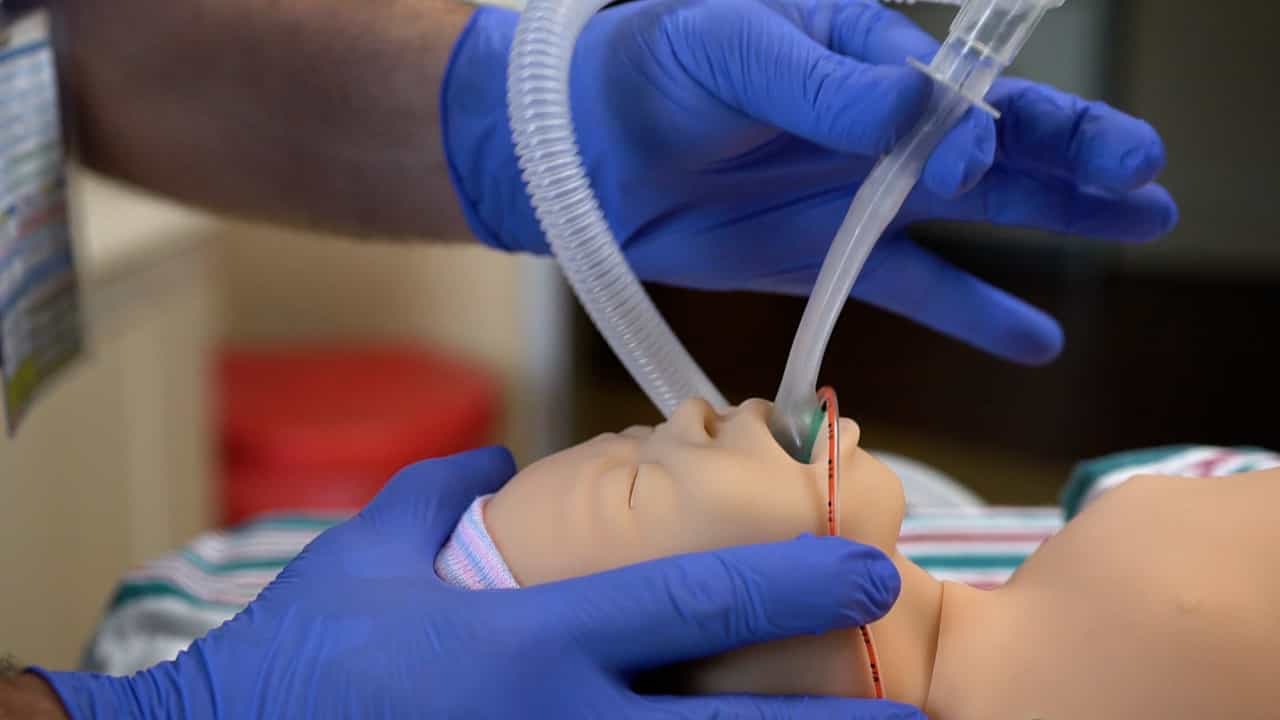

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
A comparison of airway interventions and gastrostomy tube placement in infants with Robin sequence
K El Ghoul1, C E Calabrese2, M J Koudstaal3
1Erasmus University Medical Center, Rotterdam, The Netherlands; Department of Plastic and Oral Surgery, Boston Children's Hospital, Boston, MA, USA; Department of Oral and Maxillofacial Surgery, Erasmus Medical Center, Rotterdam, The Netherlands.

Insights
Infants with Robin sequence needing airway surgery face higher G-tube feeding needs. Mandibular distraction osteogenesis shows lower G-tube rates than other airway operations.
Area of Science:
- Pediatric surgery
- Craniofacial anomalies
- Gastroenterology
Background:
- Robin sequence (RS) presents significant airway obstruction challenges in infants.
- Feeding impairment is a common complication, often necessitating gastrostomy tube (G-tube) placement.
- Understanding factors influencing G-tube rates is crucial for optimizing infant care.
Purpose of the Study:
- To evaluate feeding impairment in infants with Robin sequence based on G-tube placement rates.
- To compare G-tube placement rates between non-operative and various operative airway management strategies.
- To identify patient-specific factors associated with increased G-tube dependency.
Main Methods:
- Retrospective study of 225 infants with Robin sequence treated between 1976 and 2018.
- Patients were grouped by airway intervention: non-operative, tongue-lip adhesion (TLA), mandibular distraction osteogenesis (MDO), or tracheostomy.
- Statistical analysis compared G-tube placement rates across groups and by patient characteristics (syndromic diagnosis, GI anomalies).
Main Results:
- Operative management (58.1%) had a significantly higher G-tube rate than non-operative management (28.3%).
- Tongue-lip adhesion and tracheostomy groups showed higher odds of G-tube placement compared to MDO.
- Syndromic infants and those with gastrointestinal anomalies had increased odds of G-tube placement.
Conclusions:
- Infants with Robin sequence requiring airway operations, syndromic diagnoses, or gastrointestinal anomalies are more likely to need G-tube placement.
- Mandibular distraction osteogenesis was associated with the lowest G-tube rate among operative interventions.
- Tailored management strategies considering these factors can improve outcomes for infants with Robin sequence.
Abstract:
The purpose of this study was to evaluate feeding impairment following non-operative or operative management of airway obstruction in a large series of infants with Robin sequence (RS) by rate of G-tube placement. A retrospective study was conducted at Boston Children's Hospital including 225 patients (47.1% female) with RS treated between 1976 and 2018. Subjects were grouped by intervention required for successful management of airway obstruction: non-operative only (n = 120), tongue-lip adhesion (TLA, n = 75), mandibular distraction osteogenesis (MDO, n = 21), or tracheostomy (n = 9). The operative group had a higher rate of G-tube placement (58.1%) than the non-operative group (28.3%, P < 0.0001). Subjects in the TLA and tracheostomy groups had higher odds of G-tube placement than subjects in the MDO group: odds ratio (OR) 5.5 (95% confidence interval (CI) 1.8-17.3, P = 0.004) and OR 27.0 (95% CI 3.2-293.4, P = 0.007), respectively. Syndromic patients and those with gastrointestinal anomalies also had higher odds of G-tube placement: OR 3.5 (95% CI 1.7-7.2, P = 0.001) and OR 5.9 (95% CI 1.6-21.0, P = 0.007), respectively. Infants with RS who require an airway operation and those with a syndromic diagnosis or gastrointestinal anomalies are more likely to require placement of a G-tube. Of the operative groups, MDO was associated with the lowest G-tube rate, compared to TLA and tracheostomy.


Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...