Related Experiment Video
Updated: Dec 28, 2025


Establishment of an Extracellular Acidic pH Culture System
Published on: November 19, 2017
Sodium Fate after Sodium Bicarbonate Infusion: Influence of Altered Acid-Base Status
Horacio J Adrogué1,2, Ahmed A Awan1,2, Nicolaos E Madias3,4
1Department of Medicine, Baylor College of Medicine, Houston, Texas, USA.

Background:
We have previously investigated the fate of administered bicarbonate infused as a hypertonic solution in animals with each of the 4 chronic acid-base disorders. Those studies did not address the fate of sodium, the coadministered cation.
Methods:
We examined baseline total body water (TBW), Na+ space, HCO3- space, and urinary sodium and bicarbonate excretion after acute hypertonic NaHCO3 infusion (1-N solution, 5 mmol/kg body weight) in dogs with each of the 4 chronic acid-base disorders. Observations were made at 30, 60, and 90 min postinfusion. Retained sodium that remains osmotically active distributes in an apparent space that approximates TBW. Na+ space that exceeds TBW uncovers nonosmotic sodium storage.
Results:
Na+ space approximated TBW at all times in normal and hyperbicarbonatemic animals (metabolic alkalosis and respiratory acidosis), but exceeded TBW by ~30% in hypobicarbonatemic animals (metabolic acidosis and respiratory alkalosis). Such osmotic inactivation was detected at 30 min and remained stable. The pooled data revealed that Na+ space corrected for TBW was independent of the initial blood pH but correlated with initial extracellular bicarbonate concentration (y = -0.01x + 1.4, p= 0.002). The fate of administered sodium and bicarbonate (internal distribution and urinary excretion) was closely linked.
Conclusions:
This study demonstrates that hypobicarbonatemic animals have a Na+ space that exceeds TBW after an acute infusion of hypertonic NaHCO3 indicating osmotic inactivation of a fraction of retained sodium. In addition to an expanded Na+ space, these animals have a larger HCO3- space compared with hyperbicarbonatemic animals. Both phenomena appear to reflect the wider range of titration of nonbicarbonate buffers (Δ pH) occurring during NaHCO3- loading whenever initial [HCO3-]e is low. The data indicate that the fate of administered bicarbonate drives the internal distribution and the external disposal of sodium, the co-administered cation, and is responsible for the early, but non-progressive, osmotic inactivation of a fraction of the retained sodium.
More Related Videos
 07:38
Functional Characterization of Na+/H+ Exchangers of Intracellular Compartments Using Proton-killing Selection to Express Them at the Plasma Membrane
Published on: March 30, 2015
 06:40
Combined Infusion and Stimulation with Fast-Scan Cyclic Voltammetry CIS-FSCV to Assess Ventral Tegmental Area Receptor Regulation of Phasic Dopamine
Published on: April 23, 2020
Related Concept Videos
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:29
Disorders of Acid-Base Balance
Respiratory Acidosis and Alkalosis
Respiratory acidosis occurs due to an increase in the partial pressure of carbon dioxide PCO2 in the blood. It often arises from shallow breathing or impaired gas exchange caused by...
 01:29
Renal Regulation of Acid-Base Balance
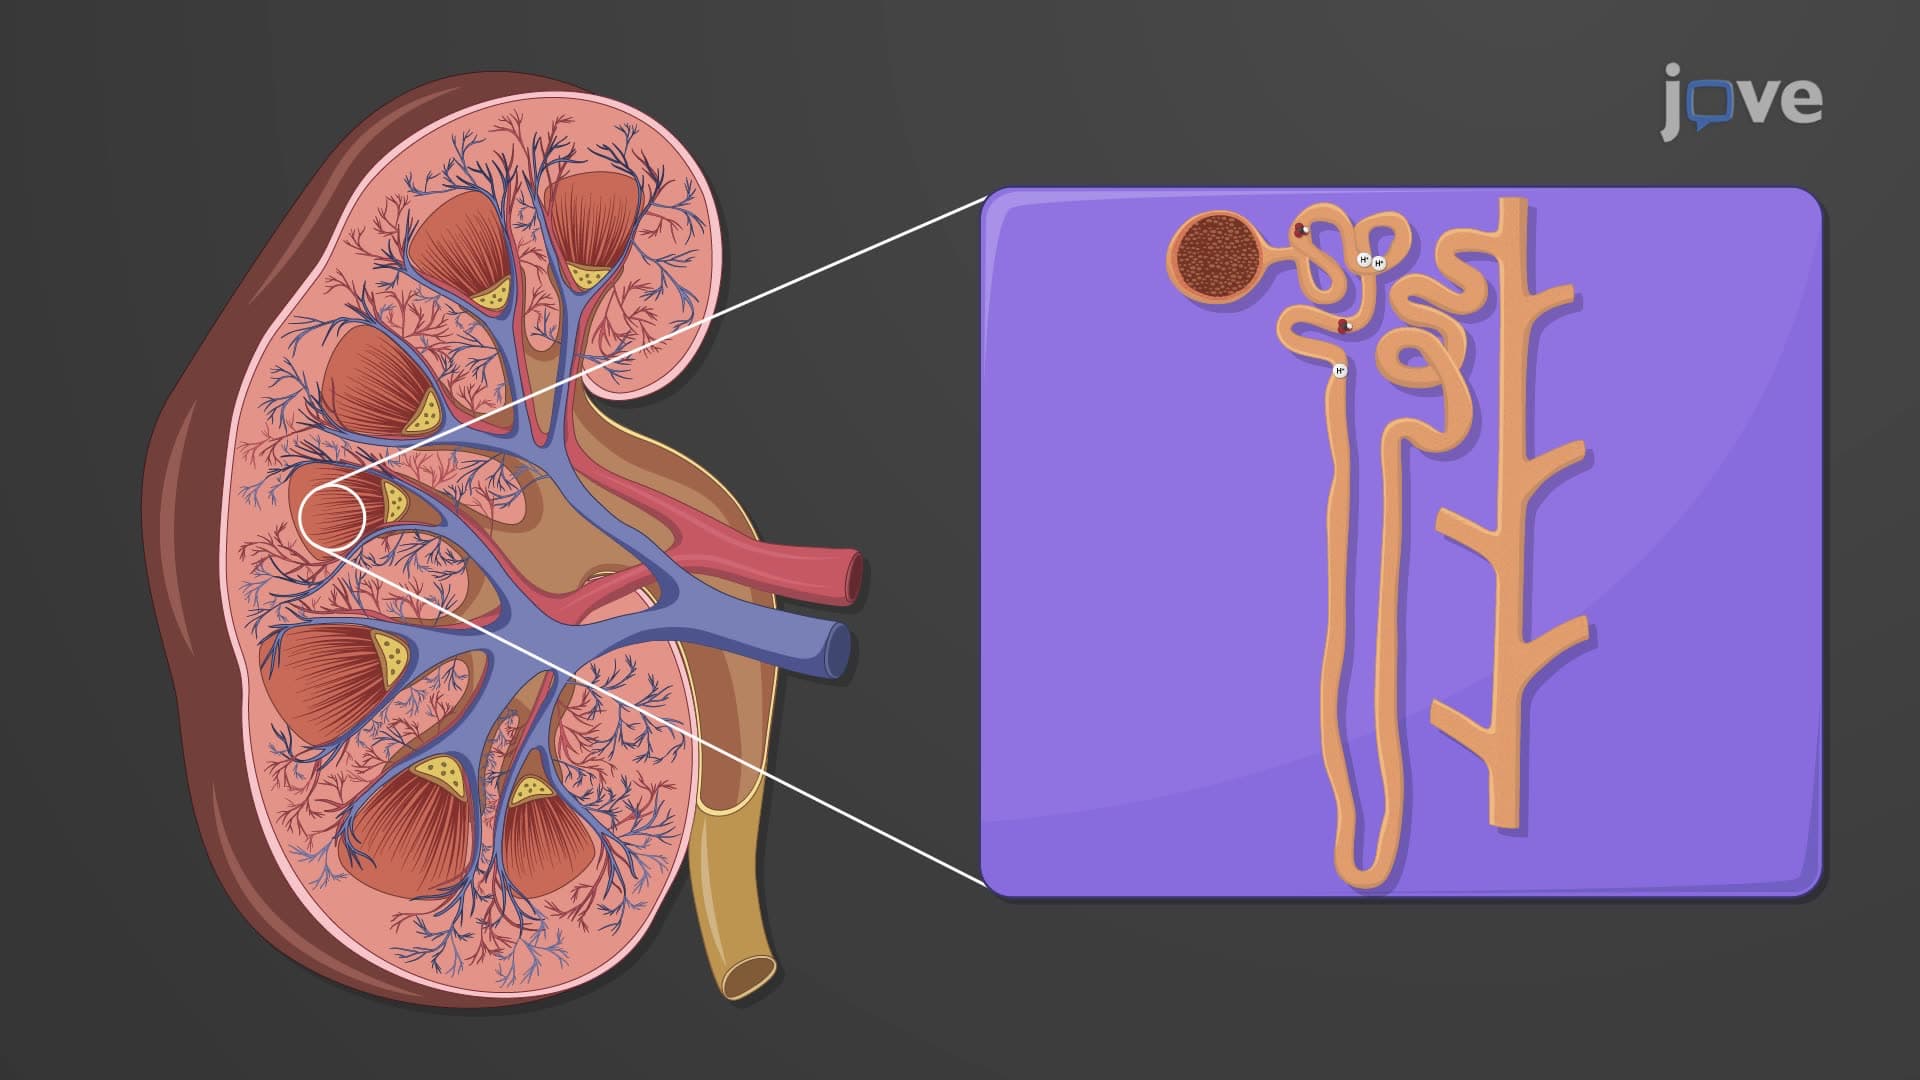
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:25
Acid-Base Balance
When the pH of arterial blood rises above 7.45, it results in a condition called alkalosis. Conversely, a drop below 7.35 leads to...
 01:18
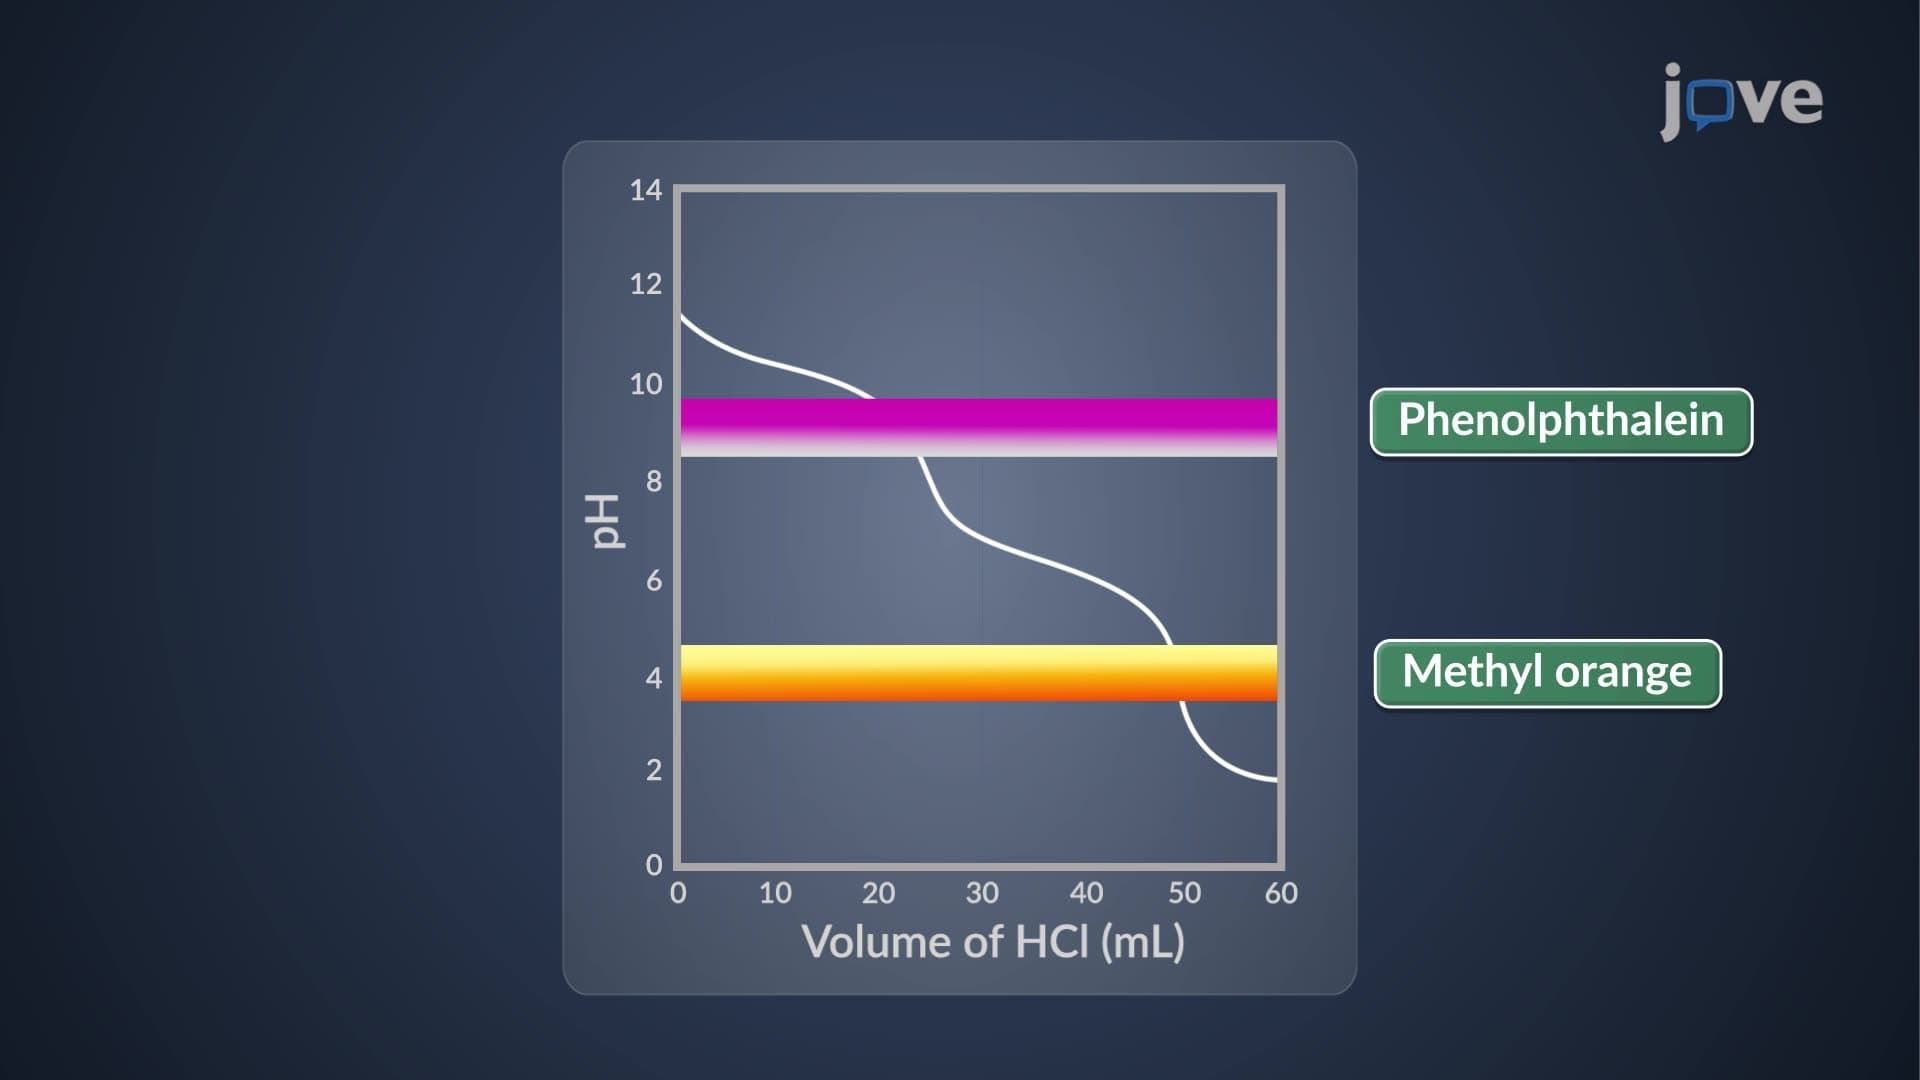
Titration of Polyprotic Base with a Strong Acid
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting,...