Related Experiment Video
Updated: Dec 18, 2025


Estimating Bilateral Atrial Function by Cardiovascular Magnetic Resonance Feature Tracking in Patients with Paroxysmal Atrial Fibrillation
Published on: July 20, 2022
Right atrial conduction time for predicting coexistent typical atrial flutter in patients with paroxysmal atrial
Satoshi Higuchi1, Koichiro Ejima1, Morio Shoda1
1Department of Cardiology, Tokyo Women's Medical University, Shinjuku-ku, Tokyo, Japan.

Introduction:
Screening of coexistent typical atrial flutter (AFL) in patients with atrial fibrillation (AF) is sometimes challenging. This study investigated whether a prolonged right atrial conduction time (RACT) estimated by tissue Doppler imaging (TDI) predicts patients with concomitant AFL and AF.
Methods And Results:
We retrospectively analyzed 398 patients (mean age: 61.6 years, 73.4% men) undergoing catheter ablation of paroxysmal AF. The patients were classified into two groups according to whether they had evidence of AFL (N = 122, 30.7%) determined by a clinical observation (N = 68), induction during procedures (N = 33), or AFL recurrence after procedures (N = 21) or not (N = 276, 69.3%). The preoperative RACT, defined as a longer duration between the onset of the P-wave and peak A'-wave on the right atrial lateral wall or septal wall, and total atrial conduction time (TACT), defined as the same time duration on the left atrial lateral wall, were evaluated in all patients. Patients with evidence of AFL had a significantly longer RACT than those without AFL (p < .001). A multiple logistic regression and receiver operator characteristics curve analysis revealed the ratio of the RACT and TACT (RACT/TACT) was the independent and most superior accurate cofounder for predicting evidence of AFL (area under the curve: 0.867). When adding a discriminator of an RACT/TACT ≧ 93% into the conventional screening, 98.4% of the patients with evidence of AFL were estimated to be treated during the initial procedures.
Conclusion:
The estimated RACT/TACT using the TDI may be useful for predicting patients with concomitant AFL in patients with AF.


Related Concept Videos
 01:29
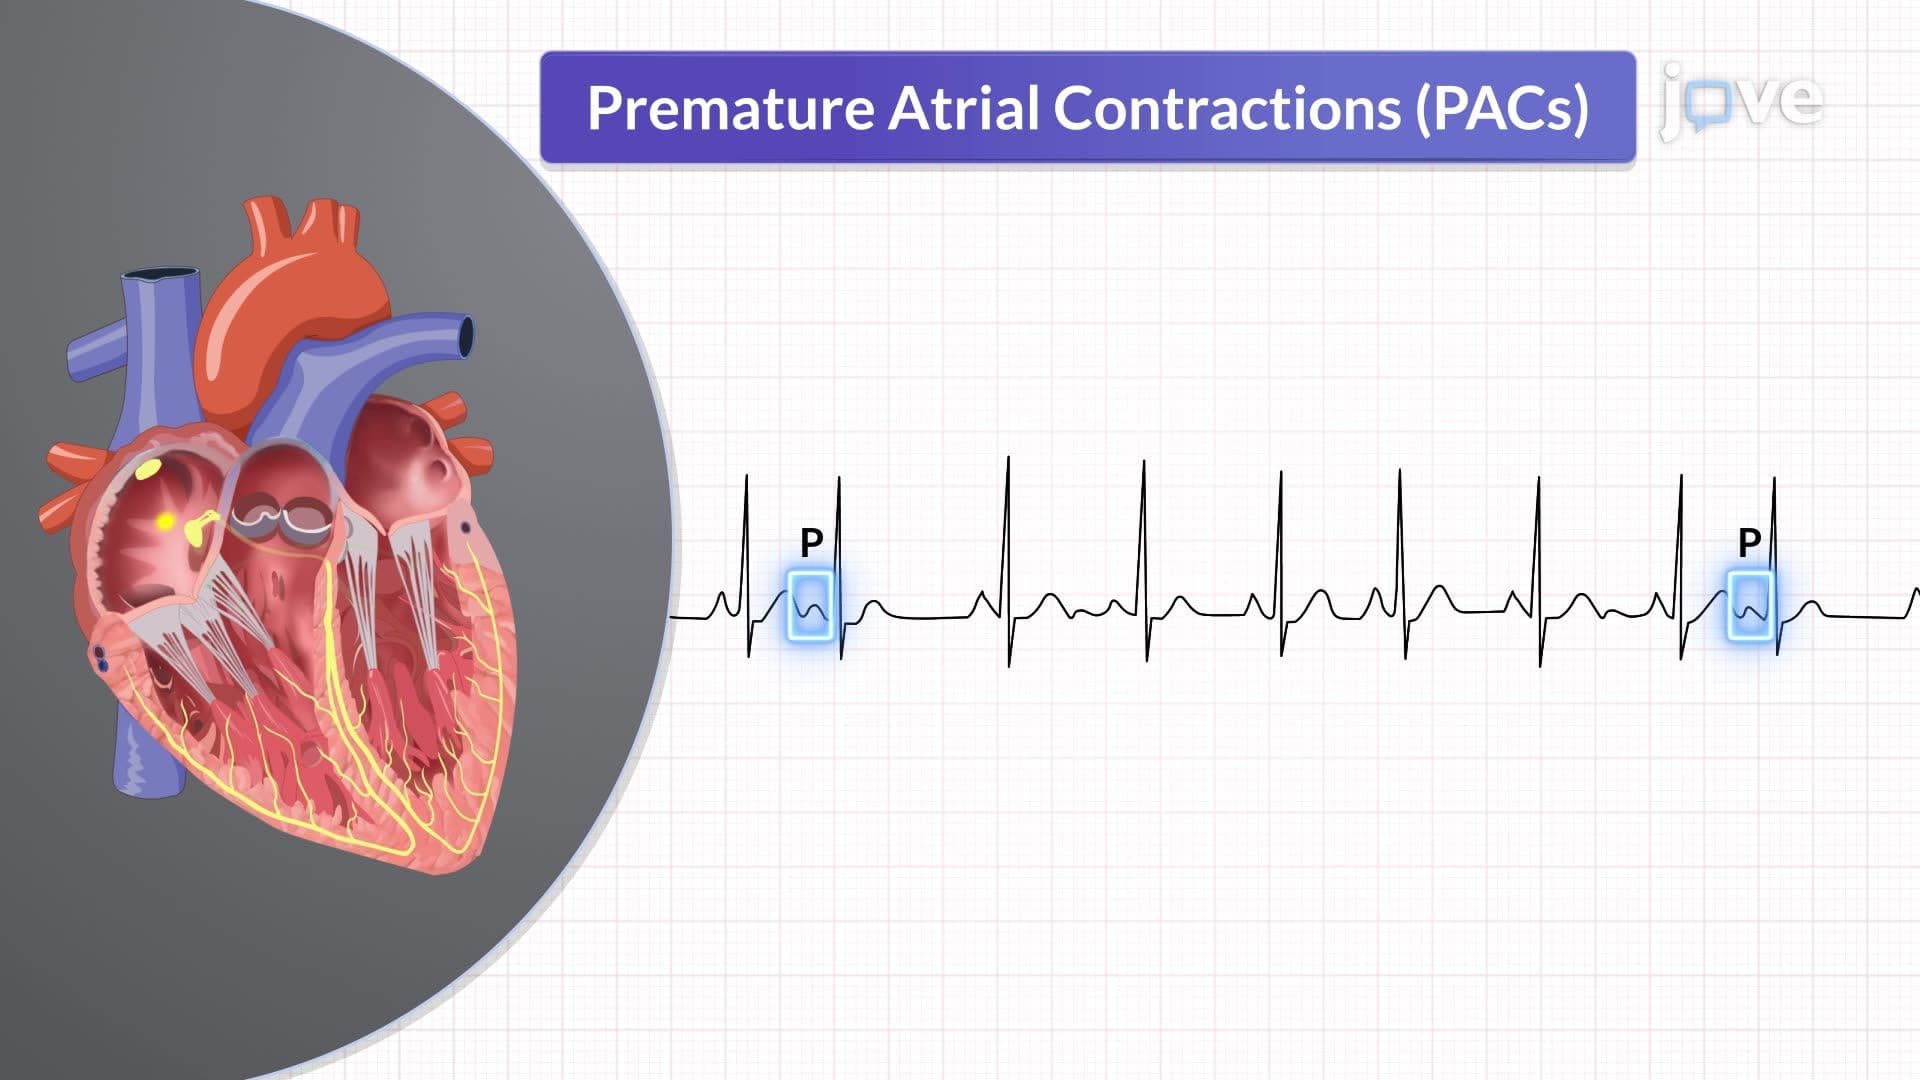
Dysrhythmias III: Characteristics of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...