CENTRAL POSTERIOR LENS CAPSULE USED INSTEAD OF AN INVERTED INTERNAL LIMITING MEMBRANE FLAP: A CLINIC-PATHOLOGICAL
Denise Vogt1, Sigrid Freissinger1, Ricarda G Schumann1
1Department of Ophthalmology, Ludwig-Maximilians-University, Munich, Germany ; and.

Purpose:
To present immunocytochemical characterization of a surgically excised central posterior lens capsule (PLC) that was transplanted to close a secondary refractory full-thickness macular hole (FTMH) as an epiretinal flap. For comparison, tissue of both an unaffected internal limiting membrane and unexposed PLC was processed.
Methods:
Clinical-pathological case report.
Results:
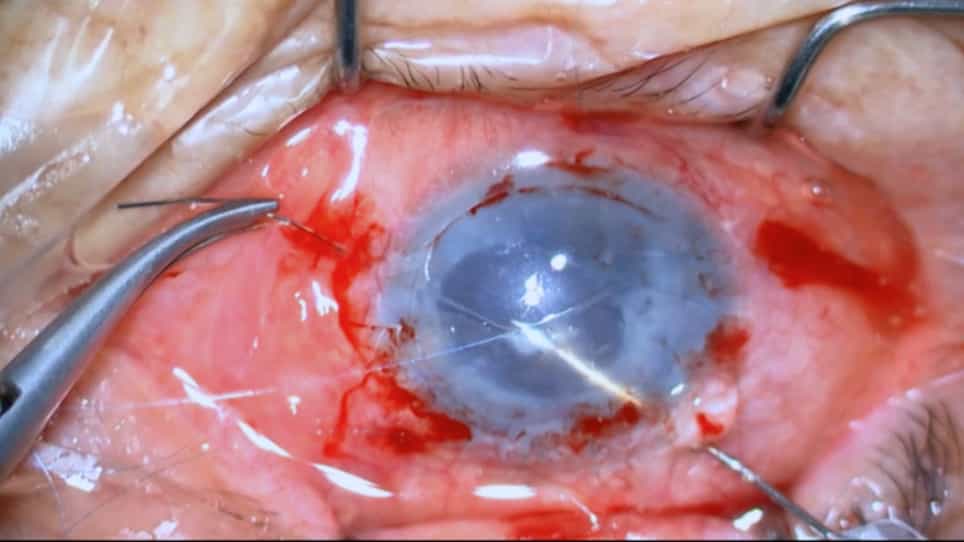
We report of a 38-year-old patient who underwent pars plana vitrectomy (PPV) with PLC tissue for patching secondary FTMH and silicone oil tamponade after tractional retinal detachment. The PLC was peeled off during a vitrectomy 1 year after positioning. For immunocytochemistry, the removed PLC was prepared as flat mount and showed a positive immunofluorescence of the Müller cells marker glutamine synthetase and for vimentin. The microglia marker IBA and the neuroprotective neurotrophic marker glia cell-derived neurotrophic factor were tested positive too. There was no immunoreactivity of cellular retinaldehyde-binding protein and glial fibrillary acidic protein. In comparison, tissue of a control internal limiting membrane that was obtained during standard FTMH surgery showed few single cells that were likewise positive for glutamine synthetase, glia cell-derived neurotrophic factor, and IBA. The control specimen of unexposed PLC showed rarely cells that were without positive immunostaining for the tested markers.
Conclusion:
Our analysis revealed positive immunoreactivity of macroglia and microglia cells of the PLC tissue that was used to patch a refractory FTMH. Similar immunostaining of PLC material and internal limiting membrane suggests the PLC transplantation as an alternative treatment option for refractory FTMH.