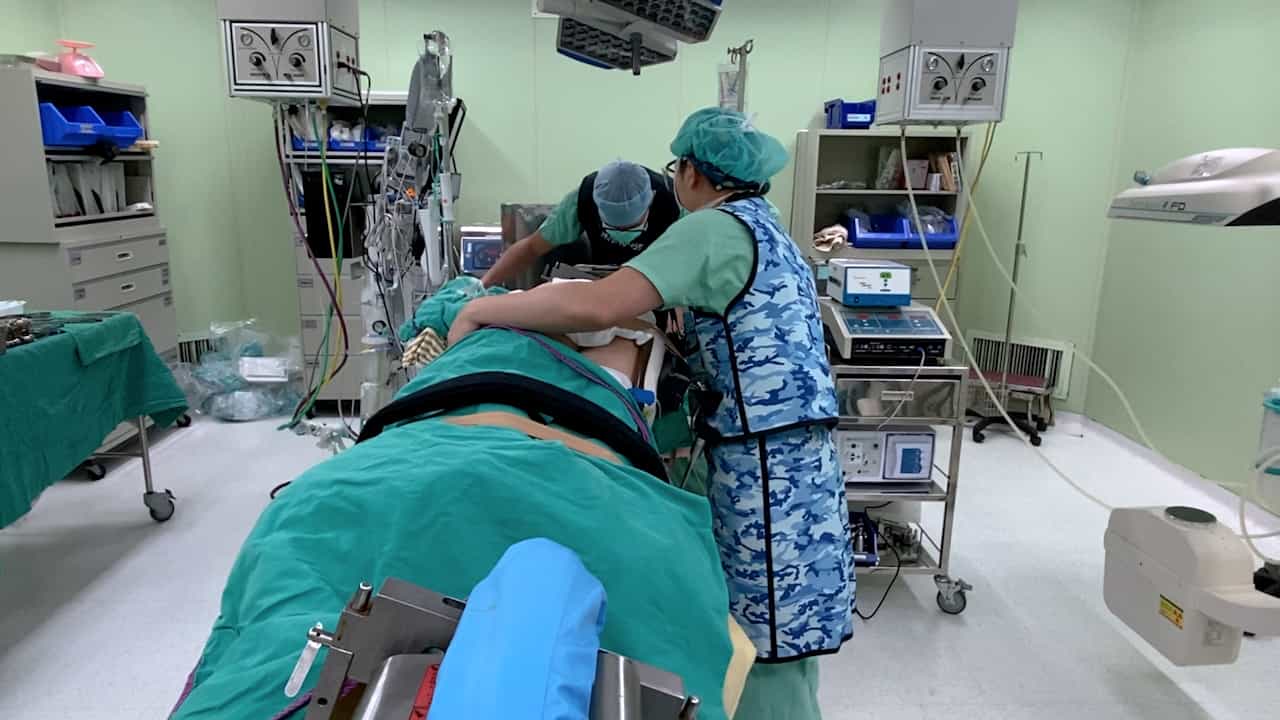
Robot-assisted thoracoscopic plication for diaphragmatic eventration
Related Experiment Video
Updated: Dec 13, 2025
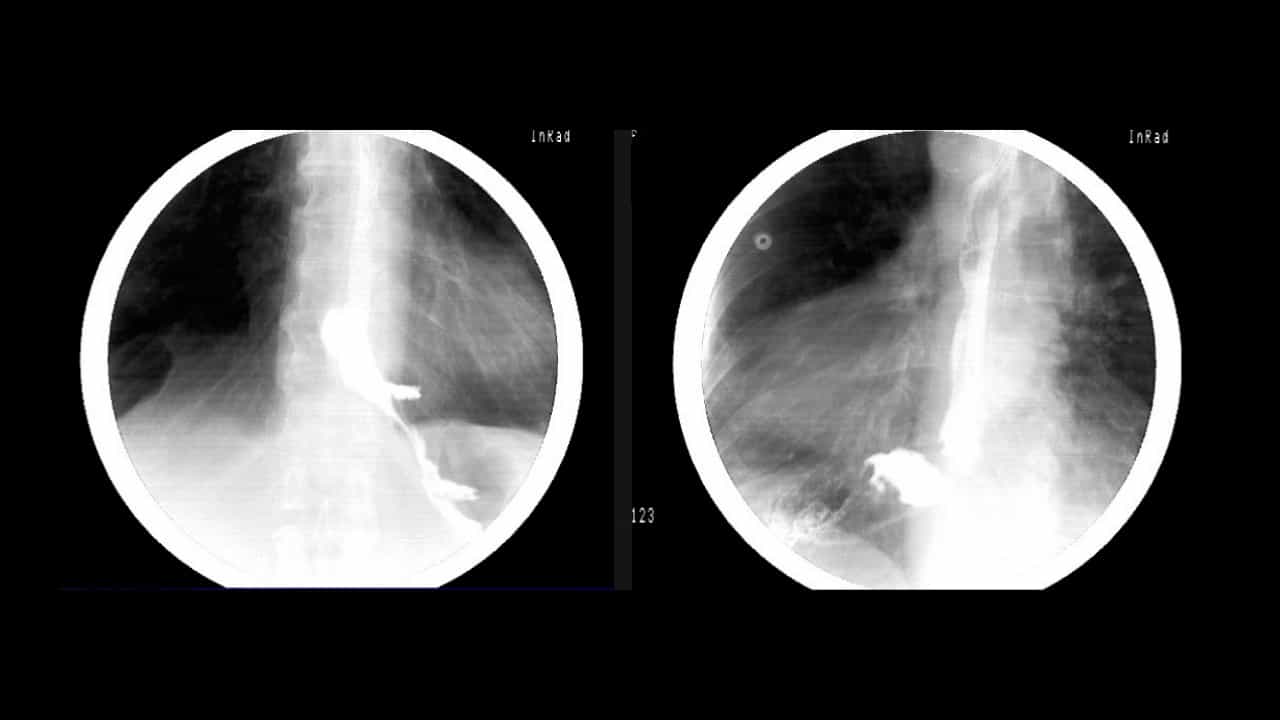
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Pei-Pei Xu1, Xiao-Pan Chang1, Shao-Tao Tang1
1Department of Pediatric Surgery, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan 430022, China.

Background:
Though conventional thoracoscopic plication is a favorable option of diaphragmatic eventration (DE), ribs limited the movement of trocars, making it difficult to suturing, knot-tying and time-consuming. The purpose of this study was to evaluate delicate surgical maneuvers and suturing time for the management of DE in robot-assisted thoracoscopic plication (RATP).
Methods:
From January 2015 to November 2019, 20 patients (14 males; mean age: 10.5 ± 5.2 months; mean weight: 8.6 ± 4.5 kg) who underwent diaphragmatic plication for DE were reviewed at our institution. There were 13 patients with congenital diaphragmatic eventration and 7 patients with acquired diaphragm eventration after congenital heart surgery. RATP was performed on 9 patients (3 on the left and 6 on the right), and conventional thoracoscopic plication (CTP) was applied to 11 patients (5 on the left and 6 on the right). Demographics, the suturing time and complications were respectively evaluated.
Results:
There was no difference between 2 groups with respect to gender, age at surgery and weight (p > 0.05). No conversion to thoracotomy was needed. The suturing time in RATP group was shorter than CTP group (27.7 ± 3.4 min vs 48.1 ± 4.2 min, p < 0.001). One patient (9.09%) experienced recurrence in CTP group and none was found in RATP group.
Conclusions:
Diaphragmatic plication with robot-assisted thoracoscopy or conventional thoracoscopy in DE has minimally invasive and good effect on children. RATP overcome the intercostal limitations to complete delicate suturing and free knot-tying, and has better ergonomics.
Level Of Evidence:
Level III.