Enhanced recovery after surgery in ventral hernia repair: A quantitative content analysis
Related Experiment Video
Updated: Nov 8, 2026
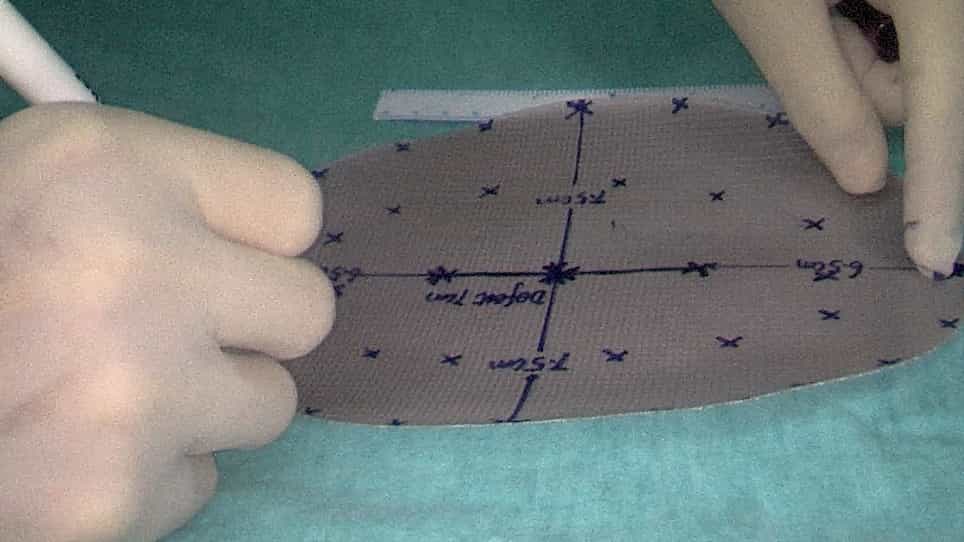
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Guilherme de Carvalho Caldas1, Clara Avelar Mendes de Vasconcellos2, Lorraine Michelle da Silva de Almeida3
1Universidade de Brasília, Brasília, Distrito Federal, Brazil.

Background:
Enhanced recovery after surgery protocols have demonstrated consistent evidence-based benefits in several surgical specialties; however, a standardized pathway for ventral hernia repair has not been defined. Previous meta-analyses suggest that enhanced recovery after surgery implementation in ventral hernia repair may reduce length of hospital stay, but significant heterogeneity in protocol composition has limited the interpretation and applicability of these findings. This review synthesizes current evidence and applies a quantitative content analysis of protocol composition to propose a standardized enhanced recovery after surgery pathway for ventral hernia repair.
Methods:
A comprehensive systematic review was conducted to include studies reporting abdominal wall reconstruction or ventral hernia repair of patients managed with a multimodal perioperative care pathway versus conventional care. We analyzed the following outcomes: overall postoperative complications, surgical site infection, surgical site outcomes, length of hospital stay, and 30-day readmission rates. Protocol composition was assessed by extracting 23 predefined perioperative components as binary variables (reported versus not reported) and summarizing them descriptively.
Results:
A total of 111 records were identified, and 11 studies (1 prospective cohort and 10 retrospective cohorts) met the inclusion criteria, comprising 3,462 patients (1,893 enhanced recovery after surgery, 1,569 pre-enhanced recovery after surgery). The weighted mean age and body mass index were 57.4 years and 31.9 kg/m2, respectively. Most patients underwent open ventral hernia repair. Length of hospital stay was the most consistently reported outcome, with enhanced recovery after surgery cohorts demonstrating a weighted mean of 5.32 ± 4.07 days (Δ = -0.53 days), without an associated increase in 30-day readmission rates. Surgical site infection, surgical site outcome, and overall complication rates showed variable trends toward improvement, although findings were highly heterogeneous across cohorts. The composition of enhanced recovery after surgery pathways varied substantially, ranging from 6 to 21 components (median, 10). Postoperative elements were the most consistently implemented, whereas both depth and density of pathway components varied. Early removal of drains or urinary catheters was reported in 10 studies (91%), followed by early feeding in 9 (82%) and multimodal analgesia in 8 (73%). In contrast, preoperative elements were less consistently implemented. Quality assessment indicated that the evidence remains heterogeneous and primarily based on retrospective historical cohorts.
Conclusion:
Enhanced recovery after surgery implementation in ventral hernia repair consistently reduces length of hospital stay, and the evidence is increasingly supportive of reductions in surgical site infection and surgical site outcome. Standardizing a ventral hernia repair-specific enhanced recovery after surgery pathway with 11 core components, based on the most consistently implemented actions from these studies, may be feasible to improve the quality of these findings.