Related Experiment Video
Updated: Dec 9, 2025

A Novel Rescue Technique for Difficult Intubation and Difficult Ventilation
Published on: January 17, 2011
A Retrospective Evaluation of Airway Anatomy in Young Children and Implications for One-Lung Ventilation
Martina G Downard1, Amy J Lee1, Christopher J Heald2
1Department of Anesthesiology, Wake Forest School of Medicine, Winston-Salem, NC.

Insights
Understanding pediatric lower airway anatomy is crucial for successful one-lung ventilation (OLV) in children. This study provides key measurements to guide endotracheal tube and bronchial blocker selection for safer OLV procedures.
Area of Science:
- Pediatric Anesthesiology
- Thoracic Surgery
- Pediatric Respiratory Anatomy
Background:
- One-lung ventilation (OLV) in pediatric patients is challenging due to limited anatomical data.
- Establishing best practices for OLV in children requires detailed lower airway measurements.
Purpose of the Study:
- To describe lower airway anatomy in children younger than 8 years.
- To provide data to guide the selection of equipment for pediatric OLV.
Main Methods:
- Retrospective observational study of 111 children (<8 years old).
- Analysis of chest computed tomographic scans.
- Measurements of tracheal and bronchial dimensions, including carina to lobar branch lengths.
Main Results:
- The left mainstem bronchus is smaller than the right.
- Specific recommendations for endotracheal tube sizing for left-sided OLV.
- Guidance on age-based transitions for bronchial blocker sizes (5F to 7F Arndt at 3-4 years).
Conclusions:
- Detailed pediatric airway anatomy knowledge aids successful OLV.
- Anatomical data can improve the safety and efficacy of OLV in young children.
Objective:
One-lung ventilation (OLV) in children remains a niche practice with few studies to guide best practices. The objective of this study was to describe lower airway anatomy relevant to establishment of OLV in young children.
Design:
Retrospective, observational study using pre-existing studies in the electronic health record.
Setting:
Single institution, academic medical center, tertiary-care hospital.
Participants:
Pediatric patients <8 years old.
Interventions:
None.
Measurements And Main Results:
Chest computed tomographic scans of 111 children 4 days to 8 years of age were reviewed. Measurements were taken from the thyroid isthmus to the carina, carina to first lobar branch on the left and right, diameter of the trachea at the carina, and diameter of the left and right mainstem bronchi. Dimensions were correlated with the outer diameter of endotracheal tubes and bronchial blockers. The left mainstem bronchus is consistently smaller than the right. Lung isolation using a mainstem technique on the left should use an endotracheal tube a half size smaller than would be used for tracheal intubation. The length from the carina to the first lobar branch on the left is consistently 3 times longer than on the right. Further, age-delineated bronchial diameters suggest that the clinician should transition from a 5F to a 7F Arndt bronchial blocker at 3-to-4 years of age.
Conclusion:
A more detailed and accurate understanding of pediatric lower airway anatomy may assist the clinician in successfully performing OLV in young children.

Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:15
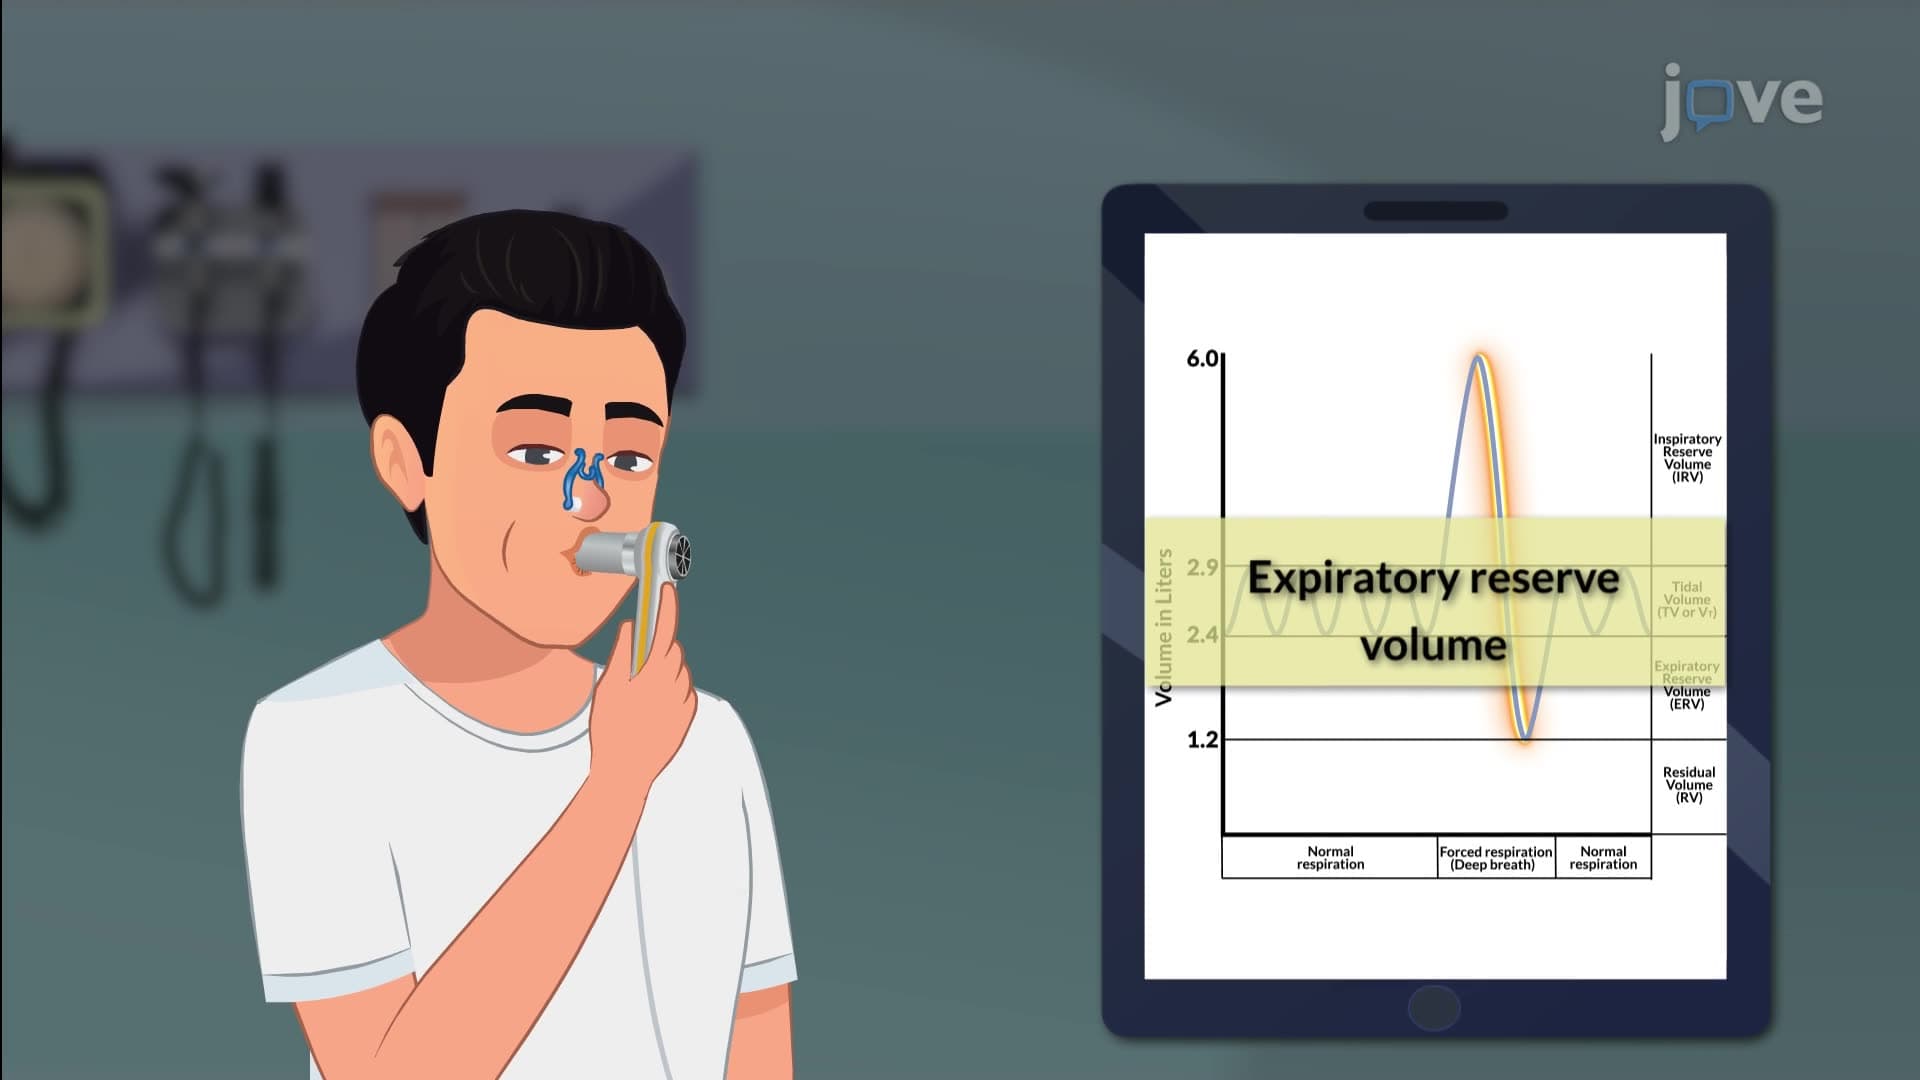
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...