Related Experiment Video
Updated: Nov 12, 2025


Comprehensive Autopsy Program for Individuals with Multiple Sclerosis
Published on: July 19, 2019
Evolution of Brain Volume Loss Rates in Early Stages of Multiple Sclerosis
Tomas Uher1, Jan Krasensky2, Charles Malpas2
1From the CORe (T.U., C.M., T.K.), Department of Medicine, the University of Melbourne, VIC, Australia; Department of Neurology and Center of Clinical Neuroscience (T.U., E.K.H., D.H.), Charles University in Prague, 1st Faculty of Medicine and General University Hospital; Department of Radiology (J.K., M.V.), Charles University in Prague, First Faculty of Medicine and General University Hospital in Prague, Czech Republic; Buffalo Neuroimaging Analysis Center (N.B., M.G.D., R.Z.), Department of Neurology, Jacobs School of Medicine and Biomedical Sciences, University at Buffalo, State University of New York; IRCCS (N.B.), Fondazione Don Carlo Gnocchi, Milan, Italy; Center for Biomedical Imaging at Clinical Translational Science Institute (R.Z.), University at Buffalo, State University of New York; and Melbourne MS Centre (T.K.), Department of Neurology, the Royal Melbourne Hospital, VIC, Australia. tomas.uher@vfn.cz.

Objective:
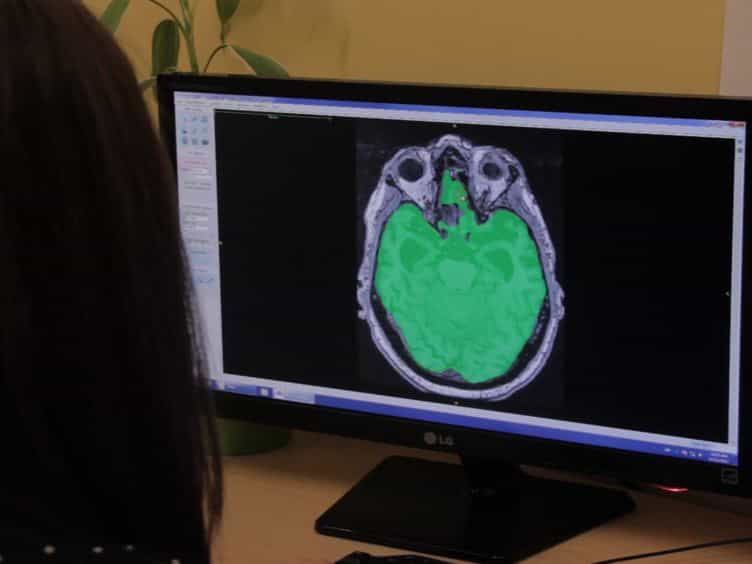
To describe the dynamics of brain volume loss (BVL) at different stages of relapsing-remitting multiple sclerosis (RRMS), to describe the association between BVL and clinical measures, and to investigate an effect of treatment escalation on the rate of BVL.
Methods:
Together, 1903 patients predominantly with RRMS from the Avonex-Steroids-Azathioprine cohort (N = 166), the study of early IFN-β1a treatment cohort (N = 180), and the quantitative MRI cohort (N = 1,557) with ≥2 MRI scans and ≥1-year of follow-up were included. Brain MRI scans (N = 7,203) were performed using a single 1.5-T machine. Relationships between age or disease duration and global and tissue-specific BVL rates were analyzed using mixed models.
Results:
Age was not associated with the rate of BVL (β = -0.003; Cohen f2 = 0.0005; adjusted p = 0.39). Although disease duration was associated with the rate of BVL, its effect on the BVL rate was minimal (β = -0.012; Cohen f2 = 0.004; adjusted p = 4 × 10⁻⁵). Analysis of association between tissue-specific brain volume changes and age (β = -0.019 to -0.011; adjusted p = 0.028-1.00) or disease duration (β = -0.028 to -0.008; adjusted p = 0.16-0.96) confirmed these results. Although increase in the relapse rate (β = 0.10; adjusted p = 9 × 10⁻⁹), Expanded Disability Status Scale (EDSS; β = 0.17; adjusted p = 8 × 10⁻⁵), and EDSS change (β = 0.15; adjusted p = 2 × 10⁻⁵) were associated with accelerated rate of BVL, their effect on the rate of BVL was minimal (all Cohen f2 ≤ 0.007). In 94 patients who escalated therapy, the rate of BVL decreased following treatment escalation by 0.29% (β = -0.29; Cohen f2 = 0.133; p = 5.5 × 10⁻⁸).
Conclusions:
The rate of BVL is relatively stable throughout the course of RRMS. The accelerated BVL is weakly associated with concurrent higher disease activity, and timely escalation to high-efficacy immunotherapy helps decrease the rate of BVL.