Related Experiment Video
Updated: Nov 6, 2025
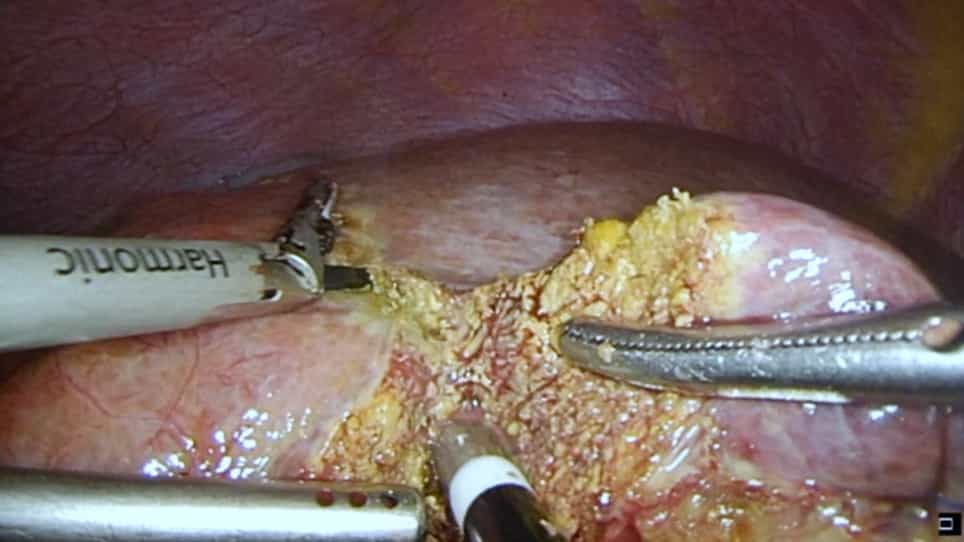

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Treatment of bleeding in patients with liver disease
Patrick G Northup1, Ton Lisman2, Lara N Roberts3
1Center for the Study of Hemostasis and Coagulation in Liver Disease, Division of Gastroenterology and Hepatology, University of Virginia, Charlottesville, VA, USA.

Patients with cirrhosis frequently have complex alterations in their hemostatic system. Although routine diagnostic tests of hemostasis in cirrhosis (platelet count, prothrombin time, fibrinogen level) are suggestive of a bleeding tendency, it is now widely accepted that these tests do not reflect hemostatic competence in this population. Rather, patients with cirrhosis appear to have a rebalanced hemostatic system with hypercoagulable elements. Therefore, routine correction of hemostasis laboratory values, for example by fresh frozen plasma or platelet concentrates, with the aim to avoid spontaneous or procedure-related bleeding is not indicated as is outlined in recent clinical guidance documents. However, little guidance on how to manage patients with cirrhosis that are actively bleeding is available. Here we present three common bleeding scenarios, variceal bleeding, post-procedural bleeding and bleeding in a critically ill cirrhosis patient, with specific management suggestions. As patients with cirrhosis generally have adequate hemostatic competence and as bleeding complications may be unrelated to hemostatic failure, prohemostatic therapy is not the first line of management in bleeding patients with cirrhosis, even in the presence of markedly abnormal platelet counts and/or prothrombin times. We provide a rationale for the restrictive approach to prohemostatic therapy in bleeding patients with cirrhosis.
Patients with cirrhosis frequently have complex alterations in their hemostatic system. Although routine diagnostic tests of hemostasis in cirrhosis (platelet count, prothrombin time, fibrinogen level) are suggestive of a bleeding tendency, it is now widely accepted that these tests do not reflect hemostatic competence in this population. Rather, patients with cirrhosis appear to have a rebalanced hemostatic system with hypercoagulable elements. Therefore, routine correction of hemostasis laboratory values, for example by fresh frozen plasma or platelet concentrates, with the aim to avoid spontaneous or procedure-related bleeding is not indicated as is outlined in recent clinical guidance documents. However, little guidance on how to manage patients with cirrhosis that are actively bleeding is available. Here we present three common bleeding scenarios, variceal bleeding, post-procedural bleeding and bleeding in a critically ill cirrhosis patient, with specific management suggestions. As patients with cirrhosis generally have adequate hemostatic competence and as bleeding complications may be unrelated to hemostatic failure, prohemostatic therapy is not the first line of management in bleeding patients with cirrhosis, even in the presence of markedly abnormal platelet counts and/or prothrombin times. We provide a rationale for the restrictive approach to prohemostatic therapy in bleeding patients with cirrhosis.


Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:30
Venous Thrombosis IV: Nursing Management
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:29
Venous Thrombosis III: Interprofessional Care