Related Experiment Video
Updated: Oct 15, 2025


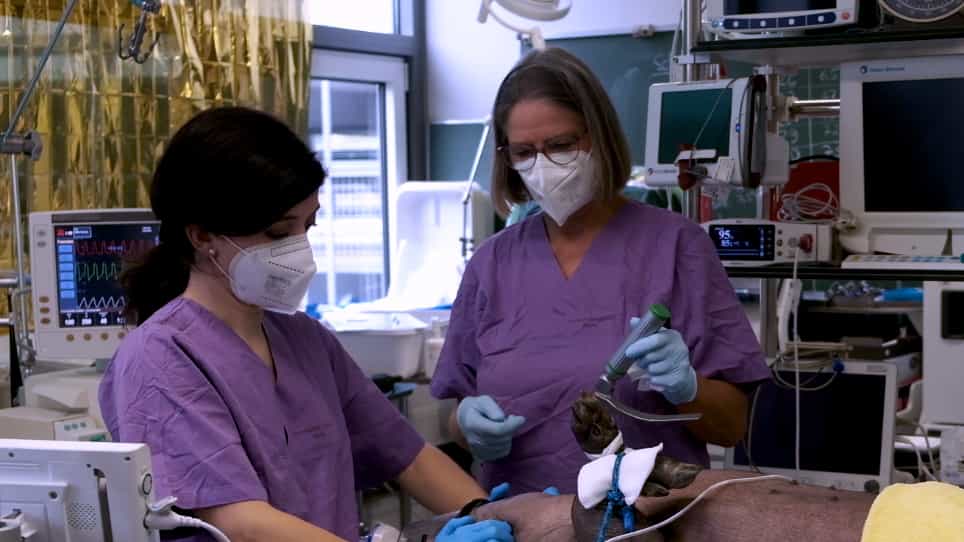
Endotracheal Intubation via Tracheotomy and Subsequent Thoracotomy in Rats for Non-Survival Applications
Published on: March 15, 2024
Outcome after intubation for septic shock with respiratory distress and hemodynamic compromise: an observational
Ting Yang1,2, Yongchun Shen1,2, John G Park2
1Respiratory and Critical Care Medicine, West China Hospital, Sichuan University, Chengdu, 610041, Sichuan, China.

Background:
Acute respiratory failure in septic patients contributes to higher in-hospital mortality. Intubation may improve outcome but there are no specific criteria for intubation. Intubation of septic patients with respiratory distress and hemodynamic compromise may result in clinical deterioration and precipitate cardiovascular failure. The decision to intubate is complex and multifactorial. The purpose of this study was to evaluate the impact of intubation in patients with respiratory distress and predominant hemodynamic instability within 24 h after ICU admission for septic shock.
Methods:
We conducted a retrospective analysis of a prospective registry of adult patients with septic shock admitted to the medical ICU at Mayo Clinic, between April 30, 2014 and December 31, 2017. Septic shock was defined by persistent lactate > 4 mmol/L, mean arterial pressure < 65 mmHg, or vasopressor use after 30 mL/kg fluid boluses and suspected or confirmed infection. Patients who remained hospitalized in the ICU at 24 h were separated into intubated while in the ICU and non-intubated groups. The primary outcome was hospital mortality. The first analysis used linear regression models and the second analysis used time-dependent propensity score matching to match intubated to non-intubated patients.
Results:
Overall, 358 (33%) ICU patients were eventually intubated after their ICU admission and 738 (67%) were not. Intubated patients were younger, transferred more often from an outside facility, more critically ill, had more lung infection, and achieved blood pressure goals more often, but lactate normalization within 6 h occurred less often. Among those who remained hospitalized in the ICU 24 h after sepsis diagnosis, the crude in-hospital mortality was higher in intubated than non-intubated patients, 89 (26%) vs. 82 (12%), p < 0.001, as was the ICU mortality and ICU and hospital length of stay. After adjustment, intubation showed no effect on hospital mortality but resulted in fewer hospital-free days through day 28. One-to-one propensity resulted in similar conclusion.
Conclusions:
Intubation within 24 h of sepsis was not associated with hospital mortality but resulted in fewer 28-day hospital-free days. Although intubation remains a high-risk procedure, we did not identify an increased risk in mortality among septic shock patients with predominant hemodynamic compromise.

Related Concept Videos
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: