Related Experiment Video
Updated: Oct 11, 2025

Measuring Local Anaphylaxis in Mice
Published on: October 14, 2014
Idiopathic anaphylaxis: Diagnosis and management
Alyssa G Burrows1, Anne K Ellis1
1From the Allergy Research Unit, Kingston Health Sciences Center - KGH Site, Kingston, Ontario, Canada.

Abstract:
Introduction: Idiopathic anaphylaxis (IA) is a diagnosis of exclusion and is based on the inability to identify a causal relationship between a trigger and an anaphylactic event, despite a detailed patient history and careful diagnostic assessment. The prevalence of IA among the subset of people who experienced anaphylaxis is challenging to estimate and varies widely, from 10 to 60%; most commonly noted is ∼20% in the adult anaphylactic population. Comorbid atopic conditions, such as food allergy, allergic rhinitis, and asthma, are present in up to 48% of patients with IA. Improved diagnostic technologies and an increased understanding of conditions that manifest with symptoms associated with anaphylaxis have improved the ability to determine a more accurate diagnosis for patients who may have been initially diagnosed with IA. Methods: Literature search was conducted on PubMed, Google Scholar and Embase. Results: Galactose-α-1,3-galactose (α-gal) allergy, mast cell disorders, and hereditary a-tryptasemia are a few differential diagnoses that should be considered in patients with IA. Unlike food allergy, when anaphylaxis occurs within minutes to 2 hours after allergen consumption, α-gal allergy is a 3-6-hour delayed immunoglobulin E-mediated anaphylactic reaction to a carbohydrate epitope found in red meat (e.g., beef, lamb, pork). The more recently described hereditary α-tryptasemia is an inherited autosomal dominant genetic trait caused by increased germline copies of tryptase human gene alpha-beta 1 (TPSAB1), which encodes α tryptase and is associated with elevated baseline serum tryptase. Acute management of IA consists of carrying an epinephrine autoinjector to be administered immediately at the first signs of anaphylaxis. Long-term management for IA with antihistamines and other agents aims to potentially reduce the frequency and severity of the anaphylactic reactions, although the evidence is limited. Biologics are potentially steroid-sparing for patients with IA; however, more research on IA therapies is needed. Conclusion: The lack of diagnostic criteria, finite treatment options, and intricacies of making a differential diagnosis make IA challenging for patients and clinicians to manage.


Related Concept Videos
 02:06
Allergic Reactions
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:30
Asthma-IV: Nursing Management
First, in...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:30
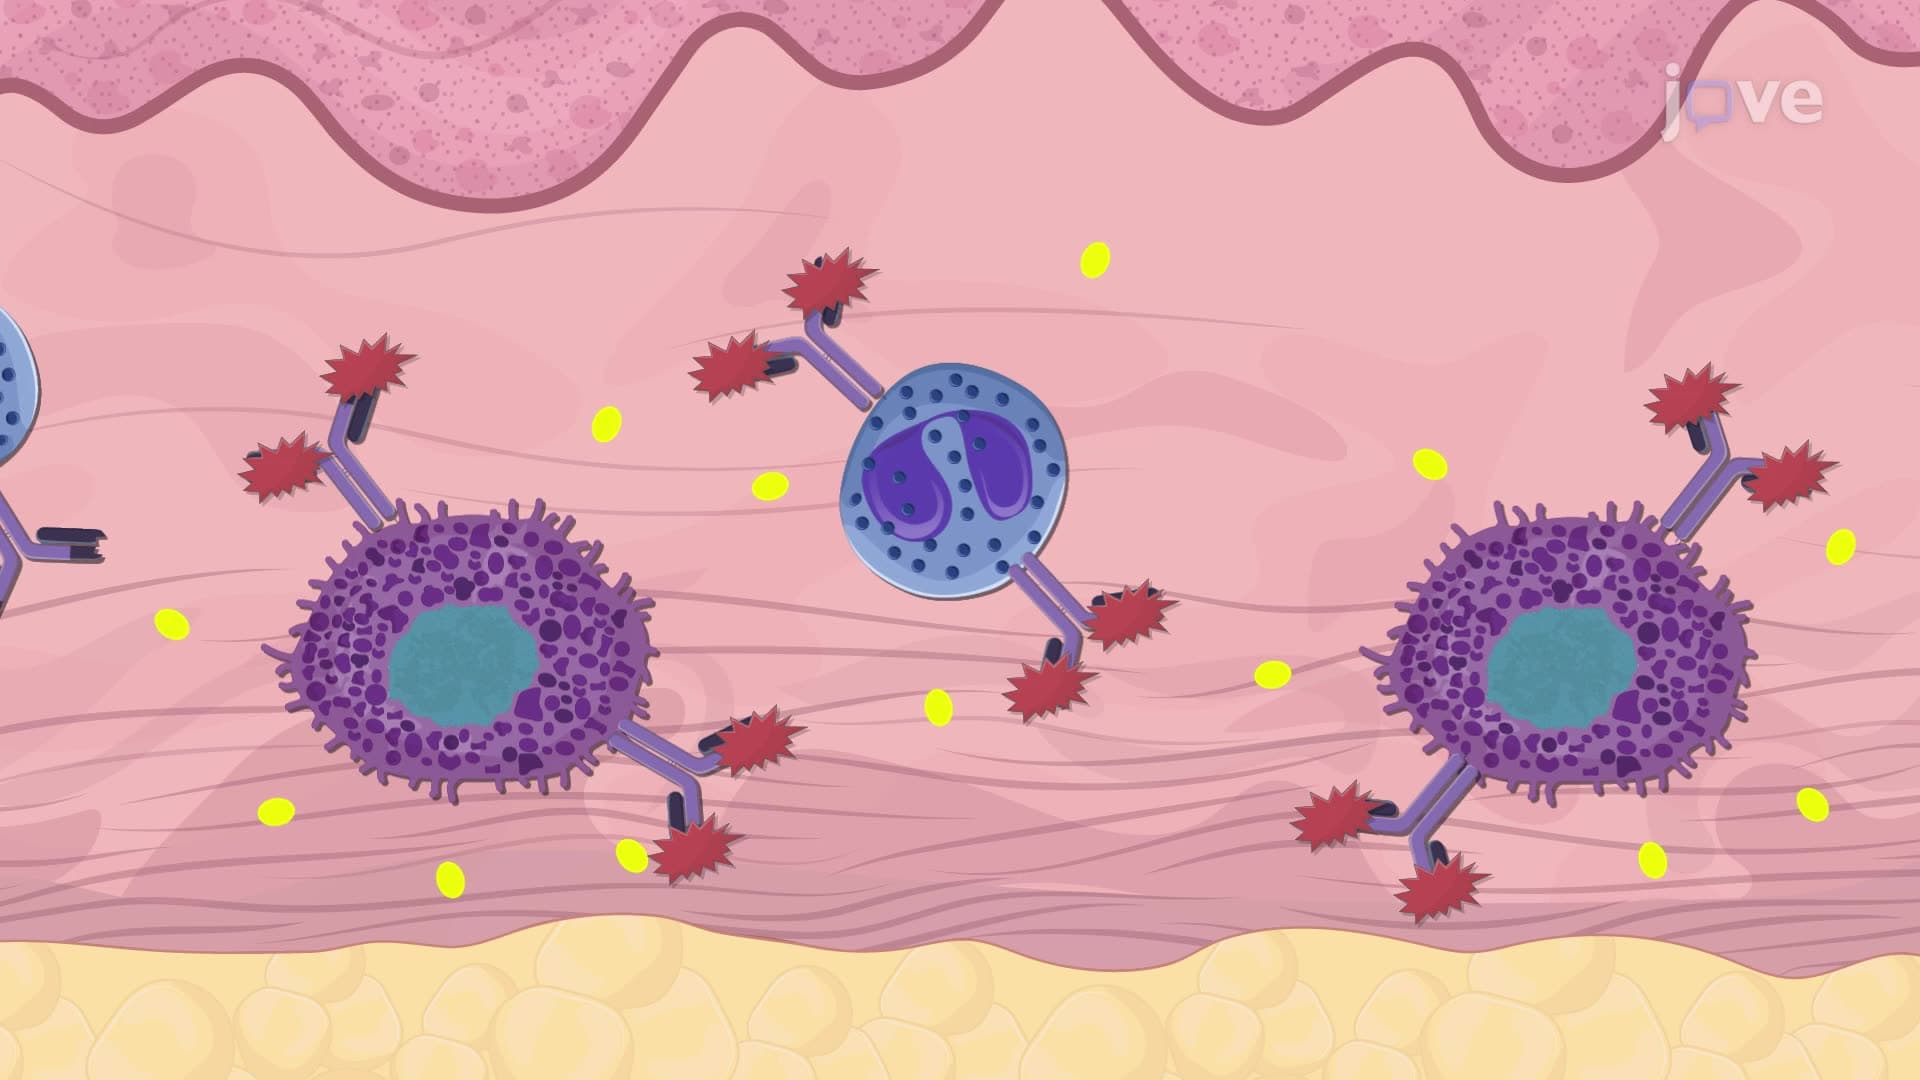
Hypersensitivities
Types of Hypersensitivities
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...