Related Experiment Video
Updated: Oct 3, 2025

Vascularized Composite Hand Allograft Procurement and Preparation for Distal and Proximal Forearm Allotransplantation: A Stepwise Approach
Published on: May 23, 2025
Flexor Digitorum Superficialis Tendon Transfer for Wrist Extension
Alexander J Rondon1, Michael W Aversano2, Chase T Kluemper3
1The Rothman Orthopaedic Institute at Thomas Jefferson University, Philadelphia, Pennsylvania.

Abstract:
Peripheral nerve injuries are among the most complex conditions facing upper-extremity surgeons. Loss of wrist extension can result in marked limitations, including loss of pinch and grip strength with discoordination of grasp and release. Tendon transfers represent the mainstay of operative treatment and have proven to be an effective method for restoring loss of wrist extension. The literature describes myriad techniques to restore loss of wrist extension. The best choice of transfers is dependent on what is available, depending on the level of injury. The present article describes a novel technique of transferring 2 flexor digitorum superficialis (FDS) tendons for wrist extension for patients with radial nerve lesions. The technique involves direct transfer of the long and ring finger FDS tendons to the third metacarpal bone. One FDS is routed through the interosseous membrane while the second FDS tendon is routed radially around the wrist to prevent a net supination or pronation force. If needed, the tendons can be alternatively routed to augment either pronation or supination. Passing both FDS tendons through the interosseous membrane creates a supination moment of the forearm, whereas routing both around the radius adds pronation. This article will review the relevant anatomy, indications, contraindications, operative technique, postoperative management, and outcomes.
Description:
The present article describes the technique of transferring 2 FDS tendons to restore wrist extension in patients who have lost wrist extension secondary to nerve lesions, such as radial nerve palsy and brachial plexus injuries. This technique involves the transfer of the long and ring finger FDS tendons around the base of the long metacarpal. One FDS tendon is routed through the interosseous membrane, and the second FDS tendon is routed radially around the wrist to add a pronation moment to the transfer.
Alternatives:
Alternatives include nerve transfers and tendon transfers1-5, such as:pronator teres to extensor carpi radialis longus and extensor carpi radialis brevis,palmaris longus to flexor carpi radialis,flexor carpi ulnaris to extensor digitorum communis III-V3,flexor carpi radialis to extensor indicis proprius, extensor digitorum communis, and extensor pollicis longus.
Rationale:
The pronator teres tendon has been the primary donor described to restore wrist extension. However, this tendon is often inadequate and requires a periosteal extension. In addition, the pronator muscle may be involved in brachial plexus injures and unavailable as a donor. Lastly, the FDS is synergistic with wrist extension, which facilitates rehabilitation.
Expected Outcomes:
Child and adult patients are expected to have good control of function at 3 months postoperatively, with a full recovery at 6 months postoperatively. Because the FDS is synergistic with wrist extension, rehabilitation is straightforward. The wrist is immobilized in a sugar-tong for 3 to 4 weeks postoperatively, followed by the use of a removable thermoplastic wrist brace for 4 weeks full-time, except when bathing and performing physical therapy, and then for 4 weeks at night only. Physical therapy should focus on activation and training of the FDS under therapist supervision. Supervised active extension exercises can be initiated after week 4 postoperatively, taking care to avoid wrist flexion beyond neutral and resistive exercises. Functional exercises can be initiated at 6 weeks postoperatively, with light resistance only until week 12, coinciding with the discontinued use of the wrist brace.
Important Tips:
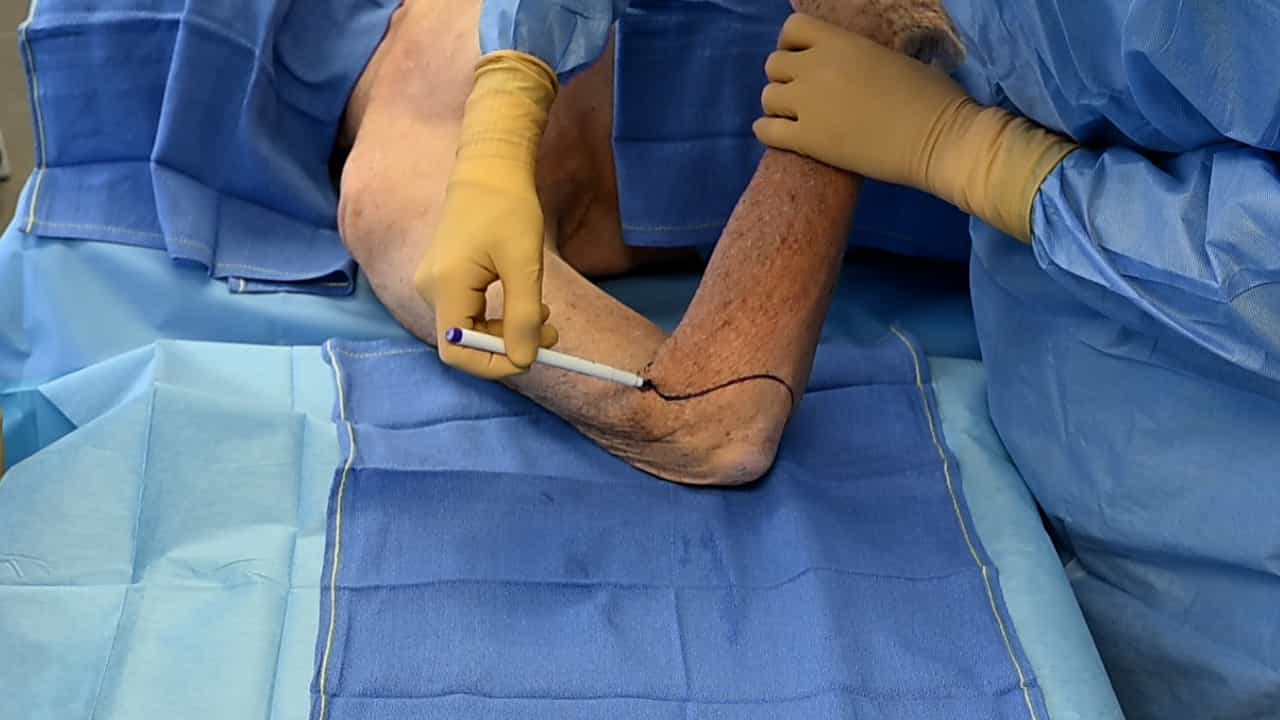
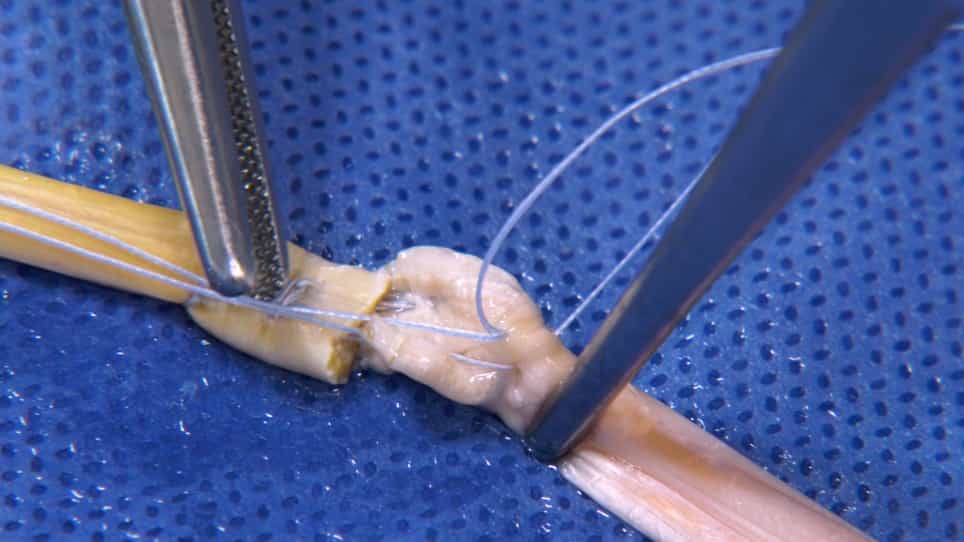
Surgery is performed through 4 primary incisions:○ a volar oblique incision in the distal palmar crease at the base of the long and ring fingers,○ a volar transverse incision at the mid-forearm,○ a dorsal transverse incision over the midshaft of the third metacarpal,○ a dorsal forearm transverse incision opposite to the volar forearm incision to shuttle the FDS tendon.The FDS donor tendons to the long and ring fingers are isolated first.Any adhesions between the FDS and flexor digitorum profundus are divided.The FDS tendons are left in the wounds until later to prevent desiccation.On occasion, the FDS tendons can become caught in the carpal canal during harvesting and will need to be pulled back into the distal palmar incision for further lysis of connections between the FDS and flexor digitorum profundus tendons.A wide window, not a slit, is cut in the interosseous membrane to pass 1 of the FDS tendons.A counter incision in the dorsal forearm is made with use of a long, curved clamp through the interosseous membrane. A Penrose drain is then passed through this tendon portal.Our preferred site for the FDS tendon attachments is around the base of the long metacarpal.
Acronyms And Abbreviations:
FDS = flexor digitorum superficialisPT = pronator teresECRL = extensor carpi radialis longusECRB = extensor carpi radialis brevisFCU = flexor carpi ulnarisEDC = extensor digitorum communisFCR = flexor carpi radialisEIP = extensor indicis propriusEPL = extensor pollicis longusFDP = flexor digitorum profundusMC = metacarpal.
Related Concept Videos
 01:17
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi...
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:15
Bones of the Upper Limb: Ulna
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...